Maybe you have just seasoned your initial warm flash, or probably you have been encountering indications for a though now. Either way, you’re most likely hoping that you will not have to expertise the results of menopause a lot lengthier. Even though each and every woman’s encounter is exceptional, we tapped women’s wellbeing professionals to request, “How long does menopause past?!” and how to find aid in the meantime.
Menopause is defined as the long term cessation of menstruation, which usually occurs all-around the age of 50, although it can happen previously or afterwards, explains Anat Sapan, M.D., board-accredited ob/gyn and menopause pro. “Menopause occurs as a drop in the output of the hormones estrogen, progesterone, and testosterone,” and as a result, you can encounter a range of signs and symptoms for several lengths of time.
So, here’s all the things you will need to know about menopause indications, how extensive those people indicators will very last, and how to manage them.
How extended do menopause signs ordinarily past?
The duration of signs and symptoms (or if you have them at all) are diverse for each and every woman, suggests Beth Oller, M.D., family members doctor at Rooks County Health and fitness Center in Kansas. “The menopausal transition ordinarily starts in between ages 45-55.”
Most ladies have the most bothersome symptoms throughout perimenopause, the decades before you technically enter menopause, claims Dr. Oller. This interval can start off up to 10 several years before you formally enter menopause. “During this time, your overall body begins to make a lot less estrogen and progesterone, and levels of these two hormones both produced by the ovaries can vary drastically, so accounting for various severity and size of indicators,” she explains.
The initial signal that anyone is coming into the menopausal changeover is a change in their menstrual cycles, and this can be cycles either getting nearer together or further aside, and bleeding can be lighter or heavier, notes Dr. Oller.
The length of menopausal signs or symptoms can range commonly from woman to girl, states Sarah de la Torre, M.D., board-accredited OB-GYN, accredited practical medicine practitioner, and health-related advisor at Joylux. “In typical, signs and symptoms can past any place from a couple of months to a number of many years.”
The duration of time that symptoms persist can rely on a wide range of aspects, which include the person woman’s hormonal amounts, age at menopause, and in general overall health, explains Dr. de la Torre. “For some women of all ages, signs and symptoms might only last for a limited period of time of time, even though some others may well practical experience signs and symptoms for several several years or for a longer time.”
Menopause signs or symptoms
Menopause must be assumed of as a few levels: perimenopause, menopause, and postmenopause, clarifies Dr. Oller. Signs or symptoms that most people today affiliate with menopause typically get started through perimenopause, and the regular quantity of time for perimenopausal signs or symptoms is 4 a long time.
A person is deemed to have reached menopause when they haven’t experienced a time period for 12 consecutive months, then postmenopause commences, notes Dr. Oller. “Symptoms normally make improvements to in the menopause and postmenopause phases.”
The typical signs of menopause can range from girl to girl. According to Dr. de la Torre, these can include things like the pursuing:
Scorching flashes and evening sweats: These are frequent symptoms of menopause and can very last for a number of months to quite a few a long time. The frequency and severity of sizzling flashes and night sweats can also differ commonly.
Irregular periods: As ladies approach menopause, their menstrual cycles might become irregular right before ultimately halting. This can final for a number of months to a few years.
Vaginal dryness and pain: Reduced estrogen degrees all through menopause can lead to vaginal dryness and irritation during intercourse. This can very last for several months to quite a few decades.
Difficulty sleeping: Insomnia and other sleep disturbances can be frequent symptoms of menopause and can final for quite a few months to various yrs. This can be thanks to other indications, this sort of as very hot flashes or temper modifications, but it can also be thanks to slumber apnea. Scientific tests have demonstrated that postmenopausal females are two to three instances a lot more most likely to have rest apnea when compared with premenopausal women.
Temper alterations: Fluctuating estrogen and progesterone degrees, additionally other elements, cause serotonin generation disruption, leading to additional mood swings, for each the Endocrine Modern society. Mood swings, irritability, and melancholy are frequent during menopause and can previous for quite a few months to various several years.
Fatigue: Fluctuating estrogen and progesterone levels can also guide to exhaustion. A lot of ladies experience exhaustion and diminished energy for the duration of menopause, which can previous for numerous months to many a long time.
Urinary issues: Decreased estrogen ranges can weaken the bladder and the urethra, compromising their potential to command urinary features. Lowered estrogen also alters the acidity of the vulva and the vagina, which can make the place extra vulnerable to infection by microorganisms or yeast overgrowth, for each Colorado’s Women’s Wellbeing. This is why menopause can maximize the hazard of urinary incontinence and urinary tract bacterial infections. These indications can past for several months to a number of many years.
In addition to the indicators shown previously mentioned, Dr. Oller provides that you could also working experience dry pores and skin and eyes, complications, hair reduction or thinning, body weight get, alter in concentrate and memory, and joint agony.
There are also silent signs that need not be overlooked, these kinds of as bone reduction owing to gradual bone reduction of bone density, cognitive decrease, increased danger of cardiovascular hazard, and changes in vaginal well being and diminished libido, notes Dr. Sapan. “It’s important to observe that these silent indicators of menopause could not be straight away apparent, but can have a substantial impact on a woman’s general health and good quality of existence.”
How can you regulate menopause signs and symptoms?
The superior news is answers now exist to address menopause indicators and ladies no for a longer period have to put up with in silence, claims Dr. de la Torre.
Every single lady has her own exclusive practical experience. On the other hand, there are various strategies to manage indicators, which includes:
Hormone replacement treatment: The most helpful way to address the signs of menopause is with hormone alternative remedy (HRT), says Dr. Sapan. “This procedure requires replacing the estrogen, progesterone, and testosterone that are lost for the duration of menopause with synthetic hormones.” HRT can assistance alleviate signs and symptoms this sort of as sizzling flashes, evening sweats, and vaginal dryness but also protect the brain, bones, and coronary heart.
Most medical practitioners will prescribe the cheapest amount of hormone for the shortest total of time, simply because there are pitfalls to getting hormones, says Dr. Oller. Some of these challenges include things like a greater risk of endometrial cancer (only when estrogen is taken without progestin), breast most cancers with long-expression use, cardiovascular condition (which include coronary heart attack), and blood clots and stroke, for every Cleveland Clinic. Continue to, Dr. Oller believes “the gains will possible outweigh them if someone’s existence is remaining influenced by regular very hot flashes.”
Life-style changes: Generating wholesome way of life modifications can also assist deal with menopause signs or symptoms. Feeding on a well balanced eating plan, staying physically active, decreasing anxiety, and obtaining plenty of rest can all help strengthen overall well being and minimize the severity of signs and symptoms, notes Dr. Sapan.
Choice therapies: Some women locate reduction from menopause indications by means of option therapies these kinds of as acupuncture, yoga, particular supplements, and meditation, says Dr. de la Torre.
Drugs: Specified medicines these types of as antidepressants, blood pressure remedies, and other people may also be prescribed to deal with menopause signs and symptoms, suggests Dr. de la Torre. If somebody is continue to acquiring intervals, a small dose delivery manage tablet can assist swap the estrogen that is low and so causing indications, notes Dr. Oller.
Vaginal lubricants: Women of all ages suffering from vaginal dryness and distress all through intercourse can use in excess of-the-counter vaginal lubricants to alleviate symptoms, implies Dr. de la Torre. You can communicate to your loved ones doctor about which ones they propose, and also if these do not assistance, to discuss other options like topical estrogen cream to help with signs and symptoms, provides Dr. Oller.
House-use units and items: For very hot flashes, Dr. Oller suggests acquiring a supporter at function or household, removing clothing when it feels like a incredibly hot flash is coming on, and seeing if you can detect any triggers that look to carry your scorching flashes on and prevent them. From skincare to vaginal care, uncover what operates for you, says Dr. de la Torre. “Focus on what problems you the most and chat to your physician to see what they can suggest exclusively for you.”
Supplements: Nutritional supplements might support you fill in dietary gaps, aid your body’s all-natural procedures and some might enable relieve menopausal signs and symptoms, says Chloe Giraldi, M.S., R.D., L.D.N., registered dietitian and VP Nutrition Science at Phenology. Nonetheless, dietary supplements need to be a complement to a healthier life style, balanced diet plan, day by day motion, anxiety management, and slumber practices, not a substitute, she notes. “Focus on developing wholesome behaviors 1st and take into consideration health supplements the ‘icing on the cake’ once you have a solid basis.”
It’s significant to note that the duration of any menopause signs or symptoms can differ widely from female to woman and can also rely on the severity of symptoms and all round wellness, claims Dr. de la Torre. “If you are encountering signs and symptoms that are affecting your high-quality of life, it’s important to talk about your considerations with your healthcare provider.”
When really should you see a doctor about menopause symptoms?
There is no time like the present to start off talking about your signs or symptoms with your medical doctor to obtain out what approaches you can ideal handle them. You need to see a physician when you initially start off having signs and symptoms of slumber disturbances or scorching flashes, even if you are in the perimenopause stage, claims Dr. Sapan. “You never want to wait until eventually your menses cease.”
Menopause can have a major effects on a woman’s all round overall health, so normal examine-ups and screenings are critical, adds Dr. de la Torre. “Your medical doctor can enable you regulate any symptoms and supply guidance on sustaining your total health and nicely-getting for the duration of this changeover.” She indicates wanting for physicians who have specialised schooling on menopause and who can work by the ups and downs of this inescapable time of daily life with you.
Ladies are the experts of their own bodies and know it greater than anyone else, says Giraldi. “It’s important to start to create rapport with a physician specially qualified in menopause treatment as quickly as you get started to notice signs or symptoms, or adjustments in your human body.” They’ll be equipped to suggest you if your indicators are linked to menopause, or an underlying situation and assess your total wellness.
Your menopause journey is exceptional to you and is formed by factors like diet, lifestyle, sleep, tension, ethnicity, genetics and more, states Giraldi. “If you do not sense like you are obtaining the suitable treatment, don’t be frightened to seek further views.” Giraldi continues to say that it can be worthwhile to have numerous providers weigh in and you might think about creating a team that will support you in the way that you will need.
Dietary health supplements are goods intended to complement the diet regime. They are not medications and are not intended to address, diagnose, mitigate, avoid, or treatment illnesses. Be careful about using dietary dietary supplements if you are expecting or nursing. Also, be careful about giving supplements to a boy or girl, until advised by their health care company.
Madeleine, Prevention’s assistant editor, has a history with wellbeing crafting from her working experience as an editorial assistant at WebMD, and from her own exploration at university. She graduated from the College of Michigan with a diploma in biopsychology, cognition, and neuroscience—and she helps strategize for good results throughout Avoidance’s social media platforms.
Ashley Hartig, 27, reported that she and her spouse Derek Hartig, who now experienced two young children alongside one another, ended up ready for a 3rd little one but didn’t want to wait around on her health practitioner — so she took issues into her personal hands, basically.
“I hadn’t spoken to a health practitioner about having it out myself, I experienced an appointment scheduled for two months with my gynecologist but that was just for an exam to test the IUD,” reported Ashley, who’s racked up 1.3 million followers and far more than 44 million likes with @TheHartigFamily video clips on TikTok.
“From there they would then e-book me in to take it out,” the impatient 27-12 months-aged mother from Florida added. “So, it would be all around 4 weeks right before it in fact arrived out.”
According to Ashley, both she and her childhood sweetheart Derek initially only wished two young ones: Ryker, 6, and daughter Presley, 3.
Nonetheless, when the realized they required a third, she spent several hours on social media wanting for other girls who experienced taken out their very own intrauterine gadget or IUD.
A female went viral on TikTok immediately after she disclosed that removed her individual IUD contraceptive immediately after declaring that it was having also extended to get an appointment with her gynecologist. @ashley.hartig / CATERS Information
The IUD is a little, T-shaped product produced of plastic or copper with a string at the end to help with removing, much like the string on a tampon. A doctor has to insert it by carefully guiding it via the vagina and cervix and then into the uterus.
“It was on brain my each individual day about having it out, I had seen movies of other gals doing it as very well,” Ashley advised Caters News. “It took a large amount of bravery, but now I experience empowered and cleansed. I was scrolling TikTok for hours striving to obtain other women of all ages who had finished it as nicely.”
Ashley Hartig, 27, reported that she and her husband Derek — who now experienced two little ones collectively — had been completely ready for a 3rd child but didn’t want to hold out for an appointment so she took issues into her have arms … pretty actually.@ashley.hartig / CATERS Information
“They were being indicating how quick it was, so just one working day when my husband was at get the job done, I just pulled it out,” she continued. “I felt the strings and just pulled it straight out of my cervix. It arrived out so easily and there was no blood either just a minimal scar tissue about it.”
The method wasn’t particularly pain-free of charge, nonetheless. She admitted whilst trying to pull it out she did experience some agony.
Hartig stated that she used several hours on social media seeking for other females who had taken out their have IUDs. @ashley.hartig / CATERS Information In accordance to the 27-year-old, equally she and her childhood sweetheart to begin with only required two young ones, but sooner or later realized they desired a 3rd. @ashley.hartig / CATERS Information
“I just experienced to uncover some internal power to do it, even though I experienced under no circumstances felt the strings in advance of. I just knew I needed to get a great grip on it,” defined the Florida native. “It took me a couple tries, I stopped trying and then after a several hrs I made the decision to try out all over again and it arrived out.”
Ashley mentioned it then dawned on her that she could possibly need to have to find medical knowledge just after all.
“It damage a couple situations so I had left it and went to choose my son up from faculty, I referred to as the Prepared Parenthood trying to get an unexpected emergency appointment but they claimed they don’t do them and that I required to go to the healthcare facility,” she reported. “I decided to attempt once again a minimal afterwards on.”
Once the product was taken out, Hartig amazed her partner by gifting the IUD to him. @ashley.hartig / CATERS Information “I handed it to him in a small box, telling him I experienced received him a present,” recalled Hartig. “He couldn’t consider I had pulled it out myself. He was not anticipating it at all, the initially issue he questioned me was if I’m okay.” @ashley.hartig / CATERS Information
At the time the system was taken out, Ashely astonished her partner Derek by gifting the IUD to him.
“I handed it to him in a minor box, telling him I had bought him a reward,” she recalled with a chortle. “He could not believe I had pulled it out myself. He was not expecting it at all, the initially matter he asked me was if I’m all right. He kept expressing how he just didn’t expect it.”
In accordance to Hartig, she had to make clear to her kids what she experienced provided to her spouse and explained to them that it was a little something that “made me not in a position to have toddlers.”@ashley.hartig / CATERS News
In a TikTok online video, which was posted in late February and has given that attained 72,000 sights, Ashley proclaimed the approach designed her experience “empowered. I felt at ease in my overall body and I employed to not experience that way at all. It took a whole lot of braveness and I sense cleansed.”
Ashley also claimed she experienced to make clear to her young children what she experienced specified to her spouse and told them that it was anything that “made me not in a position to have babies.”
Several of the Hartig family’s followers praised her for her bravery.
“I did the same matter experienced one particular interval and was pregnant the next month,” just one consumer posted.
“I experienced to get mine surgically taken off. I’m jealous of your journey,” a further commented.
“I took mine out 3 weeks back! most effective choice of my daily life,” a 3rd individual chimed in.
Other viewers explained that while they respect her decision to eliminate it on her possess, they would somewhat stick to a expert.
“Some critical problems can go in hand with the removing. I would NOT endorse, glad you are all right tho,” recommended one particular unimpressed TikTok viewer.
“Yeaaaah, I’ll just go to the physician. lol,” said a different.
In the meantime, Dr. Diane Greene Foster, a professor of obstetrics and gynecology at the College of California, San Francisco, has said if you are completely ready to have your IUD out for any rationale — there’s in fact no hurt in trying the Do it yourself strategy to elimination.
“When a girl pulls on the string, it is just what a clinician would do,” Dr. Foster told WebMD in 2020. “If you can seize the string, you can take away it oneself.”
The only difference: You are going to have to depend on your fingers rather of a specialised instrument. You will not be able to see what you are undertaking, both, Dr. Foster claimed, including, “If you really don’t get traction, you simply cannot do it. If you can not come to feel the string, your possibility of getting rid of it your self is zero.”
Tara Ghormley has always been an overachiever. She finished at the top of her class in high school, graduated summa cum laude from college and earned top honors in veterinary school. She went on to complete a rigorous training program and build a successful career as a veterinary internal medicine specialist. But in March 2020 she got infected with the SARS-CoV-2 virus—just the 24th case in the small, coastal central California town she lived in at the time, near the site of an early outbreak in the COVID pandemic. “I could have done without being first at this,” she says.
Almost three years after apparently clearing the virus from her body, Ghormley is still suffering. She gets exhausted quickly, her heartbeat suddenly races, and she goes through periods where she can’t concentrate or think clearly. Ghormley and her husband, who have relocated to a Los Angeles suburb, once spent their free time visiting their “happiest place on Earth”—Disneyland—but her health prevented that for more than a year. She still spends most of her days off resting in the dark or going to her many doctors’ appointments. Her early infection and ongoing symptoms make her one of the first people in the country with “long COVID,” a condition where symptoms persist for at least three months after the infection and can last for years. The syndrome is known by medical professionals as postacute sequelae of COVID-19, or PASC.
People with long COVID have symptoms such as pain, extreme fatigue and “brain fog,” or difficulty concentrating or remembering things. As of February 2022, the syndrome was estimated to affect about 16 million adults in the U.S. and had forced between two million and four million Americans out of the workforce, many of whom have yet to return. Long COVID often arises in otherwise healthy young people, and it can follow even a mild initial infection. The risk appears at least slightly higher in people who were hospitalized for COVID and in older adults (who end up in the hospital more often). Women and those at socioeconomic disadvantage also face higher risk, as do people who smoke, are obese, or have any of an array of health conditions, particularly autoimmune disease. Vaccination appears to reduce the danger but does not entirely prevent long COVID.
The most common, persistent and disabling symptoms of long COVID are neurological. Some are easily recognized as brain- or nerve-related: many people experience cognitive dysfunction in the form of difficulty with memory, attention, sleep and mood. Others may seem rooted more in the body than the brain, such as pain and postexertional malaise (PEM), a kind of “energy crash” that people experience after even mild exercise. But those, too, result from nerve dysfunction, often in the autonomic nervous system, which directs our bodies to breathe and digest food and generally runs our organs on autopilot. This so-called dysautonomia can lead to dizziness, a racing heart, high or low blood pressure, and gut disturbances, sometimes leaving people unable to work or even function independently.
The SARS-CoV-2 virus is new, but postviral syndromes are not. Research on other viruses, and on neurological damage from the human immunodeficiency virus (HIV) in particular, is guiding work on long COVID. And the recognition that the syndrome may cause its many effects through the brain and the nervous system is beginning to shape approaches to medical treatment. “I now think of COVID as a neurological disease as much as I think of it as a pulmonary disease, and that’s definitely true in long COVID,” says William Pittman, a physician at UCLA Health in Los Angeles, who treats Ghormley and many similar patients.
Although 16 million U.S. sufferers is a reasonable estimate of the condition’s toll, there are other, more dire assessments. A meta-analysis of 41 studies conducted in 2021 concluded that worldwide, 43 percent of people infected with SARS-CoV-2 may develop long COVID, with about 30 percent—translating to approximately 30 million people—affected in the U.S. Some studies have offered more conservative numbers. A June 2022 survey reported by the U.S. National Center for Health Statistics found that among adults who had had COVID, one in five was experiencing long COVID three months later; the U.K. Office for National Statistics put the estimate at one in 10. Even if only a small share of infections result in long COVID, experts say, they will add up to millions more people affected—and potentially disabled.
Most of the first recognized cases of long COVID were in patients who needed extended respiratory therapy or who had obvious organ damage that caused lasting symptoms. People reporting neurological symptoms were often overlooked or dismissed as traumatized by their initial illness and hospitalization. But as 2020 came to an end, says Helen Lavretsky, a psychiatrist at the University of California, Los Angeles, “we started getting to a place of sorting through what was really going on … and it became very evident at that time that neuropsychiatric symptoms were quite prevalent,” most commonly fatigue, malaise, brain fog, smell loss and post-traumatic stress disorder, as well as cognitive problems and even psychosis.
Ghormley was in her late 30s and relatively healthy when she caught the virus, but she had underlying conditions—including rheumatoid arthritis and asthma—that put her at risk for severe COVID. She spent several days at home, struggling to breathe, and then she went to the hospital, where her blood pressure soared and her blood glucose dropped precipitously. She mostly recovered from this acute phase within a few weeks, but, she says, “I never really got better.”
Soon after coming home from the hospital, Ghormley developed what her husband called “goldfish brain.” “I’d put something down and have no idea where I put it,” she recalls. “It kept happening over and over. I was thinking, ‘This is getting weird.’ My husband said I was not remembering anything. I’d try to talk, and I knew what I wanted to say, but I couldn’t think of the word.”
“Everything fell apart for me,” says Tara Ghormley, who has been struggling with long COVID since 2020. Credit: Ewan Burns
She also experienced tremors, dramatic mood swings and painful hypersensitivity to sounds. “My husband opening a paper bag felt like knives stabbing me in the ear,” she recounts. Any exertion—physical or mental—left her exhausted and in pain. The changes were jarring to Ghormley, who prided herself on her sharp mind. “The thing that bothered me the most was that I was really having trouble thinking, speaking, remembering—trying to complete a task and having no idea what it was. Suddenly I had quite profound neurological deficits. Everything fell apart for me at that time. That was horribly traumatic … it kind of broke me. I didn’t feel like me.”
Roots of Dysfunction
As a veterinary internist, Ghormley says, it’s her job to problem solve when mysterious symptoms arise, including her own. “I was actively trying to find reasons and find what I could do.” She theorized that some of her neurological symptoms might be the result of thrombotic events, blood clots that can cause ministrokes. Several early studies showed that COVID attacks endothelial cells, which line blood vessels. That can lead to clotting and oxygen deprivation in multiple organs, including the brain. Even subtle disruption of endothelial cells in the brain could contribute to cognitive dysfunction.
One study found that in people with neurological COVID symptoms, the immune system seems to be activated specifically in the central nervous system, creating inflammation. But brain inflammation is probably not caused by the virus infecting that organ directly. Avindra Nath, who has long studied postviral neurological syndromes at the National Institutes of Health, found something similar in an autopsy study of people who died of COVID. “When you look at the COVID brain, you don’t actually find [huge amounts of virus, but] we found a lot of immune activation,” he says, particularly around blood vessels. The examinations suggested that immune cells called macrophages had been stirred up. “Macrophages are not that precise in their attack,” Nath says. “They come and start chewing things up; they produce all kinds of free radicals, cytokines. It’s almost like blanket bombing—it ends up causing a lot of damage. And they’re very hard to shut down, so they persist for a long time. These are the unwelcome guests” that may be causing persistent inflammation in the brain.
Determining which patients have ongoing inflammation could help inform treatments. Early research identified markers that often are elevated in people with the condition, says Troy Torgerson, an immunologist at the Allen Institute in Seattle. Three cell-signaling molecules—tumor necrosis factor alpha, interleukin 6 and interferon beta—stood out in long COVID patients. But this pattern wasn’t found in absolutely everyone. “We’re trying to sort through long COVID patients and say, ‘This would be a good group to take to trials of an anti-inflammatory drug, whereas this group may need to focus more on rehabilitation,’” Torgerson says. He led a study (currently released as a preprint, without formal scientific review by a journal) in which his team measured proteins from the blood of 55 patients. The researchers found that a subset had persistent inflammation. Among those people, they saw a distinct immune pathway linked to a lasting response to infection. “One subset of patients does appear to have an ongoing response to some virus,” Torgerson says.
Isolated pockets of SARS-CoV-2 or even pieces of viral proteins may remain in the body well after the initial infection and continue to elicit an immune attack. The first solid evidence for “viral persistence” outside the lungs came in 2021 from researchers in Singapore who found viral proteins throughout the gut in five patients who had recovered from COVID as much as six months earlier. A study conducted at the University of California, San Francisco, found evidence for viral particles in the brains of people with long COVID. Scientists collected exosomes, or tiny packets of cellular material, released specifically from cells of the central nervous system. The exosomes contained pieces of viral proteins as well as mitochondrial proteins, which may indicate an immune attack on those vital cellular organelles. Amounts of such suspicious proteins were higher in patients with neuropsychiatric symptoms than in those without them.
The virus could linger in the brain for months, according to research conducted at the NIH and reported in Nature in December 2022. The autopsy study of 44 people who died of COVID found rampant inflammation mainly in the respiratory tract, but viral RNA was detected throughout the body, even in the brain, as long as 230 days after infection. Two other studies, both published last year in the Proceedings of the National Academy of Sciences USA, showed evidence that SARS-CoV-2 may infect astrocytes, a type of neural support cell, gaining entrance via neurons in the skin lining the nose.
Researchers are examining inflammatory signals in patients with long COVID in increasingly fine detail. A small study led by Joanna Hellmuth, a neurologist at U.C.S.F., found that patients with cognitive symptoms had immune-related abnormalities in their cerebrospinal fluid, whereas none of the patients without cognitive symptoms did. At the 2022 meeting of the Society for Neuroscience, Hellmuth reported that she had looked at more specific immune markers in people with cognitive symptoms and found that some patients had an elevated level of VEGF-C, a marker of endothelial dysfunction. Higher VEGF-C concentrations are associated with higher levels of immune cells getting into the brain, she says, and “they’re not doing their normal function of maintaining the blood-brain barrier; they’re distracted and perhaps activated.” Although the studies are small, Hellmuth adds, they reveal “real biological distinctions and inflammation in the brain. This is not a psychological or psychosomatic disorder; this is a neuroimmune disorder.”
What keeps the immune system in attack mode? According to Torgerson, “one option is that you’ve developed autoimmunity,” in which antibodies produced by the immune system to fight the virus also mark a person’s own cells for immune attack. The response to the virus “turns the autoimmunity on, and that doesn’t get better even when the virus goes away,” he says. Several studies have found evidence of autoimmune components called autoantibodies that interact with nerve cells in people with long COVID.
Clues about the inflammatory processes at work could point toward treatments for neurological symptoms. “If it’s a macrophage-mediated inflammatory process … intravenous immunoglobulin could make a difference [to] dampen the macrophages,” Nath says. The treatment, referred to as IVIg, contains a cocktail of proteins and antibodies that can mitigate an overactive immune response.
IVIg can also be used to block autoantibodies. And a therapy called rituximab that targets antibody-producing B cells provides “a time-tested therapy for a lot of autoantibody-mediated syndromes,” Nath says. Another strategy is to use corticosteroids to dampen immune activity altogether, although those drugs can be used for only a limited time. “That’s a sledgehammer approach, and you can see if it makes a difference. At least it gives you an idea that, yes, it’s an immune-mediated phenomenon, and now we need to find a better way to target it,” Nath says.
If the virus does hang around in some form, antiviral medications could potentially clear it, which might help resolve neurological symptoms. That’s the hope of scientists running a clinical trial of Paxlovid, Pfizer’s antiviral drug for acute COVID.
A Chronic Fatigue Connection?
Postviral syndromes have been documented for more than a century, arising after infection with viruses from HIV to the flu. Epstein-Barr virus, which causes mononucleosis, is one of several viruses linked to a condition called myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), which is estimated to affect at least one and a half million people in the U.S. ME/CFS bears striking resemblances to long COVID, with symptoms such as immune system dysregulation, fatigue and cognitive dysfunction. “One of the patterns we see is patients who definitely meet the criteria for ME/CFS. This is something we are seeing and treating all the time” in long COVID patients, Pittman says. ME/CFS can be severe, with some people losing mobility and becoming bedbound.
Credit: Now Medical Studios; Sources: “Neurovascular Injury with Complement Activation and Inflammation in COVID-19,” by Myoung-Hwa Lee et al., in Brain, Vol. 145; July 2022 (blood vessel reference); “Olfactory Transmucosal SARS-CoV-2 Invasion as a Port of Central Nervous System Entry in Individuals with COVID-19,” by Jenny Meinhardt et al., in Nature Neuroscience, Vol. 24; February 2021 (nasal passage reference)
Nath, who also studies ME/CFS, says that “we think mechanistically they are going to be related.” Researchers suspect that ME/CFS, like some cases of long COVID, could be autoimmune in nature, with autoantibodies keeping the immune system activated. ME/CFS has been difficult to study because it often arises long after a mild infection, making it hard to identify a viral trigger. But with long COVID, Nath says, “the advantage is that we know exactly what started the process, and you can catch cases early in the [development of] ME/CFS-like symptoms.” In people who have had ME/CFS for years, “it’s done damage, and it’s hard to reverse that.” Nath speculates that for long COVID, if doctors could study people early in the illness, they would have a better chance of reversing the process.
Torgerson hopes that researchers will ultimately come to better understand ME/CFS because of COVID. “COVID has been more carefully studied with better technology in the time we’ve had it than any other infectious disease ever. I think we’ll learn things that will be applicable to other inflammatory diseases driven by infection followed by an autoimmune process.”
Team Treatment
Ghormley, after months of illness, sought care at UCLA Health’s long COVID clinic, among the country’s few comprehensive, multidisciplinary programs for people with this syndrome. Even though her symptoms are rooted in nervous system dysfunction, she needed an array of medical specialists to treat them. The clinic grew out of a program aimed at coordinating care for medically complex COVID patients, says its director Nisha Viswanathan, an internist and primary care physician. In following up with COVID patients after several months, she realized that “we had a group of patients who still had symptoms. There was no understanding around the condition; we were just trying to see what we could offer them.” Viswanathan and others convened a biweekly meeting of UCLA Health doctors in pulmonology, cardiology, neurology, psychiatry and other specialties to discuss individual cases and overall trends.
At UCLA Health, Pittman coordinates Ghormley’s treatment. He says the interdisciplinary team is crucial to getting patients the best possible care. “Oftentimes there are so many symptoms,” and some patients have seen multiple specialists before arriving, but not necessarily the right ones. As long COVID primary care providers, he says, “we do the initial testing and get them to the right person.” For Ghormley, that list of providers includes Pittman, along with a neurologist, a pulmonologist, a cardiologist, a psychiatrist, a trauma counselor, a rheumatologist and a gynecologist.
The team approach has also been critical for doctors trying to understand a brand-new disease, Pittman says. “It’s been a very interesting journey from knowing almost nothing to knowing a little bit now, and we’re learning more every day, every week, every month,” he says. The term “long COVID” “is an umbrella, and I think there are multiple diseases under that umbrella.” Although each long COVID patient is unique, Pittman says, “we start to see patterns developing. And with Ghormley, we saw a pattern of dysautonomia, which we see frequently.”
Dysautonomia impairs the autonomic nervous system, a network of nerves that branch out from the brain or spinal cord and extend through the body, controlling unconscious functions such as heartbeat, breathing, sweating and blood vessel dilation. For Ghormley, like many people with long COVID, dysautonomia takes the form of postural orthostatic tachycardia syndrome, or POTS. The syndrome encompasses a collection of symptoms that include a racing heart rate—particularly on standing—and fatigue, and it can cause bowel and bladder irregularities. POTS can also be a component of the exhaustion that comes with PEM. Although the symptoms may seem to affect the body, they stem from nervous system dysfunction.
Ghormley’s dysautonomia led her to see cardiologist Megha Agarwal at a UCLA clinic near her home. Many physicians are not familiar with POTS, but Agarwal is particularly attuned to it, having seen it in some of her patients before COVID hit. “There’s dysregulation of the nervous system, and so many things can cause it: some cancer therapies, viruses, autoimmune conditions.” Agarwal recognized POTS in Ghormley in the fall of 2020, when very little was known about long COVID. Now she believes “POTS is really what long-haul COVID is causing” in many patients. Luckily, Agarwal says, there are medical interventions that can help.
Tachycardia—the T in POTS—causes the heartbeat to speed up, contributing to exhaustion and fatigue in addition to stressing the heart itself. Drugs called beta-blockers (for the beta-adrenergic receptors they shut off in the heart) can lower the heart rate and improve symptoms. “When heart rate is controlled, not only does the pump improve,” Agarwal says, “[but people’s] energy improves, their fatigue is gone, and sometimes there’s better mental clarity.” For some patients like Ghormley, beta-blockers are not enough, so Agarwal adds a medication called ivabradine. “It’s a bit off-label, but it’s currently being aggressively studied” for POTS. For Ghormley, the combination led to real improvements, “so now she doesn’t feel like she ran the Boston Marathon when all she did was sit down and stand up at work or take a shower,” Agarwal says.
Among Ghormley’s toughest symptoms is her brain fog, a catchall term for a slew of cognitive problems that make it hard for her to function. For days when Ghormley works, her psychiatrist prescribes Adderall, a stimulant used to treat attention deficit hyperactivity disorder that helps her concentrate and stay focused. That has “helped immensely,” Ghormley says.
Ghormley credits her doctors and Agarwal in particular with doing the detective work to dig into her symptoms. “Nobody knew anything about it, but everyone listened to me,” Ghormley says. Perhaps because she was a professional from a medical field, no one “brushed me aside.”
That’s unusual for people with long COVID, many of them women, who are often dismissed by physicians who doubt their complaints are real. “Patients just don’t feel heard,” Viswanathan says. “I had a patient who told me everything, and after, I just said, ‘This must be so hard for you. I want you to know that everything you’re feeling is real, and I’ve seen so many patients like you.’ And she started crying. She said, ‘No one has told me that. I can’t tell you the number of times I was told it was in my head.’”
Credit: Now Medical Studio; Sources: “Postural Orthostatic Tachycardia Syndrome as a Sequela of COVID-19,” by Cameron K. Ormiston et al., in Heart Rhythm, Vol. 19; November 2022; “Long COVID-19 and Postural Orthostatic Tachycardia Syndrome—Is Dysautonomia to Be Blamed?” by Karan R. Chadda et al., in Frontiers in Cardiovascular Medicine; March 2022 (references)
In addition to drugs, other types of therapies, including physical therapy, can help improve some symptoms. But people who experience PEM face a particular challenge when using movement therapies. Pittman says the exertion can make these patients feel worse. “We don’t want patients to go to not moving at all, but sometimes the type of movement they’re doing may be flaring their symptoms.” He notes that often PEM strikes young, previously healthy people who will say, “‘I need to push myself,’ and then they go way too far and get worse. Our job is to try to find that middle ground and then make that consistent over time, so they’re not getting further deconditioned but they don’t have the PEM, which has been shown to set them back.”
The Long Haul
Some patients, Pittman says, “have the expectation that they’re going to come in, and within a month they’re going to be back to normal. And resetting those expectations can be really challenging. You have to be really empathetic because people’s lives have completely changed.” But sometimes patients’ quality of life can improve noticeably when they are able to adjust to a new normal. Still, he says, “patients have so many questions, and I can’t lead them down a physiological pathway. I can tell them there’s neuroinflammation, maybe there’s autoimmunity, but we still don’t have the answers. Sometimes it’s really tough for us to accept and for the patient to accept that we just have to try our best.”
A number of people, Viswanathan says, benefit from reducing various treatments they have accumulated. Some people become so desperate that they will try anything from supplements to off-label medications to untested potions from the Internet. Stopping those sometimes leads to improved symptoms, she says.
Psychological care and support groups can help. Lavretsky adds that “lifestyle choices can play a huge role in improvement,” particularly better sleep habits and the use of breathing exercises to control anxiety. She tells people their bodies can heal themselves if the patients and clinicians find the right tools.
Whether that’s true for everyone remains to be seen, Viswanathan says. “We see many patients who have gotten better with time. I have patients whose symptoms have disappeared in the course of a year, or they disappear and occasionally flare up again.” But for some, she says, “it could last many years.”
“We’re going to be addressing this for probably decades,” Viswanathan says. “COVID is not going to go away so much as we’re just going to get used to living with it, but part of [that] means that people will continue to develop long COVID.”
Vaccination appears to reduce the risk of long COVID. But a study published in May 2022 in Nature Medicine suggests the protection, though real, is not as good as one might hope. The survey of electronic health records from the U.S. Department of Veterans Affairs looked at the relatively small portion of vaccinated people who subsequently became infected. They developed long COVID only 15 percent less often than unvaccinated people. “These patients can have symptoms for one to two years or longer, and so every month you’re racking up more patients. Even if it’s 15 percent less, the total population of patients is still growing and exploding,” Pittman says. The best way to avoid getting long COVID, experts all agree, is to avoid getting COVID at all.
The syndrome is still mired in a lot of medical uncertainty. Patients might have one or a combination of the problems investigated so far: Long COVID might be caused by viral particles that persist in the brain or other parts of the nervous system. Or it might be an autoimmune disorder that lasts long after the virus has disappeared. Maybe overactive immune cells continue to perturb the nervous system and nearby blood vessels. Fortunately, the increasing ability to recognize specific problems is helping clinicians hone treatments that give patients the best chance of recovery.
Although Ghormley says her care has dramatically improved her symptoms and allowed her to “do some normal things again,” she continues to experience flare-ups that make it impossible for her to work for weeks at a time. One day last year she skipped a dose of her heart medication and made a Target run in the southern California heat. “I got home and basically collapsed in the hallway. Since then, everything has been out of whack. If I try to move around, my legs give out.” Most frustrating—and scary—to Ghormley is the unpredictability of her symptoms. “They have changed so much; some are manageable, some debilitating. One thing will get better, and another thing comes back. I’m always hopeful that it’s going to get better, but I just don’t know.”
I’ve read your advice to other people. I’ve suffered for a long time with my own financial and family problems. I would value your thoughts.
My younger brother developed a lifelong drug addiction when he was a teenager. My father, who grew up in an orphanage, provided him with financial support that enabled him to, as my brother once said, have a home and family while “being too drugged to ever see them clearly.”
He saw his whole world through a haze. He also said that getting off drugs was difficult enough, but because our parents were financially supporting his addiction, life became impossible for him. My father purchased some things for my brother, including a house and cars, but kept them in his name so my brother could not sell them.
But my father also created opportunities for my brother to steal from him. Sometimes he would send my brother to collect thousands of dollars from a customer, and the money would of course go missing.
“‘My father created opportunities for my brother to steal from him. Sometimes he would send my brother to collect thousands of dollars from a customer, and the money would go missing.’”
Another time he sent my brother to his house, where he had left several bank passbooks on a counter. These situations let my father claim that he had been robbed by my brother and that he was not giving my brother money to buy drugs.
This went on for decades. I often had nightmares that my brother needed me to rescue him, but I couldn’t figure out how to do it. Of course, I pleaded with my father many times. I even had thoughts of harming him to free my brother.
Once I called the district attorney’s office and begged for help, but I was told that no crime was being committed.
Question 1: What else could I have done?
After my father died, my mother continued this practice, with excuses like this one: “He calls me for money. He says it’s for medical bills or to pay gambling debts.” She told me, “I can’t say no to him.”
She distributed almost all of my father’s estate to his children. I used my own share and other savings to take advantage of a really good real-estate opportunity. I have a small pension and have lived very modestly for 5 to 10 years.
“‘Eight years after my father passed away, my mother asked me to return the money she gave me from my father’s estate. Of course, she really wanted the money for my brother.’”
Eight years after my father passed away, my mother asked me to return the money she had given me from my father’s estate. Of course, she really wanted the money for my brother. She said that she was at the end of her life and didn’t want to die penniless. I told her that I needed time to sell the land.
She became very angry with me, saying that I had enough money to live on and I should give her those funds. I explained that I had enough liquid assets to live off of for a few years, but that if I was to pay her back immediately, I would have to try to sell my real estate during the 2008 financial crisis.
I was in good health, close to 70 years old. I was planning to sell the property when the market recovered and use the funds to live on for the next couple of decades. Liquidating my investment in 2008 would have put me in poverty for the rest of my life.
My mother was always a very frugal woman, and even at an advanced age her intellect and personality had not changed. She would never imagine wanting to die holding a large amount of cash. It had to be my brother’s idea.
“‘My mother enlisted my sister and my son to help her. We all agreed that it was her money and I should return it. But they all felt I should give her the money immediately.’”
My mother enlisted my sister and my son to help her. We all agreed that it was her money and I should return it. But they all felt I should give her the money immediately, and that after that, my finances would be my problem.
Whether she wanted the money for herself or my brother didn’t matter to them. I felt that after holding the money for eight years, I should be given some time to liquidate the property efficiently, which I did. My mother remained angry with me for the remaining two years of her life.
Over the years, my brother frequently called me asking for money. I always told him I loved him, then turned him down. Once I agreed to meet him, but instead I took him to a good rehab center. He always appreciated me and told me he loved me. Not being able to help him was the curse of my life.
Question 2: What, if anything, should I have done differently regarding my mother’s request?
For years, my mother took her three children out to dinner at least once a year. After the main course, my mother would always order cake, ice cream or pie for my brother, who also had diabetes. He never asked for it, nor did he refuse it.
I’d get angry with my mother and protest that my brother had severe diabetes, which was already destroying the nerves in his feet. She, being obese herself, would respond that nobody had put me in charge of his diet and that he deserved some sweets just like the rest of us.
I always let it end like that until one dinner after my mother had died. I was visiting my hometown, and my sister and her husband invited my brother and me to dinner at their favorite new restaurant.
I was surprised that she invited my brother, but I was happy to see him. During the dinner she took charge of the ordering, even requesting a very expensive wine, thus making it clear that we were her guests, and she was paying for the evening.
“‘After the main course my mother would always order cake, ice cream or pie for my diabetic brother. He never asked for it, nor did he refuse it. I’d get angry with my mother and protest.’”
After the main course, she ordered dessert for herself and for my brother. I wanted to object again, but knowing that my objections didn’t matter when my mother was alive, I thought they probably still wouldn’t matter now that my sister was taking over.
Besides, the people who think it’s a good idea to give cake to a very sick diabetic person aren’t going to listen to what I have to say. So I yanked the plate of cake away from my brother. My sister became enraged. The whole family descended on me in a rage: “You come for a visit and think you’re taking over? He can decide for himself!”
Question 3: What should I have done at the dinner?
All I could say in my defense was that he’s my little brother, he’s sick and I need to protect him. In the days to come, my daughter and other family members all unanimously agreed that I was an evil, controlling person.
Only one person came up to me, hugged me, told me he loved me, and thanked me: my brother.
Sincerely,
A Brother and Son Who Tried to do the Right Thing
Dear Brother,
Let me answer your questions in reverse order.
You did what you did. When you’re dealing with a family member who has had a substance-misuse disorder for most of his life, and your family has chosen to enable, ignore or finance his addiction. You do not need to be forgiven for intervening. This was an act of frustration and pain decades in the making. We are all human. Your family’s history of acquiescence may go back not years, but generations.
Snatching the plate away was a minor infraction of dinner-party etiquette. Their response was totally out of proportion. Your family did not see red because you yanked away a plate with a piece of pie on it; they lost the plot because you addressed the elephant in the room — not your brother’s diabetes, but his long history of addiction and your family’s willingness to turn a blind eye to it.
Your brother has two diseases: addiction and diabetes. Your family’s creed was built on sweet desserts and secrets. You had the courage and the tenacity to unmask that. Your father enabled your brother, perhaps because he himself had not been given the tools to address the problem. Your mother stood by and then asked for your inheritance back to ensure your brother had enough money to live on.
Your sister, for better or for worse, is your mother’s daughter. She grew up with the same lessons: that the best thing to do was to ignore your brother’s addiction. Nobody in your family had the knowledge or capacity or, perhaps more accurately, the willingness to address this problem. Your sister played along, and she showed her love and support the only way she was taught to do.
“‘Your family did not see red because you yanked away a plate with a piece of pie on it. They lost the plot because you directly addressed the elephant in the room.’”
You have been held hostage by your brother’s disease and by your family’s unwritten rules and values. You found a rehab facility. But he had to want to get better, and he was the only one who could do it. You tried time and again. The dessert was the last straw. It’s never best to act out of frustration, but you did shine a big neon sign on decades of silence and facilitation. You broke their rules.
Regarding Question 2: You ask what else you could have done in response to your mother’s request. Of course, you could have said no. It was your money. But as your brother’s relationship with the rest of your family shows, this is not a family built on people saying “no” to others. It is a family based on “yes.” But always saying “yes” does not leave room for your own happiness. You did the best you could at the time.
As to Question 3: What else could you have done to protect your father from your brother? Your father may have felt under pressure to help your brother financially, but he was not under your brother’s care, and you do not cite any signs of emotional abuse, aside from the financial needs of a person who was in the throes of the disease of addiction and, perhaps, did not have a steady income.
You could have staged a family intervention, but you would have needed the cooperation of your/his family, or your brother’s friends. You did find a rehab facility for your brother, but he also needs to stay the course and want to get sober. You can’t live other people’s lives for them, and it’s a mistake to punish yourself for not doing enough for someone who could not or would not help themselves.
“You can use phrases like, ‘I will support you if you take this path.’ You are letting him know that you care about him, you want to help him, and you will be behind him 100{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} if he seeks the path of recovery. ”
No one thanked you for selling the land. Instead, your mother was angry that you did not do it on her terms — and, lest we forget, her anger helped persuade you to hand over the money. You stood by your brother, a man who acknowledged that one person at that dinner table was strong enough and bold enough to set a boundary in order to protect him. Forgive yourself for doing the best you could do.
You loved your brother, and you protested at how you believe your family enabled him. They acted as a tribe that does things their way. Your brother took drugs and he ate sweet desserts. Your family was beholden to his addiction and tied to the ways they have always done things. You attempted to break those rules. I’m not sure even Mahatma Gandhi could have succeeded where you did not.
We are all a product of our upbringing. The 12-step program Al-Anon has a very simple message for family members of people who have drug and alcohol problems — family members who have spent their lives putting other people first: “You didn’t create it, you’re not responsible for it and you can’t cure it.” But you can be there to offer your help, and let your brother know that you will support his recovery.
You can use phrases like, “I will support you if you take this path.” You are letting him know that you care about him, you want to help him, and you will be behind him 100{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} if he seeks the path of recovery. But you are making it clear that you do not support his ongoing misuse of substances. In the absence of a family intervention, continue to encourage your brother to seek treatment.
The Substance Abuse and Mental Health Services Administration, a branch of the U.S. Department of Health and Human Services, aims to help families dealing with addiction issues. It offers advice on how to start a conversation with a loved one: “1. Identify an appropriate time and place. 2. Express concerns, and be direct. 3. Acknowledge their feelings and listen. 4. Offer to help. 5. Be patient.”
If you, or a family member, needs help with a mental or substance use disorder, call SAMHSA’s National Helpline at 1-800-662-HELP (4357) or TTY: 1-800-487-4889, or text your zip code to 435748 (HELP4U), or use SAMHSA’s Behavioral Health Treatment Services Locator to get help.You can also find more resources and advice for families from SAMHSA here.
Here are other resources for people with family members who have addiction issues: The Center for Motivation and Change published this book, “Beyond Addiction: How Science and Kindness Help People Change.” Dr. Robert Meyers, who has been working in the field of addiction for four decades, developed the CRAFT approach to encourage a family member to engage in treatement.
Source: SAMHSA
You can email The Moneyist with any financial and ethical questions related to coronavirus at qfottrell@marketwatch.com, and follow Quentin Fottrell on Twitter.
Check out the Moneyist private Facebookgroup, where we look for answers to life’s thorniest money issues. Readers write in to me with all sorts of dilemmas. Post your questions, tell me what you want to know more about, or weigh in on the latest Moneyist columns.
The Moneyist regrets he cannot reply to questions individually.
More from Quentin Fottrell:
‘This has bugged me all my life’: My estranged father gave me $1,000 a month to buy a house in California. My brother cried foul, and told me to stop. Who’s right?
My stepmother has been less than ethical’: I suspect my stepmom removed me as beneficiary from my late father’s life-insurance policy. What can I do?
My mother cut me from her will and my sibling cashed out her annuity, on which I was a beneficiary. Should I sue?
Buffalo Bills gamers congregate on the subject by the ambulance following Buffalo Expenditures security Damar … [+] Hamlin (3) collapses through the NFL soccer activity involving the Buffalo Bills and the Cincinnati Bengals on January 2, 2023, at Paycor Stadium in Cincinnati, Ohio. (Picture by Michael Allio/Icon Sportswire via Getty Illustrations or photos)
Icon Sportswire by using Getty Pictures
By Arthur L. Caplan & Lee H. Igel
As the complete nation understands, Buffalo Payments basic safety Damar Hamlin stood up right after generating what appeared like a routine deal with on an opposing Cincinnati Bengals player during the first quarter of an NFL activity this earlier Monday night. A couple seconds later on, he wobbled on his feet and then collapsed. Club physicians and athletic trainers had been swift to the scene, where they and unexpected emergency health-related specialists started doing CPR, using an automatic external defibrillator to revive Hamlin’s coronary heart, and supplying other lifesaving treatment. The 24-yr-old was suffering cardiac arrest. Times afterwards, Hamlin remained hospitalized in vital situation.
The activity was remaining played in entrance of a stadium whole of 65,000 admirers and broadcast live by ESPN to hundreds of thousands of Monday Night time Football viewers throughout the United States. Players and staff—several of whom have been visibly shaken—could be witnessed forming a circle, praying and consoling each individual other. As it was becoming distinct that Hamlin’s issue was life-threatening, the tone in the stadium and on-air properly shifted absent from the recreation and towards humanity.
Healthcare staff worked for 9 minutes to stabilize Hamlin for transportation to the medical center. As soon as the ambulance carrying him was on its way, players from the two teams headed to their locker rooms. Payments mentor Sean McDermott and Bengals coach Zac Taylor, alongside with some gamers from both groups, achieved. A decision about continuing with the activity experienced to be designed. Together, they agreed that the emotion of the minute intended the recreation could not and shouldn’t go on. They informed the officiating crew and the leaderships of both the NFL and the NFL Players’ Affiliation. About one particular hour immediately after Hamlin collapsed, the NFL introduced that the activity would be postponed.
How could it take so extensive for the league to make that contact soon after these kinds of a terrifying episode had taken location? Does the league have a plan about a demise on the discipline or related with an harm if a participant goes to a medical center? If so, it should be transparent. Or else, it is uncomplicated to feel that the league was executing whatsoever it necessary for the exhibit to go on, to continue to keep on speed to meet up with Commissioner Roger Goodell’s goal of the NFL producing $25-billion in once-a-year earnings by 2027. Would that have happened if the coaches and players had not claimed, “That’s it,”?
In fact, the NFL was prepared.
There ended up all kinds of inquiries generating the rounds on social media when Hamlin was however being tended to on the field. By the pursuing morning, 1 set of them involved tweets and feeling columns arguing that this was a are not able to-glance-away case in point of how substantially the NFL prioritizes gains over players—so significantly so this time, they wrote, that Goodell should to be fired straightaway.
Speedy requires on breaking news are well-known these times. That is especially accurate when an intensive, psychological, and remarkable convert of events is transpiring. It is effortless to “Monday night time quarterback” or otherwise engage in passing judgement and criticism about how the NFL was controlling the scenario as it was unfolding. Lots of of those people performing so could very well have been drawing on their feelings that Goodell and the league will not do a great adequate work having care of lively and retired gamers who are dealing with the outcomes of concussions, mental well being fears, and other soccer-linked injuries.
But performing exercises some caution in this situation was warranted because of what appeared to be happening as opposed to what was essentially happening in the course of the throes of the crisis.
Accounts of the communication taking put while Hamlin was however getting procedure at the stadium present that his well being was foremost in everyone’s thoughts. There will not feel to have been much considered on anyone’s aspect about likely on with the game then or thereafter. The awareness, really, appears to have been on following the actions described in the Emergency Motion Prepare that had been created for a traumatic celebration in the venue.
For the previous ten years, before the commence of every season, the NFL has necessary each of its golf equipment to style and design, implement, and follow an Emergency Action Plan for their house stadium. Every single prepare is reviewed by the league, the players’ association, and independent advisors. The strategy grew in aspect out of the classes the league was learning about how to take care of concussions sustained by gamers in the course of online games.
Portion of any Unexpected emergency Action Approach consists of having a array of 30 healthcare professionals stationed to answer to incidents at a moment’s detect. It also features associations with nearby 1st responder and close by hospital trauma models. Yet another aspect is a meeting that takes place one particular hour prior to kickoff, at which the head doctor for the household workforce testimonials with clinical personnel and recreation officers the assets, communication networks, techniques, and devices offered for crisis response.
This past Monday night, the Emergency Motion System was activated when dependable staff noticed a human being encountering a healthcare crisis. Next its protocols on the field and in the stadium permitted health care specialists and functions team to focus on what they required to do to assist the afflicted person as finest they could under the situations. The concentration for anyone included on the inside of of the chain of events—from clinical team to team personnel to league and players’ association executives—was to make confident that they labored and communicated in methods that ended up already in place to give the injured particular person the greatest probability for survival. Next that, the transform could then be designed to informing the community.
The NFL and its golf equipment just take unexpected emergency organizing in venues significantly. It is, admittedly, driven in section by the many concussions and injuries associated with a violent activity. But the planning is there.
In addition to the Unexpected emergency Motion Designs, the NFL Rulebook outlines operational techniques for emergencies—whether by force of character or human-made—that threaten games and the venues they are played in. This aids make clear the lag in time amongst the general public recognizing the fact of Hamlin’s condition and obtaining word that the NFL was postponing the recreation. It is a functionality of setting up and problem for overall health, not profiteering.
Because of their system and that means to the general public, significant leagues have experienced to think-by way of postponing online games adhering to national and local tragedies that take place away from the field—the assassination of President John F. Kennedy, the 9/11 terrorist attacks, the Boston Marathon bombing, the Pittsburgh synagogue massacre among them. From time to time, the tragedies participate in out on the discipline, as happened on Monday evening or when, about 5 yrs back, Pittsburgh Steelers linebacker Ryan Shazier was transported off the industry after suffering a job-ending spinal damage for the duration of an NFL game. In all of these instances, some gamers, coaches, house owners, followers, and members of the media and broader public reasoned for a postponement even though other people managed that heading on with the online games asserts a feeling of “normalcy” and even heroism.
Decisions about no matter if, when, and how to resume video games following a disaster tumble on the means the decisions about them are introduced. It has a lot to do with the way that the alternatives are framed, that is, which positive and detrimental features are highlighted and the prospect of the achievable results. For the sake of Damar Hamlin’s daily life, arranging in progress was crucial.
Even though there is a large amount for the NFL to operate on about the challenges of the game, credit rating have to be specified for shifting from yesterday’s “rub some grime on it and get back in there” frame of mind to present-day considerably a lot more sophisticated player- and care-oriented plan.
Celia Koski of Westbrook has experienced long COVID considering that 2020. She has several indications and is participating in the Maine Professional medical Center’s research on the topic. Ben McCanna/Personnel Photographer
Celia Koski is never ever sure until she wakes up in the morning if she can make it to perform at her pores and skin treatment organization. Diagnosed with extensive COVID-19 in 2020, Koski has good and negative times.
“I never know working day to day whether I’m going to be in a position to perform or not,” claimed Koski, who suffers from symptoms including fatigue, “brain fog,” headaches, tremors, extreme joint agony and double eyesight. “It’s this kind of a strange disorder and it is so new. It is aggravating not owning the responses. But on the other hand, I recognize why they do not.”
The 65-yr-old Westbrook resident mentioned she tells her consumers up front that she may perhaps have to cancel appointments on small recognize. She’s also experienced to scale back again the full quantity of people she sees. Irrespective of the frustrations, Koski explained, she’s even now “very hopeful.”
Koski is Patient No. 22 in the Maine Well being Institute for Research’s examine of long COVID-19 individuals, which is part of the Nationwide Institutes of Well being Get better examine (Investigating COVID to Increase Restoration). The aim is to assistance scientists learn about extended COVID-19 and why some sufferers expertise symptoms months or even years immediately after becoming infected with the coronavirus. A better comprehension could guide to efficient treatment plans for long COVID, and some remedies previously are becoming tested in clinical trials.
It’s unclear how lots of folks have signs of extensive COVID – and to what extent. Estimates range from a minimal of 10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} to as lots of as 50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of folks who have been infected with COVID-19 have had indications that persist for months or a long time. Several estimates settle somewhere in the middle at 20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} to 25{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}.
Dr. Clifford Rosen, principal investigator for the Maine Wellbeing Institute for Investigation, claimed that the societal impacts of lengthy COVID are staggering, with several people owning to fall out of the workforce or significantly scale again how a lot they function.
Rosen and fellow researchers at MaineHealth, by means of the review, could be aspect of the remedy.
So considerably, 109 Maine patients are participating in the Recover review of 12,500 individuals nationwide, enrolled through the institute. Maine joined the Recuperate study in December 2021 – receiving a $1.5 million federal grant – and the to start with Maine people ended up enrolled this yr.
Scientists nonetheless never know the cause or will cause of prolonged COVID, but Rosen explained they are generating progress.
Dr. Clifford Rosen, of Maine Well being Institute for Investigation, is top the Very long COVID investigation work at Maine Wellbeing. Carl D. Walsh/Staff members Photographer
“One theory is that the virus is still there in the tissues, hiding out in the excess fat cells,” he claimed. “So people’s immune units are not really up to snuff for the reason that the virus has in no way been cleared.”
An additional risk is that the immune method is tricked into considering the virus is still current even when it is gone, producing immune reactions that make people today sense sick.
“One of the inquiries we are hunting to answer is regardless of whether the immune process (in extended COVID sufferers) is not performing its task effectively adequate or (is) performing its work also effectively,” Rosen reported.
He stated researchers also are hunting at irrespective of whether a spike protein on the coronavirus that has been detected in the blood of long COVID people up to a calendar year just after they are infected plays a role in how prolonged they go through from signs and symptoms. A further concept is that small blood clots identified as microclots could be producing the troubles.
As a individual in the Recover review, Koski has been through a collection of assessments and evaluations, which include genetic checks, blood exams, CAT scans, glucose measurements, bodily therapy assessments and neurological examinations. They are intended to establish a baseline of what sorts of signs persons are experiencing and aid attempts to find out why.
Celia Koski of Westbrook is even now hopeful scientists will uncover a way to ease her lengthy COVID indications. Ben McCanna/Team Photographer
“I consider to stay individual, and I’m hopeful that a little something is heading to operate,” Koski claimed.
Rosen mentioned there still is a good deal of disinformation out there about the COVID-19 vaccines and prolonged COVID. He stated 1 issue is sure: The vaccines do not add to lengthy COVID. Side outcomes from the vaccines, he stated, are scarce, pretty much always benign and solve promptly.
Remedy Analysis
On the therapy front, the Maine institute is taking part in two countrywide medicine research, of immulina and paxlovid.
Paxlovid is an antiviral that is now given within just five times of an infection, but Rosen stated it has possible for men and women suffering from very long COVID. Immulina is a normal complement – derived from an extract of blue-environmentally friendly algae – that aims to lower irritation and could probably simplicity indicators, Rosen explained.
“For people today who have extended COVID, there are these new research trials currently being began all the time,” he said. “There is hope.”
Dr. Cliff Rosen, of the Maine Well being Institute for Analysis, discusses Extensive COVID exploration with MIHR Supervisor of Physiology Care, Victoria DeMambro in the Scarborough lab. Carl D. Walsh/Personnel Photographer
A different medicine, naltrexone, confirmed promise this yr in a modest National Institutes of Wellness research of 52 sufferers who took a small dose, and will be investigated even more. Naltrexone is at present utilised to address opioid and alcohol use problems.
Koski stated she has been cleared to just take a very low dose of naltrexone starting up in January, and she hopes it increases her signs. Naltrexone is not aspect of the MaineHealth study.
A person myth that is continue to out there, Rosen said, is that ivermectin can simplicity extensive COVID symptoms. He said ivermectin, which is utilised to handle intestinal parasites – does not do the job and can be destructive.
Ready FOR Reduction
Whilst sufferers wait for productive treatments, their lives continue to be upended.
Dawn Summers-McDonald, 52, who is from Westbrook but has moved to Florida, claimed the long COVID signs and symptoms she has experienced since 2020 have “destroyed my programs for my long term.”
“I love to prepare dinner and I was contemplating of opening up a catering business enterprise,” she explained. Not only did she fall that system but she’s isolated. She does not socialize considerably, fearful of catching COVID-19 a 2nd time.
Gretchen Drown of Portland holds a self portrait she painted when she was extremely ill with COVID-19. Drown has been battling with lengthy COVID for two many years and has enhanced but continue to suffers with many symptoms. Gregory Rec/Team Photographer
Summers-McDonald does immunoglobulin therapy at the Mayo Clinic, and that has helped, but she continue to suffers from several indicators, which include blurred vision, numbness, a burning sensation on the skin and gastrointestinal problems.
“I quite substantially have had a sore throat each individual day for two many years,” said Gretchen Drown, a 57-calendar year-outdated Portland resident who is portion of the Recover study. “It will flare up and lower, but it practically never ever goes away.”
Drown, who has experienced from prolonged COVID due to the fact 2020, claimed her signs and symptoms have enhanced in excess of the past many months, but it is continue to exceptional that she goes a full working day without the need of having any. They consist of thoughts of euphoria and melancholy, nerve ache, insomnia and cognitive problems.
Drown believes the Get better analyze will be crucial to restoring her health. But she expects individualized treatment plans, not one particular that will work for absolutely everyone, will produce the greatest outcomes due to the fact persons with long COVID have this kind of a extensive selection of complications.
Gretchen Drown of Portland has been battling with long COVID for two yrs and has improved but however suffers with a lot of signs. Gregory Rec/Team Photographer
“There’s not nonetheless an knowledge of what is driving these indicators. This is heading to be so important,” Drown claimed. “This is going to be the facts set that all of our providers conclusion up relying on for decades to appear.”
For individuals with long COVID who live in Maine and want to share their activities, there is a support group on Facebook referred to as “C19 Long Haulers Maine.”
Invalid username/password.
Please verify your e-mail to validate and entire your registration.
Use the variety beneath to reset your password. When you have submitted your account electronic mail, we will mail an e-mail with a reset code.
« Preceding
Maine reports initial flu-relevant dying of baby this winter






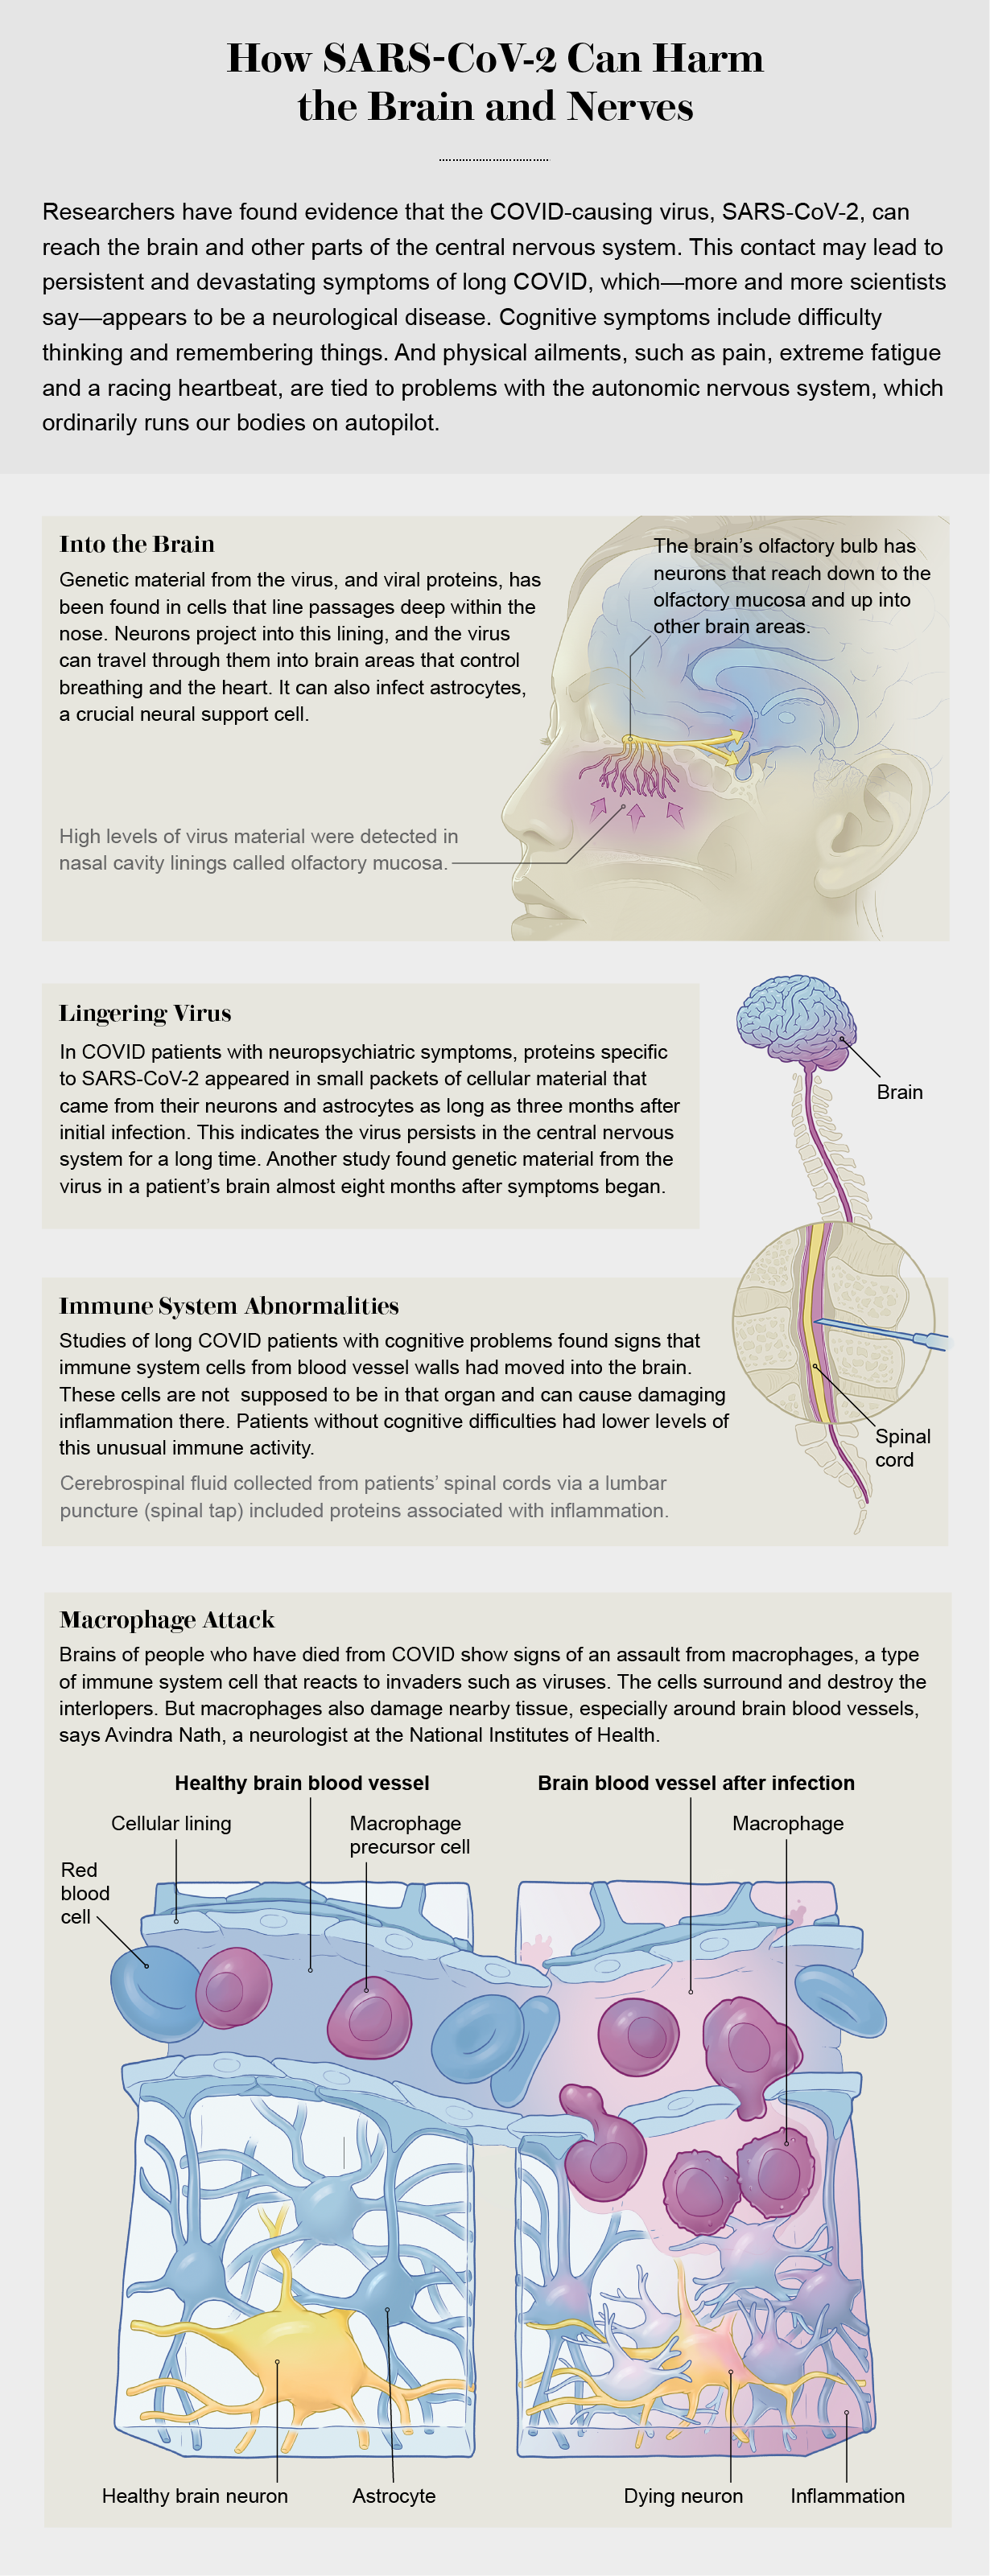
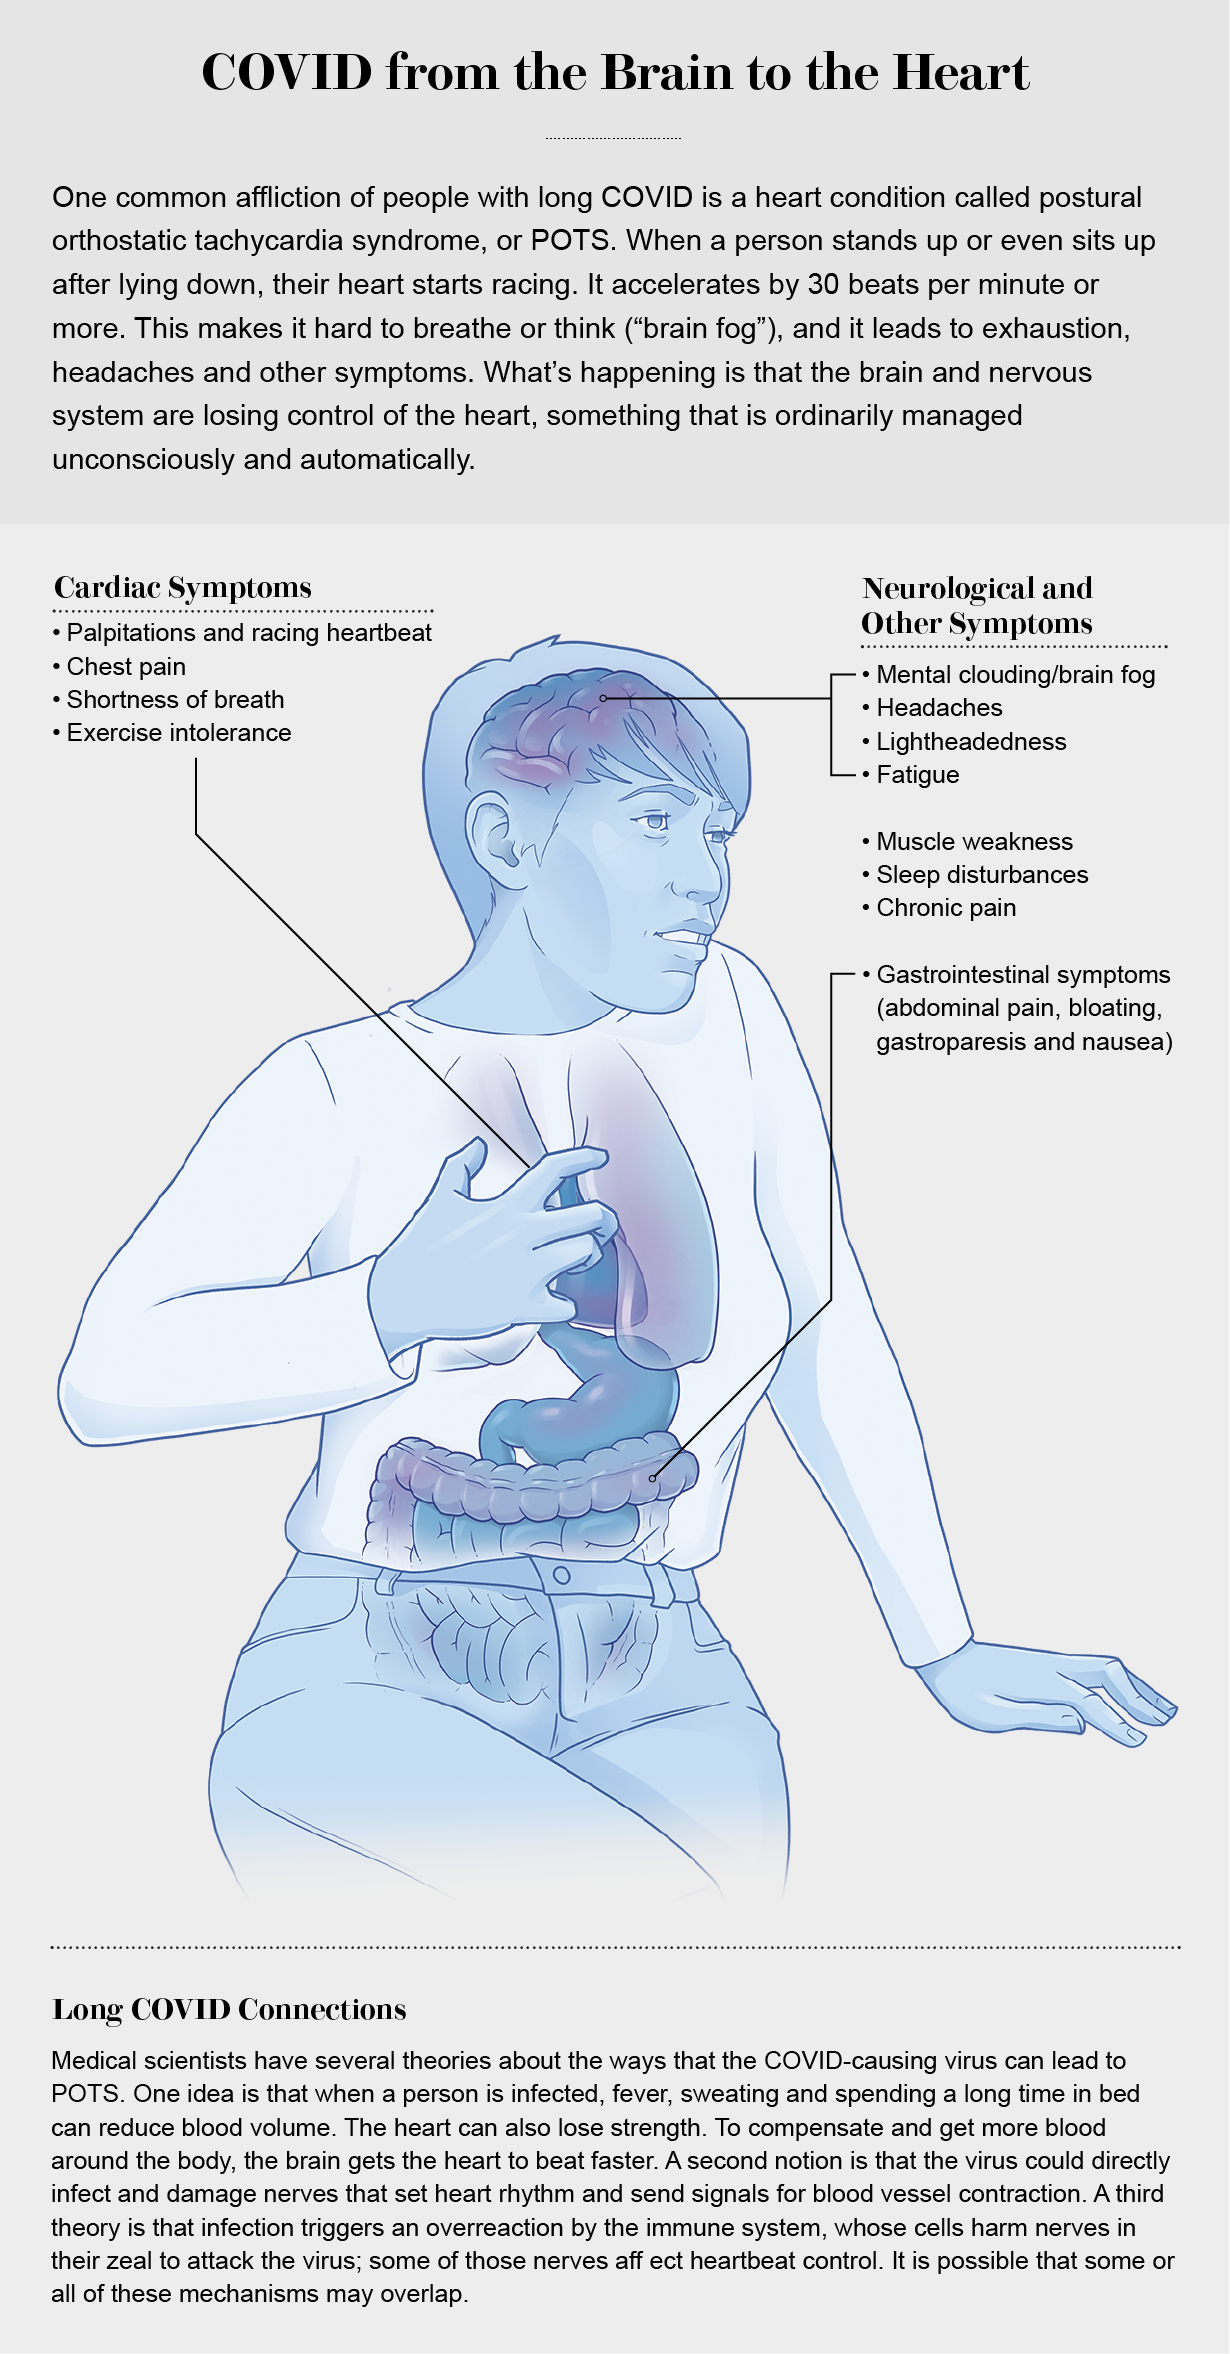





Invalid username/password.
Please verify your e-mail to validate and entire your registration.
Use the variety beneath to reset your password. When you have submitted your account electronic mail, we will mail an e-mail with a reset code.