Sharon Osbourne has shared a health update with her fans after being taken to the hospital last week.
The presenter and former X Factor judge was taken ill on the set of her son Jack’s new reality TV show Jack Osbourne’s Night of Terror on December 16. She was soon hospitalised for treatment.
“Back home and doing great! Thank you for all the [red heart emoji],” Osbourne wrote on her Instagram page, alongside a picture of her adorned Christmas tree and one of her dogs, husky Elvis.
Related: Simon Cowell teases new reality show with former X Factor contestant
Jack was the first to share more about his mother’s condition last Saturday, confirming she had been discharged after a day.
“She has been given the all-clear from her medical team and is now home. Thank you to everyone who has reached out with love and support,” he wrote on his Instagram Stories.
“As to what happened to my mum – I’m gonna leave it to her to share about when she is ready,” he added.
This content is imported from Instagram. You may be able to find the same content in another format, or you may be able to find more information, at their web site.
Related: X-Factor star James Arthur announces the birth of his daughter and reveals special name
Osbourne, who is married to Black Sabbath musician Ozzy Osbourne, was previously a co-host on The Talk.
Her stint on the show came to an end following a discussion about race with her former co-anchor Sheryl Underwood. The show was taken off the air while an investigation was carried out, but Osbourne decided to quit and was later replaced by Jerry O’Connell.
In other Osbournes news, MTV’s The Osbournes is getting revived on the BBC to mark the gang’s return to the UK.
Like the original show, it’s expected to follow Sharon and Ozzy and their children Jack and Kelly, though it isn’t clear whether daughter Aimée (who chose to be off-screen during The Osbournes) will feature.
Having a smartwatch has become part of our everyday tech needs. You can do anything with a smartwatch on without neglecting urgent notifications from your phone and, most especially, your health. And, the best part, unlike phones, you don’t have to hold it; it’s wearable. It is basically a handy device to wear anywhere you go and whatever you do.
Well, you probably know all that; that is why you are here! The next challenge is knowing which brands to buy among the many designs and features in the market today.
Smart watch vs. smart band
But before the best smartwatch picks, let’s first identify the difference between a smart band and a smartwatch, as they may be confusing, especially for first-timers, when you browse through the fitness trackers section online.
Smartwatches and smart bands are both fitness trackers that are wearable on your wrist. They share very similar functions and features, but smartwatches are more advanced. Smartwatches generally offer wider feature selections for users with their big screen, compatibility with smartphones and more. However, smart bands are only fitness-specific when it comes to their features [1].
Some particular general feature differences:
Smartwatches
Smart bands
Have a full touchscreen.
Function through buttons.
Can function independently, where you can text, call and reply to emails.
Dependent on a smartphone and usually have no SIM card insertions.
Have speakers that allow you to play music.
The majority have no speakers or microphones.
Best smartwatch to buy in 2023
Choosing the best smartwatch for you is a must! You should look for a design that suits your lifestyle and needs. We have come up with four best smartwatch brands in 2023 that you can consider before buying.
Despite its smartwatch nature, the Fitbit Versa 4 can’t compete with the best fitness tracking accuracy, at least at launch. For those comfortable with a mixture of surface-level smartwatch elements and harder-core fitness watches, its battery life is sound.
Display and style: There are many similarities between the Fitbit Versa 4 and the Versa 3. A square-faced watch with curved glass covering the screen. A plastic rear and aluminum bezel make up the device.
Although it has a less high-end design than the Apple Watch SE 2, it is clearly more style-driven than the Garmin Venu 2 Sq. While there aren’t many novel features here, there is one key difference from the last Versa 3.
Versa 4 has a physical button, while Versa 3 uses a quite annoying capacitive panel. It’s a bit cheap-looking, maybe because the casing is anodized and the button is glossy. Despite being made of metal, it feels like plastic. Still, a physical button is better than a capacitive one.
As with the Versa 3, the screen has 336 x 336 pixels. While the screen border of the watch is considerably larger than the Apple Watch Series 8, this isn’t too hard to forgive given the watch’s significant price difference. Likewise, the display is bright enough to look clear outdoors on a sunny day, and it is sharp and colorful.
Compatibility: Fitbit Versa 4 does not support WearOS, Google’s smartwatch platform. As a result, Fitbit OS’s classic interface has been redesigned in accordance with Google’s new style guidelines.
A widget-like screen displays each of the Fitbit Versa 4’s key features as you flick left and right. Among these are your daily steps, your heart rate over the past day, your sleep report, and the weather report.
You can access the notification cards by flicking up from the watch face. You can access core watch features like Do Not Disturb, screen brightness, and Always-on display mode by swiping down from the watch face. It is fairly simple, and Fitbit seems to have significantly reduced the lag of the Versa 3/Sense generation.
Usability and features: The watch is comfortable enough that you sometimes forget you’re wearing it, even with the model’s “over-under” watch strap style. Despite its size, it weighs only 40g all in, strap and watch face – which is remarkably light for a smartwatch.
The Apple Watch is among the most popular smartwatches on the market. There is no doubt that the Apple Watch SE is the best Apple Watch for most people, as it’s a lot more affordable than the Apple Watch 8, yet has most of its core features and even the same chipset as the Apple Watch 8.
Despite lacking an always-on display, an ECG, and blood oxygen tracking, the Apple Watch SE 2 has a wide range of health and fitness features as well as potentially lifesaving features like Car Crash Detection.
Additionally, it is very lightweight and comfortable, has impressive battery life for a smartwatch, and has a powerful display. So it strikes a superb balance between price and performance, and is a great relatively affordable pick.
Display and style: A 44mm or 40mm case size of 368 by 448 pixels with a Retina display of up to 1000 nits brightness.
It has a 100 percent recycled aluminum case. Redesigned, color-matched back case in a nylon composite material. Available in Midnight, Starlight and Silver. Ion-X front glass [2].
Compatibility: Despite the fact that the Apple Watch SE 2 is ideal for children and seniors who don’t have an iPhone thanks to Family Setup, it is also the most popular model among those who are new to Apple Watches and upgrading from a Series 3 or older model, as it offers a competitive price and generous feature set, allowing users to enjoy an unconstrained Apple Watch experience at an affordable price.
Usability and features: It features the same ‘S8’ processor as the Apple Watch Series 8, so it’s extremely responsive and snappy. In that sense, there’s no question that it feels like a cheaper Apple Watch – with the latest chip in there, it’s future-proof and performs everything as fast as it should.
Also, the watchOS 9 here is very similar to what you’ll find on the Watch 8 and Watch Ultra, except that it lacks some of the features that are tied to hardware, such as temperature sensing and pulse oxygen readings. The Action Button options on the Ultra are also not available.
Another smartwatch you should also buy in 2023–the AGPTEK LW11 smartwatch. This smartwatch has modern designs specified for men or women according to its colours.
Display and style: With the Galaxy Watch 5, we get to experience the same distinctive, contemporary design we saw in last year’s Watch 4. It’s a completely different experience if you are coming from a Galaxy Watch 3 or Watch 4 Classic. Instead of rotating bezels, you interact with an invisible digital bezel around the screen.
In case you are new to the Galaxy Watch line, the core watch screen is one side of a polished metal disc, while the reverse side has the heart rate monitor. On the right side, the two buttons, and the arms that connect the watch body to its bands, are held in place by a brushed aluminum frame that contrasts nicely with the polished disc.
Graphite (black), Pink Gold, or Silver are available on the smaller 40mm model, while Sapphire (a muted mid-tone blue) is available on the larger 44mm version. A wide range of color options is available with Samsung’s Bespoke service, available on samsung.com.
With bespoke, you can mix and match straps with watch bodies, and it goes beyond wearables, with the Galaxy Z Flip 4 allowing customers to customize their foldable. Once you’ve selected your case color, the Watch 5 comes with a wide range of bands – the Sports Band is the default band that ships with the Watch 5, while the 5 Pro has two D-Buckle Sports Bands, a Global Goals band, a Hybrid Leather band, a Ridged and Extreme Sports band, and a Milanese band.
A perpetual matte texture on the silicone band keeps the Watch 5 from tugging on your skin and is also hairy-wrist-friendly. When it comes to comfort, the Watch 5 is a soft landing for those who are unfamiliar with smartwatches. The default Sports Strap holds it in place, and it’s not too big.
Compatibility: Interacting with the watch is intuitive – swipes, taps, and button presses are all there is to it. Right-hand buttons have reassuring click feedback, and both the screen and digital bezel respond to touch.
Usability and features: While both Watch 5 sizes have bigger batteries (making them about 3 grams heavier), the Watch 5’s footprint hasn’t changed from the Watch 4. However, when compared with last year’s model, the Watch’s sensors poke out slightly more. In addition to accommodating the bigger batteries, Samsung claims this results in more accurate tracking.
In addition to IP68 certification against dust and water, the Watch 5 is swim-proof up to 5 ATM, and it has MIL-STD-810H approval to withstand tough conditions such as hard knocks, drops, and extreme temperatures.
Best Apple Watch for those who don’t mind spending on it
There is no comparison between the Apple Watch Ultra and its predecessors. Almost every part has been upgraded, and all for the better – in fact, it’s easily one of the best smartwatches out there.
Display and style: As a response to Garmin watches dominating the ‘premium fitness watch’ segment, Apple was forced to make the Watch this year – although it says it’s been years in the making. Featuring a new, more rugged design, a better screen and better GPS tracking, it’s the first design update in eight years – but it’s also incredibly expensive at $799.
Design changes are evident. It has a bigger, ridged Digital Crown for easier use when wearing gloves. You can see more information on the display than ever before, as it is nearly two inches across and much brighter than it was before.
The Watch Ultra has a significant upgrade: an Action Button. You can physically start and stop workouts by using the side button (although you can’t customise it as much as you’d like). This is a big orange symbol of change that the Apple Watch desperately needed.
Compatibility: The Apple Watch Ultra excels in fitness not because of its functionality – it has all the features offered by any Apple Watch running watchOS 9 – but because of its execution. GPS is more accurate and faster, and the heart rate monitor seems reliable. As a result, battery life is longer, so you can run longer and harder.
Additionally, there’s a diving sensor that you can use to see how deep you can dive into water. However, there’s more to come in terms of diving apps in the near future. If you like your current Watch for run or cycling tracking, then the upgrades here won’t disappoint.
Usability and features: Fitness isn’t the only upgrade: safety features are also genuinely useful. If you’re stuck on a hillside, the high decibel alarm will come in handy. In the event of an accident, the car crash detection will alert the emergency services.
Even the cellular functionality on board makes you feel safer – knowing that if you’re ever in distress (and in range of a cell tower), you’re never alone. Also included are health functions that monitor your heartbeat and blood oxygen – yes, they’re included in every new Apple Watch, but they still make a compelling case for purchasing the device.
Nevertheless, there are still some bugs to be worked out. There is no native mapping navigation onboard – not in terms of Maps, as that app is available. Instead it uses a compass, which isn’t always the best option for tracking back.
The battery proved to sustain over 30 hours in testing, but is still awfully short when compared with Garmin and Coros. Those watches can last for days in standby, while Apple’s push for functionality has a high cost in battery life.
Currently the most advanced multi-sports watch from Garmin
As Garmin’s most advanced multi-sports watch to date, the Fenix 7’s new training tools are geared toward a broader range of athletes. Battery life has dramatically improved with no additional weight, and the enhanced touchscreen is a bonus for browsing menus. Only the absence of a microphone stands out, but most people will get by without it.
Display and style: The Fenix 7 comes in three sizes: 42 mm, 47 mm and 51 mm – in standard, Solar and Sapphire Solar varieties.
Garmin has chosen to use a transflective memory-in-pixel display on the Fenix 7 instead of an AMOLED screen, as on the Venu 2 and Epix watches. While it’s not as bright as we’d like, it’s a sensible choice that conserves battery life.
Compatibility: In addition to five physical buttons and a touchscreen, the Fenix 7’s interface will be immediately familiar to users of the Fenix 6. During activity tracking, the touchscreen will automatically lock to keep from pausing or cancelling activities accidentally.
If you prefer to use only the buttons, you can disable the touchscreen completely. Additionally, it can be switched off during sleep to prevent accidental touches at night, but we did not find this to be a problem.
Usability and features: The Fenix 7 is equipped with a number of sensors, including Garmin’s Elevate 4 optical heart rate monitor, an altimeter, a compass, SpO2 (blood oxygen) sensors, and a temperature sensor.
Monitoring SpO2 can take place continuously, over night, or during spot-checks only. As with the Fenix 6, the Fenix 7 has a feature that alerts you if you move your wrist too much while it is taking an SpO2 reading.
Garmin’s Fenix 7 line delivers great battery life, which has always been one of its selling points. It’s important to note, though, that the life of each watch will be determined by its battery size, solar cell size, and solar cell type.
With Garmin’s Power Glass, the Fenix 7 Sapphire Solar (in particular) harvests energy throughout the day to keep the watch’s battery charged. You’ll still need to plug the watch in occasionally, but the solar cell extends its battery life significantly.
To clarify, you cannot charge the watch only with solar power. As a result, the battery drain is reduced. Watches cannot be left in the sun all day and expect it to be fully charged when you collect them at night. What you use it for and which sensors you enable will determine how often you have to recharge it.
In addition to its slick exterior, the Google Pixel Watch offers smooth operation and powerful, useful features. You’ll love it despite some notable quirks.
Display and style: The Google Pixel Watch is a beautiful smartwatch that combines metal, chrome and glass in a way that is rarely seen in smartwatches. The design is both subtle and supportive, giving the wearable’s relatively small screen (1.2-inch, 450 pixels x 450 pixel) the best opportunity to shine.
In comparison, that display is almost half the size of Apple Watch 8. Google’s Pixel Watch arrives with a shockingly thick black bezel between the circular display and the metal chassis, where Apple has been working to reduce the bezel around its watch face and extend the screen to the very edges of the Iox-X glass over the last seven years.
As opposed to Apple’s wearables, Google’s Pixel Watch is available in just one size: 41mm. As per Google’s representatives they said, variety of band styles should make this mid-range size a convenient fit for most people, as you get two sizes of band in the box.
Compatibility: If you pair the Google Pixel Watch with the Google Pixel 7 Pro (or Pixel 7 or any Android phone running version 8.0 or above), notifications will appear automatically or you can summon them with a swipe up. Smart home controls, maps, directions and (some) apps are available.
Additionally, it’s a capable health and fitness wearable, though the Fitbit integration makes it somewhat awkward. In comparison with Fitbit, which Google bought last year, Pixel Watch tracks exercise and exercise intensity separately.
Usability and features:
Google’s Pixel Watch is an attractive wearable device. In addition to being eye-catching, it is also useful. This is a fantastic partner for Google’s new Pixel 7 phones.
Like other wearables, the Google Pixel Watch will remind you to stand, walk around, and get all of your steps in for the day. The wearable nanny culture is old, but the Pixel Watch can help those who need reminders.[1]
The information included in this article is for informational purposes only. The purpose of this webpage is to promote broad consumer understanding and knowledge of various health topics. It is not intended to be a substitute for professional medical advice, diagnosis or treatment. Always seek the advice of your physician or other qualified health care provider with any questions you may have regarding a medical condition or treatment and before undertaking a new health care regimen, and never disregard professional medical advice or delay in seeking it because of something you have read on this website.
Women’s access to health care is shaped by a broad range of factors, including coverage and income, the availability of health care providers in their communities, and the affordability of care and health insurance.
The Affordable Care Act (ACA) has expanded pathways to affordable coverage to millions of women by broadening eligibility for Medicaid and providing subsidies to make individual health insurance coverage more affordable for those who do not have access to coverage through their employer. The ACA also contains provisions aimed at alleviating some of the financial barriers to health care; however, many women still face challenges with health care costs and medical bills, particularly those who are uninsured or have low incomes.
This report presents findings from the 2022 KFF Women’s Health Survey (WHS) on women’s health status, use of health care services, and costs. The WHS is a nationally representative survey of 5,145 self-identified women ages 18 to 64, conducted May 10 – June 7, 2022. See the Methodology for more details.
Summary of Findings
The majority of women ages 18-64 report being in excellent, very good, or good health (82{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}); however, nearly one in five (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women describe their health as fair or poor, with substantial differences by sociodemographic characteristics.
Half of women (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report having an ongoing health condition that requires regular monitoring, medical care, or medication and 18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} report having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities, with higher rates among older women. Ten percent of women with a disability or ongoing health condition do not have a regular doctor or health care provider.
Nearly all women ages 18-64 (95{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have seen a doctor or health care provider in the past two years, but a smaller share has had a general check-up or well-woman visit (73{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Uninsured women are significantly less likely than insured women to have seen a provider or had a check-up in the past two years.
Overall, women have more interactions with and connections to the health care system than men. Higher shares of women report having a usual source of care and have visited a health care provider in the past two years than men.
Most women (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) obtain their health care at doctors’ offices, but health centers and clinics are common sites of care for underserved populations. One in four (25{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) uninsured women, one in five (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) Hispanic women, and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those with Medicaid usually visit health centers or clinics for their routine health care.
Most women ages 18-64 (60{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say they have had a telemedicine visit in the past two years. Most (69{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate the quality of care they received via telemedicine as comparable to in-person care. Annual check-ups, minor illnesses and injuries, and mental health services were the top reasons women accessed services via telemedicine.
Many women with health insurance report experiencing limitations with their insurance in the past 12 months. One in five (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women with Medicaid say that their plan did not cover care they thought was covered, or paid less than expected, compared to one-third (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women with employer-sponsored coverage.
More than one in four (27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women ages 18-64 report having had problems paying medical bills in the past 12 months compared to 23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men.
Among women experiencing problems with medical bills in the past year, more than half (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have had difficulty paying for basic necessities like food, heat, or housing because of the bills, including nearly seven in ten (68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women with low incomes.
Health Status and Use of Prescription Medications
Health Status
The majority of women ages 18-64 report being in good or excellent health, but substantial shares of women with low incomes and those with Medicaid describe their health as fair or poor.
Most women ages 18-64 (82{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as excellent, very good, or good; however, 18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women describe their health as fair or poor, similar to other national estimates.
A higher share of women ages 36-49 (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and ages 50-64 (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as fair or poor than those ages 18-35 (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 1). A larger share of Black (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Hispanic (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women report being in fair or poor health than White (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women. (Persons of Hispanic origin may be of any race; other groups are non-Hispanic.) Approximately three in ten women with low incomes (28{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and women with Medicaid coverage (30{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as fair or poor. (This survey defines low income as household income under 200{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of the federal poverty level (FPL); higher income is 200{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} or more of the FPL. The federal poverty level (FPL) for an individual in 2022 is $13,590.) A higher share of women with Medicaid describes their health as fair or poor than women with employer-sponsored insurance (11{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), individual insurance (13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and the uninsured (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
Many women are managing ongoing health conditions or living with disabilities that impact daily life.
Half (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women ages 18-64 report that they have an ongoing health condition that requires regular monitoring, medical care, or medication (Figure2). This rate increases with age, from 41{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 18-49 to 65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50-64. Smaller shares of Hispanic (41{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (38{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women report having an ongoing health condition than White (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Black (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women. More women with employer-sponsored insurance (46{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report having an ongoing health condition requiring regular care than do uninsured women (36{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women with Medicaid (53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are more likely than those with employer-sponsored insurance or the uninsured to report having an ongoing condition.
Eighteen percent of women ages 18-64 report having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities (Figure 3). Women ages 50-64 are more likely than those ages 18-49 to report having a disability or chronic disease (24{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Lower shares of Hispanic (14{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (6{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women have a limiting disability or chronic condition than do White (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Black (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women. Women with Medicaid coverage (30{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those with low incomes (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are more likely than their counterparts to report having a disability or chronic disease.
Almost two-thirds of women ages 18-64 take at least one prescription medication, including birth control pills, on a regular basis.
Women may take prescription medications to treat or manage chronic conditions and acute illnesses or to prevent pregnancy. Sixty-three percent of women report taking at least one prescription medicine, including birth control pills, on a regular basis (Figure 4).
Prescription medication use increases with age, with 58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 18-49 taking at least one on a regular basis compared to 73{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50-64. White women (68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are more likely than Asian/Pacific Islander (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Hispanic (55{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and Black (58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women to take a prescription medication on a regular basis. As may be expected, a higher share of women in fair or poor health report taking a prescription medication regularly than women in excellent or very good health (76{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 54{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Even though more uninsured women (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as fair or poor than insured women (17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), a higher share of insured women (65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (data not shown) report taking take a prescription medication than uninsured women (43{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). One explanation for this could be that uninsured women have less access to health care and affordable medications than those with insurance, which could result in lower use of prescription medications.
Differences Between Women and Men
In measures of health status and prescription drug use, there are some differences and some similarities between women and men.
More women than men report having an ongoing health condition that requires regular monitoring, medical care, or medication (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 43{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), or taking at least one prescription medication on a regular basis (63{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 48{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 5). The share of women and men who rate their health status as fair or poor is similar (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} and 20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}, respectively), as is the share who report having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}, respectively). (People of all genders, including non-binary people, were asked these questions; however, there are insufficient data to report on non-cisgendered people.)
While the vast majority of women have a regular provider they turn to for routine care, only half of uninsured women have a usual source of care.
Having a usual source of health care is associated with increased use of preventive care and better health outcomes. Eighty-two percent of women have a regular doctor or health care provider they see when they are sick or need routine care. The share of women who have a regular provider increases with age (Figure 6). Hispanic women (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are slightly less likely than White (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Black (84{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women to have a usual source of care. Fewer women who are uninsured (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those with low incomes (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report having a usual source of care than their counterparts. Women who live in a state that expanded Medicaid are more likely to have a usual source of care than women in states that have not expanded Medicaid (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (data not shown). Ten percent of women with a disability or an ongoing health condition do not have a regular doctor or health care provider (data not shown).
Most women obtain their health care at doctors’ offices, but health centers and clinics are common sites of care for underserved communities, particularly for uninsured women, those with Medicaid, and Hispanic women.
Eighty-two percent of women have a regular doctor or place they usually go for health care. Among them, eight in ten (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report that they usually obtain their care at a doctor’s office (Figure 7). Ten percent obtain care at an urgent care or retail clinic; 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} usually go to a health center or school-based clinic; and 3{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} cite the emergency room or some other place as their usual site of care.
More women ages 50-64 (88{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), White (84{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women, women with higher incomes (85{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and those with private health insurance (86{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rely on an office-based physician for their regular care than their counterparts (Table 1). (Private health insurance includes employer-sponsored insurance and individually purchased insurance.) Health centers and clinics play a larger role as sites of care for women ages 18-49 (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Hispanic women (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), women with low incomes (15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), those with Medicaid (17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and uninsured women (25{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) than their counterparts.
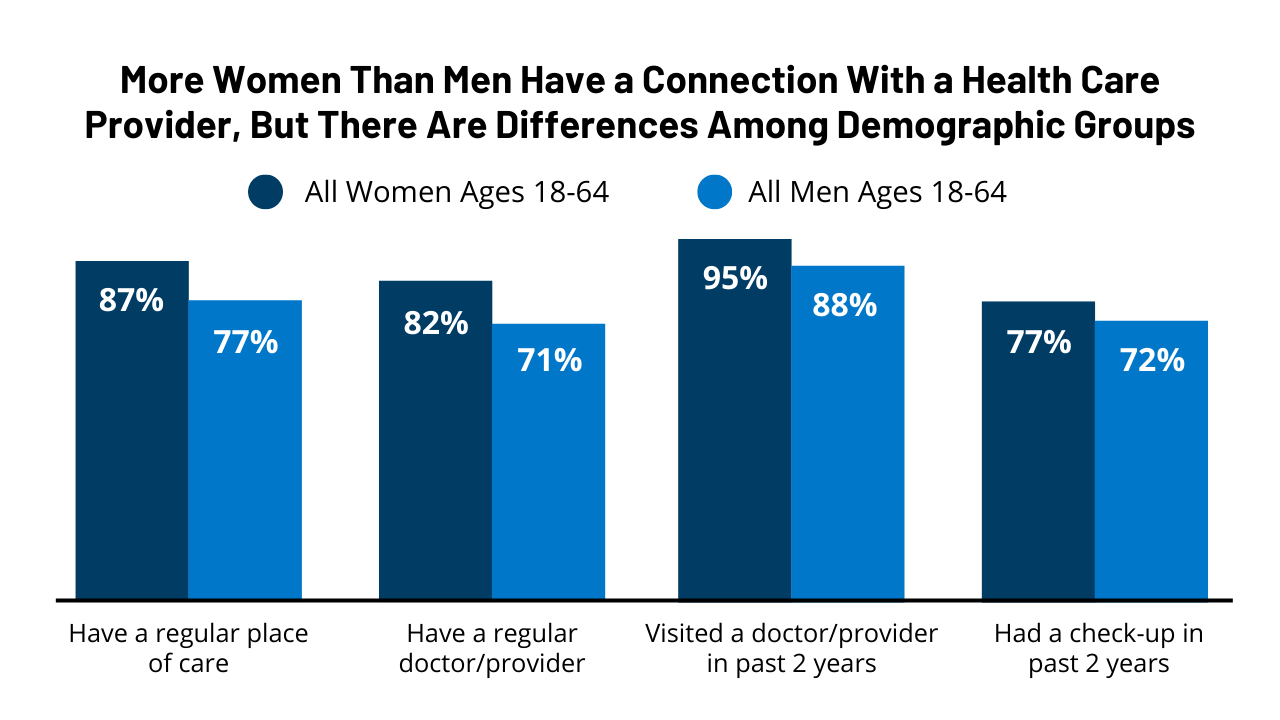
Overall, women have more interactions with and connections to the health care system than men. Higher shares of women than men report having a usual source of care and have visited a health care provider in the past two years.
Women are more likely than men to report having a regular place of care (87{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and a regular doctor or health care provider (82{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 71{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 8). Ninety-five percent of women say they have visited a health care provider in the past two years and among them, 77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} have had a check-up, compared to 88{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} and 72{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men, respectively. (People of all genders, including non-binary people, were asked these questions; however, there are insufficient data to report on non-cisgendered people.)
While most women ages 18-64 have visited a doctor in the past two years and had a check-up, rates are lower among younger women and uninsured women.
Nearly all women (95{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have seen a doctor or health care provider in the past two years (Figure 8). However, fewer women ages 18-35 (92{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Hispanic (92{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and uninsured women (78{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have visited a doctor in the past two years than their counterparts.
Among women who have seen a health care provider in the past two years, more than three-quarters (77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have had a general check-up/well-woman visit during that period. However, a smaller share of uninsured women (61{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and women with low incomes (74{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) had a recent check-up than their counterparts. A smaller share of women ages 18-35 had a check-up than women ages 50-64 (72{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 85{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and more Black women than White women had one (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
Two years into the pandemic, most women ages 18-64 (60{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say they have had a telehealth visit(Figure 9).
Smaller shares of younger women report having had a telehealth visit in the past two years and fewer than half of uninsured women say they have had one. Women living in rural areas are less likely than those living in urban areas to have had a telehealth visit with a health care provider (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) in the past two years, a general trend that has been documented in otherstudies. This could be due, in part, to patient preferences as well as more limited access to reliable high-speed internet and technology among those living in rural areas than in urban/suburban areas, as has been documented by other research. Slightly fewer women living in Medicaid non-expansion states have had a telehealth visit than those in expansion states (58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). There were no statistically significant differences by race/ethnicity (data not shown).
Among women ages 18-64 who had a telehealth visit in the past two years, nearly two in ten (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say the primary purpose for their visit was for an annual check-up or well-visit, minor illness or injury, or mental health services (Table 2). The next most common reasons included management of a chronic condition (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), another health concern not listed (13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), COVID-related symptoms (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and gynecological or sexual health issues (5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
Primary reasons for telehealth visits often vary by age. Among women ages 18-25 who had a telehealth visit in the past two years, three in ten (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say the primary purpose for their most recent telehealth visit was mental health services, compared to just 10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50-64. Almost one-quarter (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women ages 50-64 say their most recent telehealth visit was for management of a chronic condition, compared to 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 18-25. Among women ages 18-49 who had a telehealth visit in the past two years, 2{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say prenatal or postpartum care was the primary purpose for the most recent telehealth, including 2{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those ages 18-25, 4{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those ages 26-35, and 5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those ages 36-49 (data not shown).
Most women (70{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say the quality of care they received at their most recent telehealth visit was similar to the quality of in-person care, with 12{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} saying their telehealth care was better and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} saying it was worse than in-person care (Figure 10). Larger shares of women with low incomes (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those who are uninsured (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their telehealth care was better than in-person care than women with higher incomes (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those with private insurance (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Two percent of women who had a telehealth visit in the past two years say they have not had an in-person visit for this type of care.
When looking at specific types of services provided via telehealth, one in five (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women receiving telehealth services for a gynecological or sexual health issue or mental health services say the care they received via telehealth was better than in-person care (Figure 11). Conversely, about one in five women say their telehealth care for treatment of minor illnesses and injuries (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and COVID-related symptoms (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) was worse than in-person care. Among women ages 18-49 who had a telehealth visit in the past two years and whose most recent visit was for prenatal or postpartum care, 18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} said the quality of care was better than the quality of in-person care, 65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} said it was the same, and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} said it was worse (data not shown).
More insured women than men report having experienced problems with their insurance covering needed health services or medications in the past 12 months.
Thirty-one percent of women ages 18-64 with health coverage (employer-sponsored insurance, individual insurance, or Medicaid) report that in the past 12 months, they or a family member received care from a doctor, hospital, or lab they thought was covered, but their health plan did not cover the bill at all, or paid less than they expected, compared to 26{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men who say the same (Figure 12). More insured women than men say their plan would not cover a prescription medication or required a very expensive copay or coinsurance for it (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women were slightly more likely than men to say that in the past 12 months, their plan would not cover a test or scan that their doctor recommended (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
These gender differences could be due to several factors, including that women are more likely than men to have visited a health care provider in the past two years, to take prescription medication on a regular basis, and to have an ongoing health condition that requires regular monitoring, medical care, or medication (see “Health Status and Use of Prescription Medications” section above).
Some of these insurance coverage problems vary by type of insurance plan (Table 3).
For example, among women, more women with private insurance (individual or employer-sponsored plans) (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) than women with Medicaid (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their plan did not cover medical care they thought was covered, or paid less than expected, in the past 12 months. A higher share of women with individual coverage (35{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) than women with employer-sponsored coverage (27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) or Medicaid (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say that their plan did not cover a prescription medication or required high cost sharing for it. Women with individual coverage (28{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are also more likely than women with employer-sponsored coverage (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) or Medicaid (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) to report their plan did not cover a test or scan their doctor recommended in the past 12 months.
Insurance companies sometimes deny coverage of prescription medications or require large co-payments, but many women are not aware that they can appeal coverage decisions.
The ACA requires that most private health insurance plans have an appeals process for coverage determinations and claims. State Medicaid programs are also required by federal law to have an appeals process. Among the 65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of insured women who take a prescription medication on a regular basis, only four in ten (40{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are aware that they can ask their insurance company to reconsider covering the cost of a prescription, known as filing an appeal (Figure 13).
Knowledge of this option varies by income level and insurance type. More low-income women with insurance who take a prescription medication are aware that they can file an appeal with their health plan than higher-income women (44{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 38{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women with Medicaid are also more likely than those with employer-sponsored insurance to know that this is an option (45{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 38{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
Many women who take a prescription medication say their out-of-pocket costs for those medications have increased over the past year.
Among the nearly two-thirds (63{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women ages 18-64 who take a prescription medication on a regular basis, almost one-third (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their out-of-pocket costs for those medications have increased compared to 12 months ago (Figure 14). Over half (54{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their out-of-pocket costs have stayed the same, 6{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say their costs have decreased, and 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say they do not know.
Changes in out-of-pocket costs vary by type of insurance coverage. Fifty-five percent of women who are uninsured and who take a prescription medication say that their costs have increased compared to 12 months ago, compared to 34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women with private insurance and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those with Medicaid. Most women with private insurance (53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Medicaid (63{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say that their out-of-pockets costs for their prescription medications has not changed in the past year. Notably, twice as many women with Medicaid (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) who take a prescription medication say they do not know how their out-of-pocket costs for those medications has changed, compared to 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of all women. (Four percent say they were not taking any of these medications 12 months ago; they are not included in this analysis.)
While the ACA has addressed some financial barriers to accessing health care, many women, including those with insurance, still report problems paying medical bills. Some women incur significant medical expenses because of an unexpected diagnosis such as cancer, or an illness or injury that limits their ability to work and earn income to pay off bills. Costly medical bills can also arise after receiving care from an out-of-network provider, commonly referred to as surprise medical bills. (The No Surprises Act, which took effect in January 2022, establishes new federal protections against surprise medical bills.)
More than one in four women ages 18-64 report having had problems paying medical bills in the past year, with higher rates among uninsured women and women in poorer health. (Poorer health refers to those who report being in fair or poor health.)
Twenty-seven percent of women report that they or a household family member has had problems paying medical bills in the past 12 months, a slight increase from 2020 (24{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Problems paying medical bills are more common among women than men (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
Outstanding medical bills are more common among uninsured and women with low incomes and those in poorer health (Figure 15). This includes more than two in five (42{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) uninsured women and women in poorer health, and almost two in five women with low incomes (37{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Approximately one-third of women who live in states that did not expand Medicaid (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Black (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Hispanic women (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) also report having trouble paying medical bills in the past 12 months. Women who live Medicaid expansion states are less likely than those in non-expansion states to have had trouble paying medical bills (data not shown). More women with children report problems paying medical bills in the past 12 months than do women without children (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 25{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
Among women who report having had problems paying medical bills in the past 12 months, one-third (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say it was because they or someone in their family lost a job, income, or unemployment benefits. Seventeen percent say it was because they or someone in their family had health expenses related to COVID-19. The majority (66{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women who say they have had trouble paying medical bills in the past 12 months report that it is due to some other reason (Figure 16).
Medical bills can have serious consequences for people’s financial well-being and ability to afford basic necessities. Although more women than men report having problems paying medical bills in the past 12 months, women and men experience financial consequences because of the bills at similar rates.
Among the 27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men who have had problems paying medical bills in the past 12 months, similar shares have had to set up a payment plan to pay off the bill (65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men); used up all or most of their savings (62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 69{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men); been contacted by a collection agency (61{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 56{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men); and had difficulty paying for basic necessities (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men) (Table 4). However, a higher share of men than women with recent problems paying medical bills report borrowing money from family or friends (53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 42{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
For women, the financial consequences of medical bills vary by income level (Figure 17).
Among the 27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women who report having trouble paying medical bills in the past 12 months, women with low incomes are more likely than women with higher incomes to report having difficulty paying for basic necessities such as food, heat, or housing (68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 39{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}); having been contacted by a collection agency (70{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}); or borrowing money from family or friends (56{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women with higher incomes are more likely than women with low incomes to have had to set up a payment plan with a doctor or hospital (71{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 59{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
Women’s access to and use of health care services has an impact on their health outcomes. Most women report having a regular source of care and having had a recent doctor’s visit. However, connections to the delivery system are more tenuous for uninsured women and women with low incomes, who are less likely to report a recent visit or regular place of care. Most women report they have had a general check-up/well-woman visit in the past two years, but like other measures on access to care, rates are lower among uninsured women and those with low incomes. When looking at gender differences, women are more likely to have regular connections with the health care system than men.
The COVID-19 pandemic has changed how some people access health care, particularly a shift from in-person care to increased use of telehealth. Federal and state policy changes and market forces also contributed to the growth in the use of telehealth. Most women say they have used telehealth in the past two years, and most of them rate the quality of care they received as comparable to an in-person visit. This pattern is consistent for all types of telehealth services our survey asked about, ranging from check-ups to mental health care services. While many women do not express concerns about quality differences between telehealth and in person care, the extent to which this newer modality will continue to be utilized and grow will also depend on the reimbursement policies that private plans and public payors adopt following the end of the pandemic emergency.
Despite the role that health insurance plays in helping people afford health care and reducing patients’ financial risks when they need routine care, get sick, or need to be hospitalized, scope of coverage and affordability can still be challenging for many women with insurance coverage. A sizeable minority of women with insurance report having problems using their health plan, such as their plan not paying for health care they thought was covered but was not, or their plan not covering their prescription drugs or requiring high cost sharing for them. Many people say they have had problems paying medical bills in the past year, bur rates are higher among women than men. While the ACA strengthened access to coverage and offers protection from some out-of-pocket health care costs, gaps remain. For many, health care and coverage are still unaffordable and represent potential barriers to needed care.
The U.S. Authorities Accountability Office environment (GAO) has appointed seven new members to the Health and fitness Facts Know-how Advisory Committee (HITAC), such as wellness details exchange executives, a individual advocate, and two main healthcare details officers.
The 21st Century Cures Act, enacted in December 2016, set up HITAC and gave the Comptroller Normal obligation for appointing at least 14 of the associates. In addition, 11 customers are appointed by the Secretary of Wellbeing and Human Products and services, the The vast majority and Minority leaders of the Senate, and the Speaker and Minority Chief of the Residence of Representatives. The committee delivers recommendations to the Nationwide Coordinator for Health and fitness Information and facts Technological innovation on policies, expectations, implementation requirements, and certification standards relating to the implementation of a wellbeing data technological know-how infrastructure that advances the electronic access, trade, and use of wellness data.
“HITAC is composed of persons committed to increasing the digital entry, trade, and use of wellness facts. Each individual 12 months, several fantastic candidates specific an curiosity in serving on the committee,” claimed Gene L. Dodaro, Comptroller Standard of the United States and head of the GAO, in a statement.
The new appointees are:
• Kikelomo Belizaire, M.D., M.P.H., M.B.A., is the Chief Medical Officer at Pegasystems, exactly where she supports the company’s industry alternatives for wellbeing methods, health designs, and lifestyle sciences companies. Dr. Belizaire is also a working towards hospitalist in the Charlotte, North Carolina spot. She formerly served as the health-related director of Anthem’s professional device, as a medical doctor dealing with high-acuity clients in a number of different clinic devices in North and South Carolina, and as a healthcare guide.
• Shila Blend, Ph.D., M.S., is the Health and fitness Details Engineering Director of the North Dakota Well being Information Community, North Dakota’s statewide wellbeing details trade. She also serves as a issue make a difference skilled with the Rural Emergency Health care Solutions Counts challenge, which is working to develop high quality actions for emergency health-related solutions in rural regions. Previously, she served in a amount of positions with the condition of North Dakota, which include as the Deputy Main of Staff for COVID-19 reaction, as the Director of the Medical center Preparedness System, and as Coordinator for the state’s stroke and cardiac systems of care.
• Hannah Galvin, M.D., is the Chief Health-related Info Officer of Cambridge Wellness Alliance, an educational general public safety web wellbeing technique, wherever she qualified prospects the Division of Scientific Informatics and practices as a pediatrician. She also retains an assistant professorship as a result of Tufts College Faculty of Medication. Dr. Galvin is the co-chair of the board of directors of Change, an independent process power targeted on enabling clients to handle how their very own sensitive well being info are shared to promote equitable interoperability. Beforehand, Dr. Galvin was the Clinical Director of Informatics at Lahey Health, Senior Manager of Scientific Efficiency at athenahealth, Inc., and practiced at various hospitals in Massachusetts, New Hampshire, and Rhode Island, the place her medical concentration was on caring for underserved and vulnerable populations.
• Bryant Thomas Karras, M.D., is the Main Medical Informatics Officer and Senior Epidemiologist with the Washington State Office of Wellness, in which he guides informatics and overall health information and facts interoperability attempts. He has led numerous state endeavours, like those relevant to advertising and marketing widespread adoption of wellbeing info know-how, early detection of condition outbreaks, patient immunization histories, prescription drug checking, and COVID-19 exposure notification. Beforehand, Dr. Karras was a study scientist and assistant professor with the University of Washington, and an inner medication health practitioner at a variety of hospitals in Connecticut, Oregon, Washington, and Wisconsin.
• Anna McCollister is a individual advocate, entrepreneur, and advisor on a variety of wellbeing know-how, data use, and well being care excellent initiatives. She delivers her practical experience as a affected person with form 1 diabetes to each individual of these routines. Ms. McCollister has served on a quantity of nationwide committees, including on a Foodstuff and Drug Administration advisory committee concentrated on endocrinologic and metabolic medication, and on a Nationwide High-quality Discussion board committee on high-quality steps for principal care and serious illness. She was also the Chief Advocate for Participatory Study at the Scripps Translational Science Institute and served as a marketing consultant to lifestyle sciences, pharmaceutical, and biotechnology consumers.
• Deven McGraw, J.D., M.P.H., is Direct for Info Stewardship and Knowledge Sharing at Invitae Corporation, a health care genetics organization. She co-launched and was the Main Regulatory Officer of Ciitizen, a overall health technological know-how business obtained by Invitae that will work to enable people to acquire, manage, and share their healthcare information. Her previous encounter includes serving as the Deputy Director of Health Facts Privateness in just the Department of Wellbeing and Human Companies Business office of Civil Rights, as the Performing Chief Privacy Officer for the Office of the Countrywide Coordinator for Health and fitness IT, and as a partner with Manatt, Phelps & Phillips, LLP.
• Naresh Sundar Rajan, Ph.D., M.S., is a Chief Info Officer at CyncHealth (previously identified as the Nebraska Health Details Initiative), wherever he leads health and fitness data trade knowledge and modernization initiatives. He also serves to aid the specialized architecture for the exchange of prescription drug checking info by means of the Prescription Checking Info Exchange Standards Group, and on a neighborhood advisory board to aid foster health-associated research in Terrific Plains states with significant rural and underserved communities. Before becoming a member of his latest organization, he worked for the condition of Utah on analytics to share details on treatment prescriber methods, and for the state’s Violence and Damage Prevention Application
We include products we think are useful for our readers. If you buy through links on this page, we may earn a small commission. Here’s our process.
How we vet brands and products
Medical News Today only shows you brands and products that we stand behind.
Our team thoroughly researches and evaluates the recommendations we make on our site. To establish that the product manufacturers addressed safety and efficacy standards, we:
Evaluate ingredients and composition: Do they have the potential to cause harm?
Fact-check all health claims: Do they align with the current body of scientific evidence?
Assess the brand: Does it operate with integrity and adhere to industry best practices?
We do the research so you can find trusted products for your health and wellness.
A vegan or plant-based diet excludes all animal products, including meat, dairy, and eggs. When people follow it correctly, a vegan diet can be highly nutritious, reduce the risk of chronic diseases, and aid weight loss.
Increasing numbers of people are moving toward vegan diets due to health, animal welfare, or environmental concerns. A 2018 Gallup poll reports that about 3{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of people in the United States are fully vegan and notes that sales of plant-based foods are rising.
Vegan diets tend to be rich in nutrients and low in saturated fats. Research suggests that the diet can improve heart health, protect against cancer, and lower the risk of type 2 diabetes.
However, people eating only plant-based foods need to be more aware of how to obtain certain nutrients, including iron, calcium, and vitamin B-12, that usually come from an omnivorous diet.
In this article, we take a close look at the vegan diet, including its health benefits and risks, as well as important things to consider before trying it out. We also provide recipe ideas and tips for following a vegan diet.
A vegan diet involves eating only foods comprising plants. Those who follow this diet avoid all animal products, including meat, dairy, and eggs. Some people also avoid eating honey. For some, being vegan is a dietary choice, while for others, it is a lifestyle choice.
People who choose to live a vegan lifestyle may also avoid clothes, soaps, and other products that use or contain parts of animals, such as leather and animal fur. Some adopt this lifestyle for its environmental benefits as a sustainable diet.
Vegan diets tend to include plenty of fruits, vegetables, beans, nuts, and seeds. Eating a variety of these foods will provide a wide range of important vitamins, minerals, healthful fats, and protein.
People following this diet should, however, take care to get key nutrients that people usually consume in animal products. These nutrients include iron, protein, calcium, vitamin B-12, and vitamin D.
The main difference between vegetarians and vegans is that although vegetarians do not eat meat (including cows, pigs, chicken, and fish), they consume dairy products, eggs, or both. The vegan diet excludes all products with animal-based ingredients.
The vegan diet is more restrictive, so people will need to think more about where their nutrients are coming from to ensure that they meet their daily dietary requirements.
Read more about vegan vs. vegetarian diets here.
Vegan diets can provide all of the nutrients that a person needs, and they can eliminate some of the possible risks that research has associated with harmful animal fats. Research has linked the vegan diet with a range of health benefits, including those below.
Better heart health
Vegan diets can boost heart health in several ways.
A large scale 2019 study has linked a higher intake of plant-based foods and lower intake of animal foods with a reduced risk of heart disease and death in adults.
Animal products — including meat, cheese, and butter — are the main dietary sources of saturated fats. According to the American Heart Association (AHA), eating foods that contain these fats raises cholesterol levels. High levels of cholesterol increase the risk of heart disease and stroke.
Plant foods are also high in fiber, which the AHA link with better heart health. Animal products contain very little or no fiber, while plant-based vegetables and grains are the best sources.
In addition, people on a vegan diet often take in fewer calories than those on a standard Western diet. A moderate calorie intake can lead to a lower body mass index (BMI) and a reduced risk of obesity, a major risk factor for heart disease.
Lower cancer risk
According to a 2017 review, eating a vegan diet may reduce a person’s risk of cancer by 15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}. This health benefit may be due to the fact that plant foods are high in fiber, vitamins, and phytochemicals — biologically active compounds in plants — that protect against cancers.
Research into the effects of diet on the risk of specific cancers has produced mixed results.
However, the International Agency for Research on Cancer report that red meat is “probably carcinogenic,” noting that research has linked it primarily to colorectal cancer but also to prostate cancer and pancreatic cancer.
The agency also report that processed meat is carcinogenic and may cause colorectal cancer.
Eliminating red and processed meats from the diet removes these possible risks.
Weight loss
People on a vegan diet tend to have a lower body mass index (BMI) than those following other diets.
The researchers behind a 2015 study reported that vegan diets were more effective for weight loss than omnivorous, semi-vegetarian, and pesco-vegetarian diets, as well as being better for providing macronutrients.
Many animal foods are high in fat and calories, so replacing these with low calorie plant-based foods can help people manage their weight.
It is important to note, though, that eating lots of processed or high fat plant-based foods — which some people refer to as a junk food vegan diet — can lead to unhealthful weight gain.
Read more about the vegan diet and weight loss here.
Lower risk of type 2 diabetes
According to a large 2019 review, following a plant-based diet can reduce the risk of type 2 diabetes. The research linked this effect with eating healthful plant-based foods, including fruits, vegetables, whole grains, nuts, and legumes.
A vegan diet removes some sources of nutrients from the diet, so people need to plan their meals carefully to avoid nutritional deficiencies. People may wish to talk to a doctor or dietitian ahead of adopting a vegan diet, especially if they have existing health conditions.
Key nutrients that may be low in a vegan diet include:
Vitamin B-12: Vitamin B-12 is mainly present in animal products. It protects the nerves and red blood cells. Plant-based sources of this vitamin include fortified cereals and plant milks, nutritional yeast, and yeast spreads. Read more about vegan sources of vitamin B-12.
Iron: Iron is important for blood health. Beans and dark leafy greens are good sources. Find out more about iron-rich vegan foods.
Calcium: Calcium is crucial for bone health. Eating tofu, tahini, and leafy greens will help keep calcium levels up. Learn about calcium-rich plant-based foods.
Vitamin D: Vitamin D protects against cancer and some chronic health conditions, and it helps strengthen the bones and teeth. Regularly eating vitamin D-fortified foods and spending time in the sun can boost vitamin D levels.
Omega-3 fatty acids: Important for heart, eye, and brain function, there are three types of omega-3 fatty acid: EPA, DHA, and ALA. Walnuts and flaxseeds are good sources of ALA, but seaweeds and algae are the only plant sources of EPA and DHA. Read about how to get omega-3 as a vegan.
Zinc: Zinc is important for the immune system and the repair of DNA damage. Beans, nutritional yeast, nuts, and oats are high in zinc. Read about zinc-rich vegan foods.
Iodine: Iodine is important for thyroid function. Plant-based sources include seaweeds and fortified foods.
A person may wish to ask for their doctor’s advice on whether to take supplements or consume more fortified foods.
Shop for supplements
A vegan diet may be low in specific nutrients. Certain specialized foods and dietary supplements can help people meet their daily requirements. People can choose from a variety of brands online.
The change from an unrestricted diet can seem daunting, but there are many simple, tasty, and nutritious ways to pack a vegan diet with key vitamins and minerals.
Instead of cow milk, people can use plant-based alternatives. Compared with cow’s milk, plant milks tend to be lower in calories and contain less saturated fat. Manufacturers often enrich them with vitamins and minerals.
People can also buy plant-based cheeses, yogurts, and butters or make their own. Read about dairy alternatives here.
Some people may have concerns about meeting their protein needs on a vegan diet, but many plant foods are excellent sources of protein. Read about the best plant-based sources of protein.
Soy products — such as tofu, tempeh, and seitan — provide protein and also add a meat-like texture to many dishes. Learn more about meat substitutes here.
Vegan recipes often use the following nutritious foods in place of animal products:
tofu
tempeh
mushrooms
potatoes
jackfruit
eggplant
lentils
beans and legumes
cauliflower
nuts
peanut butter and other nut butters
beets
People can find a huge variety of vegan recipes online. Some examples include:
There are plenty of sweet vegan recipes online, too:
It may take a little experimentation, but most people will be able to find a vegan meal plan to suit their taste.
Vegan diets are growing in popularity. A vegan diet can offer many health benefits, including better heart health, weight loss, and a reduced risk of chronic diseases.
Research also suggests that vegan diets are better for the environment.
People who wish to adopt a vegan diet will need to plan their meals carefully to ensure that they are getting enough key nutrients to avoid deficiencies.
Sharon Osbourne took to Instagram on Monday to share with her followers that she’s “again property and accomplishing terrific” right after the 70-year-aged was rushed to the medical center subsequent a clinical unexpected emergency.
Osbourne shared an image of her pup sitting down in entrance of a Christmas tree. She also thanked all people for all the love.
On Saturday, Santa Paula Law enforcement Main Don Aguilar verified to Fox News Digital that Osbourne was rushed to the medical center immediately after a clinical unexpected emergency Friday evening.
Ventura County Fireplace Office advised Fox News Electronic that their crew responded to a “health-related connect with” at Glen Tavern all over 6:30 p.m. Friday and transported a person affected person to Santa Paula Clinic.
Pursuing the news, Osbourne’s son Jack Osbourne shared an update on his mother’s problem Saturday.
The 37-year-old television identity certain lovers that the former talk display host was now at dwelling following remaining “provided the all obvious from her health-related team.” He also resolved reports that Sharon was filming an episode of the Travel Channel’s “Ghost Adventures” when she professional a medical emergency.
SHARON OSBOURNE Says ‘MY Coronary heart BREAKS’ FOR Husband OZZY After PARKINSON’S Prognosis
“Ok, in this article is what I am going to say – very first factors very first MY Mother Was not FILMING AN EPISODE OF @ghostadventures,” Jack wrote in a put up on his Instagram story on Saturday. “She was filming an episode of Evening of Terror with me. Hahaha.”
He continued, “Now that we have designed that clear…She has been offered the all distinct from her healthcare crew and is now home. Thank you to everybody who has attained out with like and assist.”
Sharon’s professional medical crisis will come on the heels of a hard yr for the Osbournes. Her partner Ozzy, 73, unveiled he has Parkinson’s disorder in January 2020 and underwent major surgical procedure this past June. (Gregg DeGuire/Getty Photos for The Recording Academy)
“As to what happened to my mum – I’m gonna leave it to her to share about it when she’s ready.”
Sharon’s medical crisis comes on the heels of a hard calendar year for the Osbournes.
Her husband Ozzy, 73, discovered he has Parkinson’s disorder in January 2020 and underwent major surgical treatment this earlier June.
She spoke out about her husband’s complicated operation throughout a modern visual appeal on her British isles chat clearly show Speak Television set.
Sharon at the time also disclosed that this course of action was “really going to decide the relaxation of his everyday living.”
Sharon Osbourne also stepped down as host of “The Converse” previous year. (Getty Photos)
Thankfully, Ozzy expressed that he had designed considerable improvements in his wellness because going through the main operation.
Click Here TO Indication UP FOR THE Enjoyment Publication
Married given that 1982, the Osbournes have entered a new stage of their connection considering that the former Black Sabbath star has been identified with Parkinson’s sickness. In a vulnerable interview on the ITV show “Paxman: Putting Up With Parkinson’s,” Sharon shared, “When I look at my husband, my coronary heart breaks for him.”
She admitted in October, “Out of the blue, your lifestyle just stops, life as you realized it.”
The Osbournes, who celebrated their 40th marriage ceremony anniversary a few months back, have been candid about the struggles they have confronted in the previous numerous decades, both professionally and individually.
Sharon reluctantly still left her job final year as a host of “The Discuss.”
Typical views of Glen Tavern Inn in Santa Paula, California in which Sharon Osbourne fell sick whilst filming. (Coleman-Rayner for Fox News Electronic)
Ventura County Fire Division informed Fox News Electronic that their staff responded to a “professional medical phone” at Glen Tavern around 6:30 p.m. Friday and transported one affected individual to Santa Paula Hospital. (Coleman-Rayner for Fox Information Electronic)
In modern several years, Ozzy has endured numerous well being scares due to his issue and has had to appreciably alter how he spends his times.
Simply click Here TO GET THE FOX Information App
In addition to Kelly and Jack, the couple also share daughter Aimee. Ozzy also has Louis and Jessica from his prior relationship to ex-spouse Thelma Riley.
Fox Information Digital’s Stephanie Giang-Paunon and Ashley Hume contributed to this report
Janelle Ash is an enjoyment writer for Fox Information Digital.