Healthcare Access and Equity: Women’s Health and Technology Hold the Keys

Healthcare Access and Equity: Women’s Health and Technology Hold the Keys

Although the quality of U.S. healthcare and individual results has typically greater above time, obtain to treatment — and hence to favourable affected person outcomes — is not equitable to all persons. Over-all, one particular in 10 Individuals do not have health insurance coverage, which is fallout of a process breaking less than the excess weight of higher expenditures and deepening complexity.

Diabetes prices are a lot more than 30{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} increased among Indigenous People in america and Latinos than among the Whites. Charges of loss of life attributable to coronary heart illness, stroke, and prostate and breast cancers keep on being a lot larger in black populations.

If you dwell in a rural spot and have a chronic disorder (or various ailments) supplier possibilities are extra restricted than in densely populated spots. That suggests availability of a expert or even the capability to get an appointment can be a problem.

There are a lot of other variables that effects health care obtain and equity: socioeconomics, engineering, gender, language obstacles and extra. These things are even more complex by an individual’s precise care demands.

Just set, men and women with out adequate health care coverage protection or proximity to good quality treatment really do not have the similar prospects to access treatment and their all round wellness may be adversely affected.

Building points even worse, the U.S. healthcare method carries on to be extremely complicated to navigate and is fraught with administrative load. When it is a lot easier and a lot quicker to accessibility most primary human demands than it is to check out a care company, transform is necessary. In the search for significant solutions to these inequities, women’s overall health and technological financial investment are obvious sites to begin.

The scenario for greater entry

Nevertheless the U.S. health care program does have its faults, we are a global chief in investigation, teaching, treatment criteria, and scientific results. According to the World Index of Health care Innovation, the U.S. healthcare method ranked sixth for innovation in 2021 but third to very last in fiscal balance. Which is what will make obtain and fairness concerns disheartening. As treatment vendors, collectively we know we can be performing more for a lot more patients if our programs produced delivery and obtain to treatment less complicated.

In an excellent earth, sufficient entry to healthcare would imply that all people is capable to get the treatment they need to have in a timely method and in a way that supports their most effective particular final result. That contains viewing a company quickly and at a sensible price tag. Greater access to preventive treatment would have an exponential benefit for people and for the healthcare method as a total. Skipped prevention opportunities alone value the U.S. $55 billion every single yr. When thinking about actual physical therapy as a frontline musculoskeletal intervention, analysis displays up to 26{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} expense personal savings at over $1500/patient.

Accessibility challenges are not minimal to checking out a medical professional. Frontline and preventative wellness expert services this kind of as physical remedy are also compromised. As Medicare reimbursement premiums for ancillary companies these as PT proceed to decrease, providers and individuals are caught in the conflict. Our objective is to assist persons sustain and get back again to their very best actual physical wellbeing though jogging a  national practice that relies on margin growth to battle macro traits and devote for the future.

Access follows reimbursement and the services lined by insurance policy corporations. If providers are not able to produce services in business enterprise restrictions, contraction of expert services may perhaps consequence. Enterprise versions reliant on economies of scale may possibly be compelled to withdraw from a lot more rural and distant regions where by demand from customers for services is limited. That signifies even significantly less entry for people today in rural communities, and the cycle proceeds.

Alternatively, if decreased reimbursement is passed together to people in the form of larger rates or out-of-pocket price tag, less folks will find or be equipped to afford care, further more restricting entry for the uninsured and the underinsured. When faced with spending constrained house pounds on food and housing vs. non-urgent medical care, the treatment will get rid of out each time — resulting in a less healthy populace.

Make women’s wellbeing a precedence

Women comprise fifty percent the world’s inhabitants but account for 80{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of buying decisions in the healthcare industry. And nonetheless, women’s health and fitness is regarded a area of interest market place and a subset of health care. Endorsing women’s wellbeing is the single most impactful alter we could make as girls engage in a disproportionate job in how and when others access care.

When I was at Brigham and Women’s Clinic, I observed firsthand that improving upon the well being of all ladies could boost the health of an overall group or inhabitants. As advisors to a lot of on where and when to acquire treatment, we hardly ever admit the strong influence and affect girls have on the common wellbeing of their family members and acquaintances. Sad to say, quite a few gals generally put the care of other folks ahead of their individual.

In our roles as mothers, daughters, companions and far more, we normally care for other individuals and have to have to do the exact for ourselves. In simple fact, 76{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of American gals invest up to 10 hours everyday caring for associates, spouses and/or kids, and one in 5 (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women expend far more than 10 hrs a working day caring for other individuals. If ladies are the influential guideline for quite a few to access health care, we have to get the job done tougher to advertise the health and fitness of all women. Our potential to enjoy the purpose of care facilitator for other people is dependent on it.

Plenty more we can do

Outside of women’s health and fitness, we ought to discover workable solutions to other systemic inequities in the healthcare technique. We must reverse the unfavorable development that declining reimbursement premiums are possessing on preventative care and overall access to providers this sort of as physical remedy.

Technological know-how is one more unlock to superior health care obtain. These innovations span breakthroughs to how, when and wherever care is sent. The Covid-19 pandemic showed us the ability and prospective of digital care delivery to strengthen accessibility, through telehealth movie or telephonically. As we consider about geographic limits that put a premium on availability of high quality care, telehealth can engage in an outsized role in serving these populations.

In addition, telehealth can increase affected person results by means of advanced checking, cognitive affordances, clinical selection-assistance capabilities, and execution of lifestyle-saving and evidence-based vital treatment protocols, just to name a couple improvements. The to start with stage in continuing the enhancement and progression of telehealth is for the private and governing administration payers to permanently address these companies and to set reimbursement prices at parity with in-particular person payment schedules.

We can do extra to take out charge and complexity inside the healthcare process, well balanced with enhancing accessibility to treatment for those who wrestle to get the treatment they need to have. As suppliers, we need to go on to establish and eliminate boundaries to treatment each time doable.

We owe it to our clients.

Access and Coverage for Mental Health Care: Findings from the 2022 KFF Women’s Health Survey

Access and Coverage for Mental Health Care: Findings from the 2022 KFF Women’s Health Survey

Vital Takeaways

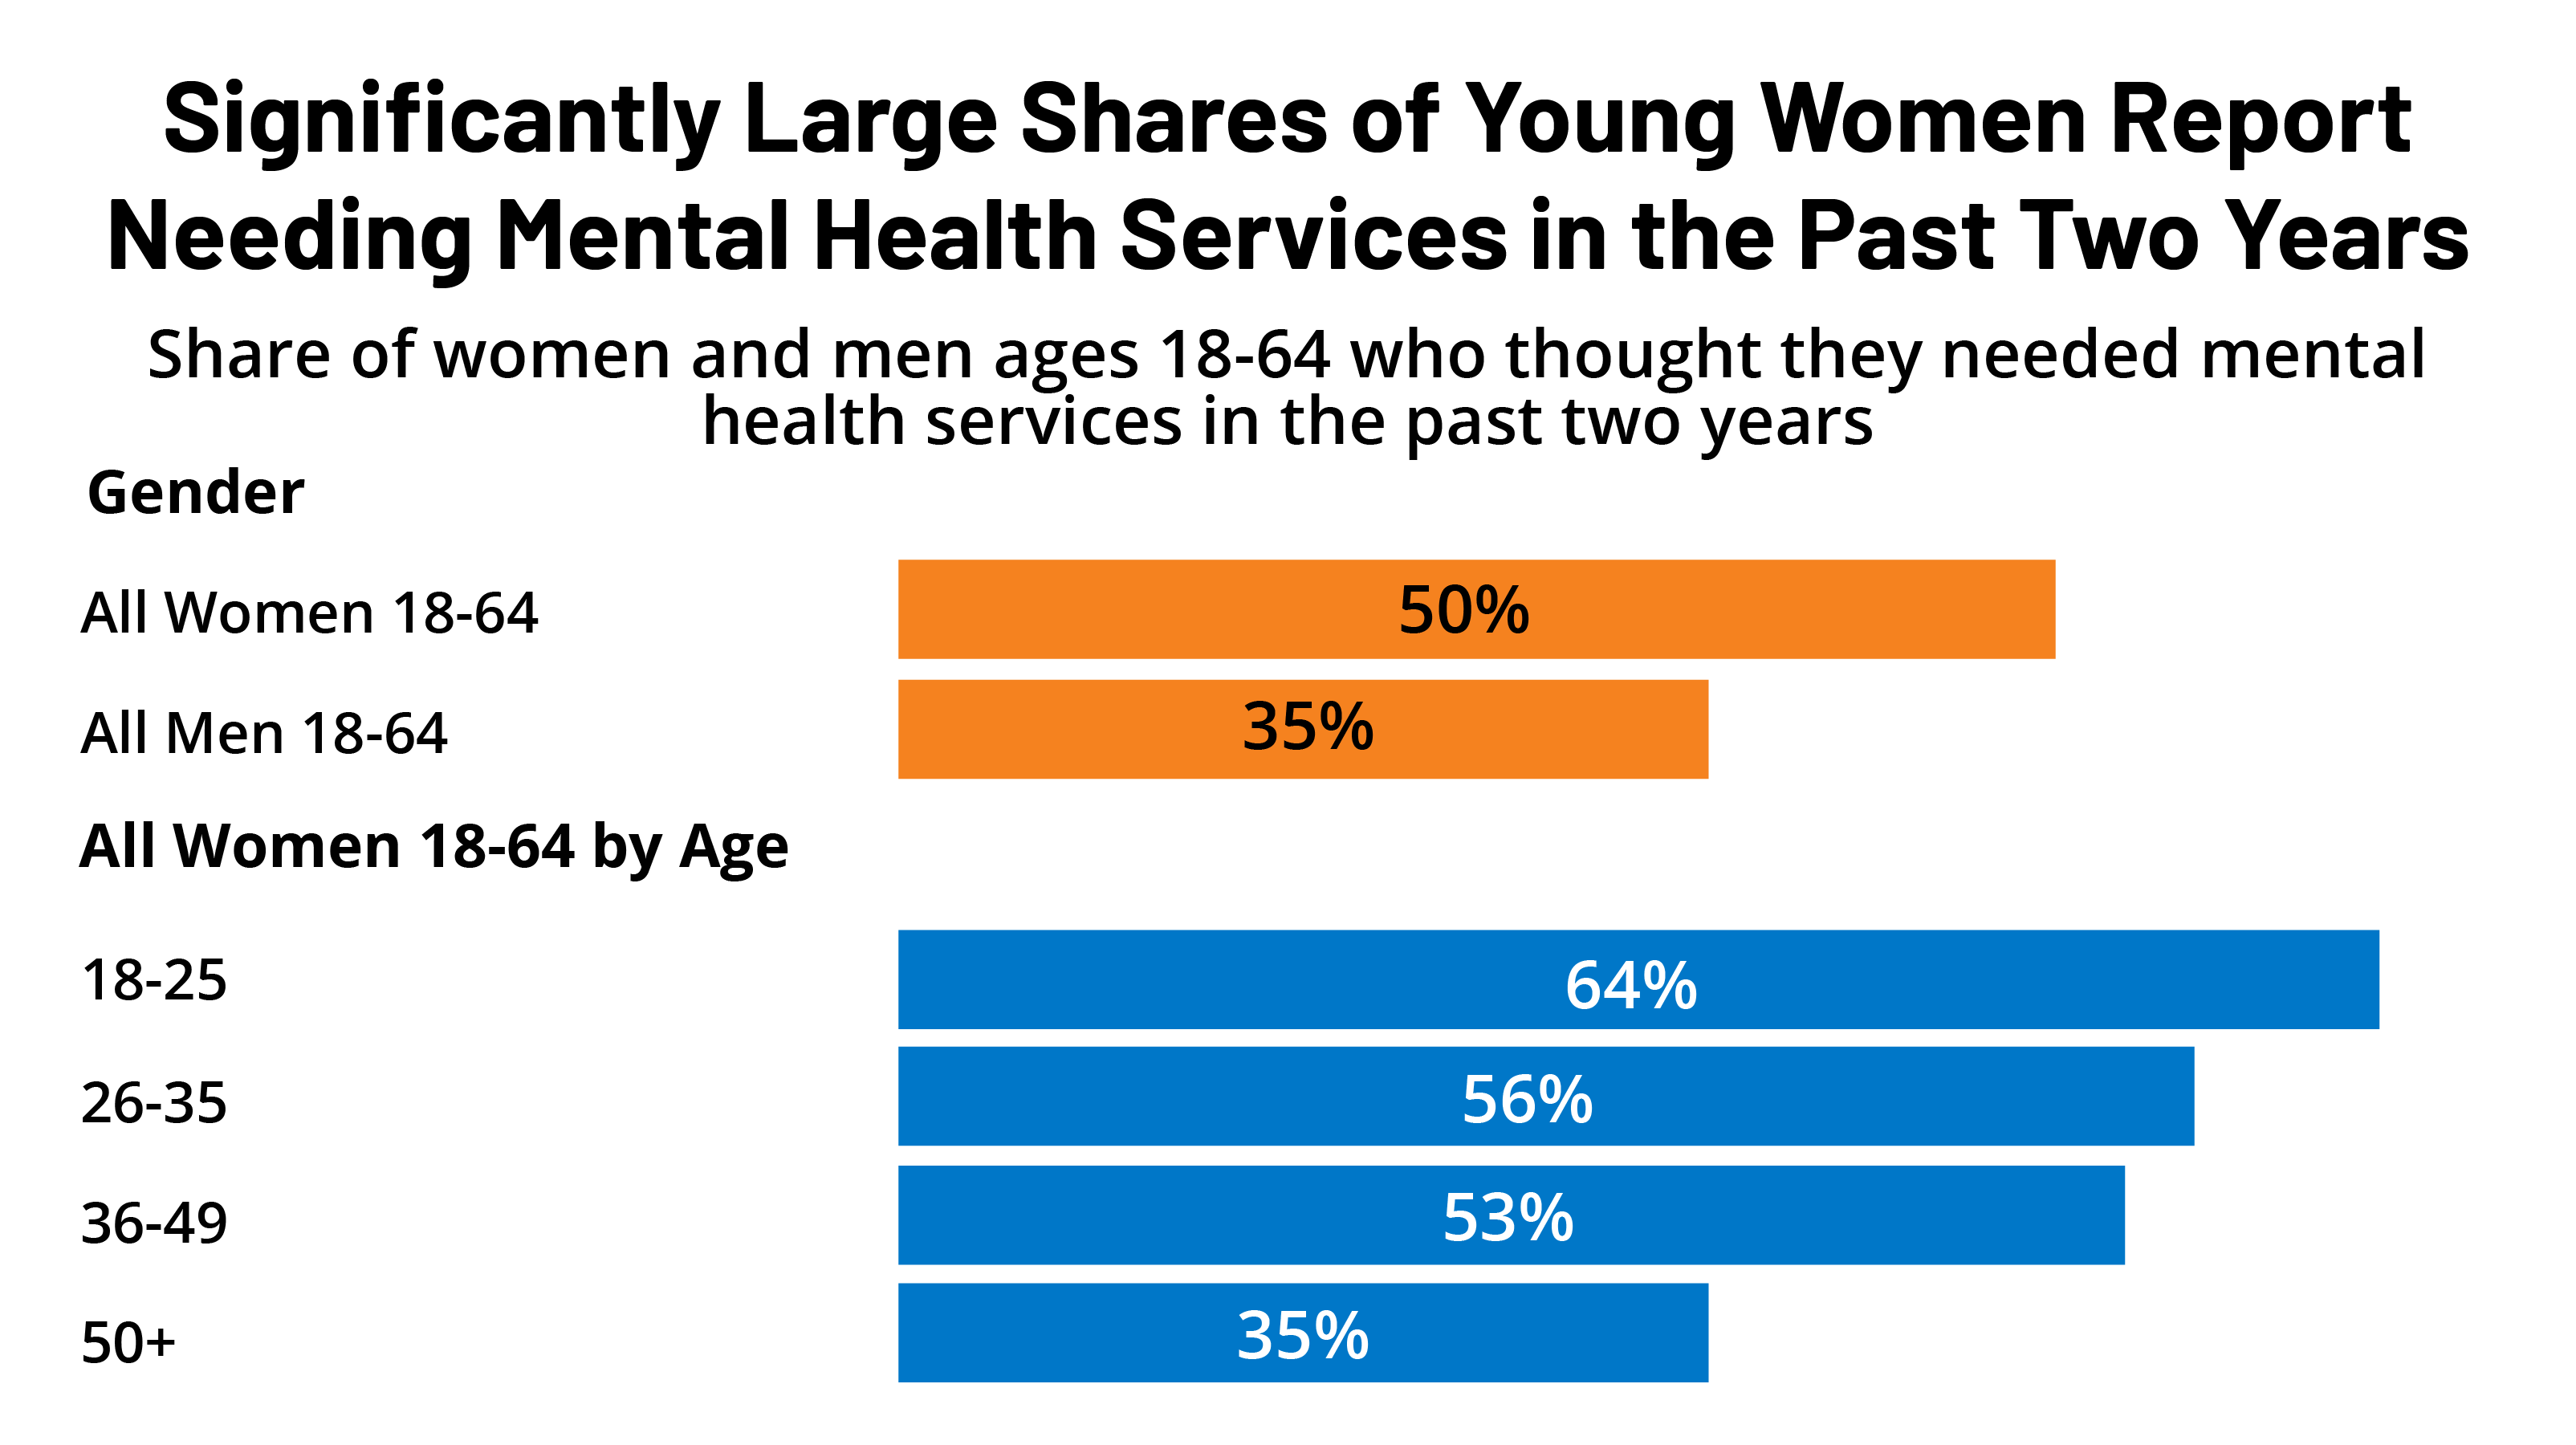
  • A noticeably bigger share of women (50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) than guys (35{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) thought they required psychological wellness providers in the past two decades. Amid those who considered they essential mental wellbeing care, about six in ten women of all ages and guys sought treatment in the previous two yrs.
  • Just about two-thirds of youthful gals ages 18-25 report needing mental wellbeing care in the earlier two decades in comparison to one-3rd of women of all ages ages 50-64.
  • Among the all ladies ages 18-64 who believed they desired mental wellness services in the past two a long time, just half attempted and had been ready to get an appointment for psychological wellbeing treatment, 10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} tried out but were being not able to get an appointment, and 40{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} did not request treatment.
  • Nearly 50 percent of girls who wanted mental overall health products and services and tried using to get care were being ready to get an appointment inside of a thirty day period, but more than just one-third of females experienced to wait around much more than a thirty day period. Among individuals who could not get an appointment, ladies cite limited supplier availability and cost as the key explanations they have been unable to obtain mental well being care.
  • Two in 10 privately insured females with a mental overall health appointment in the earlier two many years say their service provider did not acknowledge their insurance.
  • Sixty percent of gals had a telemedicine/telehealth go to in the past two a long time. Psychological well being care was the third most typical purpose girls cited for accessing telehealth/telemedicine providers, with 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} declaring it was the key intent of their most current telemedicine pay a visit to. The vast majority report that the excellent of their telehealth stop by was the exact same as an in-human being check out.

Introduction

Psychological overall health has emerged as a swiftly developing concern in recent years, with 90{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of Americans indicating there is a mental well being disaster in a modern KFF-CNN poll. Girls knowledge various psychological health circumstances a lot more usually than adult men, and some also expertise psychological well being problems that are special to girls, these as perinatal despair and premenstrual dysphoric ailments that may well come about when hormone degrees alter. Info from the National Middle for Health and fitness Stats present that across all age groups, ladies were almost 2 times as possible to have despair and stress than adult males. The COVID-19 pandemic, the opioid epidemic, and racism are amongst frequently cited stressors that have exacerbated extensive-standing psychological health challenges and prompted developing demand from customers for psychological health and fitness providers in the previous two a long time, specifically among females.

This temporary delivers new facts from the 2022 KFF Women’s Health Study (WHS), a nationally representative survey of 5,145 women and 1,225 gentlemen ages 18-64 conducted mostly on line from May well 10, 2022, to June 7, 2022. In addition to several subject areas similar to reproductive health and perfectly-becoming, the survey questioned respondents about their experiences accessing mental well being providers in the previous two many years. This concern temporary offers KFF WHS data on mental wellbeing providers obtain between self-discovered women and guys ages 18-64, and it also normally takes a closer seem at mental overall health protection among the gals. People today of all genders, which include non-binary people today, had been requested these thoughts on the other hand, there are insufficient data to report on non-cisgendered men and women. See the Methodology section for aspects.

Utilization of Mental Wellness Products and services

Gender Distinctions

Fifty percent of gals ages 18-64 (50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) assumed they needed psychological overall health services in the past two decades (Determine 1) and a considerably lesser share of males report they essential mental wellbeing care (35{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).  Research have prolonged documented gender disparities in the premiums and forms of psychological wellness ailments. Amid those who imagined they essential care, nonetheless, identical fees of females and gentlemen report trying to get care. Sixty p.c of gals tried to make an appointment for psychological well being compared to 56{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of adult men.

Will need and Care Trying to get

Approximately two thirds (64{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of gals ages 18-25 believed they needed psychological health and fitness products and services at some issue in the previous two many years in comparison to just 35{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of girls ages 50-64 (Determine 2). Previous results from the 2020 KFF WHS revealed that far more than half of females (51{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) mentioned that worry or pressure linked to the coronavirus had affected their psychological health. Other studies clearly show that younger grownups, especially gals, knowledgeable large incidence of depression and loneliness in the course of the early levels of the pandemic.

Extra than half of gals with low incomes (< 200{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of the federal poverty level (FPL)) (55{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and women with Medicaid coverage (58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) thought they needed mental health care in the past two years compared to less than half (47{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women with higher incomes (≥ 200{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} FPL) and those with private insurance (includes employer-sponsored insurance and individually purchased insurance) (47{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). The FPL in 2022 for an individual is $13,590 (Figure 2).

Among those who thought they needed mental health care, larger shares of women ages 26-35 (63{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and women ages 36-49 (64{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) sought care compared to 55{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50-64. Larger shares of women enrolled in Medicaid (67{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) sought mental health services compared to women who have private insurance (58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and women who are uninsured (50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 3).

A significantly lower share of Asian/Pacific Islander women (40{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say they needed mental health services at some point in the past two years than their White counterparts (50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Although not statistically significant, smaller shares of Asian/Pacific Islander women report seeking care compared to White women (50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). While the pandemic fueled violence against Asians and subsequently worsened anxiety and mental health for many, studies have shown that Asians reported greater cultural barriers to help-seeking such as family stigma and concerns about “losing face.” Cultural barriers may influence perceived need of care in addition to help-seeking behaviors.

Although the self-reported need for mental health care did not differ between Hispanic and White women (both 50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), smaller shares of Hispanic women (56{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) sought care compared to White women (62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Despite high rates of depression among Hispanic women, studies have shown that stigma and perceived discrimination in health care settings can contribute to underutilization of mental health services within Hispanic communities. Hispanic women also have the highest uninsured rate, which may limit their access to care.

Among the 50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women who thought they needed mental health services, half (50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) were able to get an appointment, while another 40{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} did not try to get mental health services (Figure 4). One in ten (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) who tried to get care were unable to make an appointment for mental health services. This suggests that the other half of women who report needing care may have unmet mental health needs.

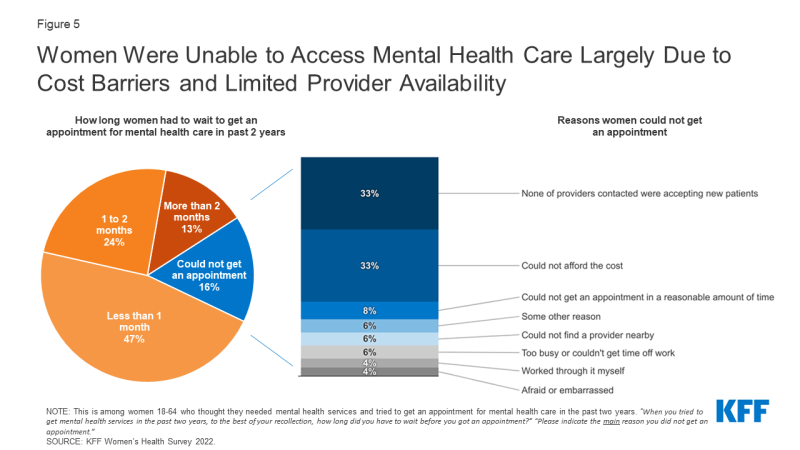
Among all women who thought they needed mental health care and tried to get it in the past two years, nearly half (47{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) had to wait less than a month for an appointment (Figure 5). One-quarter (24{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) had to wait one to two months, and 13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} had to wait more than two months to get care. The remaining 16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those who sought mental health care could not get an appointment.

Among the 16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women who needed care, sought care, and were unable to get an appointment for mental health services, the main reasons were limited provider availability and cost barriers. One-third of women who could not get an appointment say the main reasons were that they could not find a provider that was accepting new patients (33{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) or that they could not afford the cost of mental health services (33{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Eight percent could not get an appointment in a reasonable amount of time and six percent say they could not find a provider nearby. Another 6{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say they could not get an appointment for another reason, such as not wanting to go in-person due to COVID-19.

Our findings on provider availability are consistent with other studies on mental health access. A report from the U.S. Government Accountability Office found that many consumers with health insurance faced challenges finding in-network care. The country also faces a workforce shortage of behavioral health professionals in addition to other challenges with health care infrastructure that exacerbates issues with accessibility.

Figure 5: Women Were Unable to Access Mental Health Care Largely Due to Cost Barriers and Limited Provider Availability

Cost and Coverage for Mental Health Services

Among those who sought care but could not get an appointment, one-third (33{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say the main reason was that they could not afford it (Figure 5). Cost remains a barrier to mental health care access for some people with insurance and especially for those who lack coverage. Significantly larger shares of women who are uninsured (60{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say they could not get an appointment due to affordability reasons, compared to those who have health insurance either through private plans (33{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) or Medicaid (30{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 6). There were no significant differences between women who have private insurance and women covered by Medicaid.

These findings on cost barriers are consistent with current literature, which has found that along with provider availability, affordability is one of the most prevalent barriers to mental health care.

While federal laws require special insurance protections such as parity for mental health care, gaps in coverage remain. All state Medicaid programs provide coverage for mental health services, and the Affordable Care Act (ACA) requires most private insurers to cover mental health care. However, the scope of coverage varies, provider networks are limited in many plans, and mental health providers may not accept all insurance plans. Some mental health practitioners do not accept insurance of any kind.

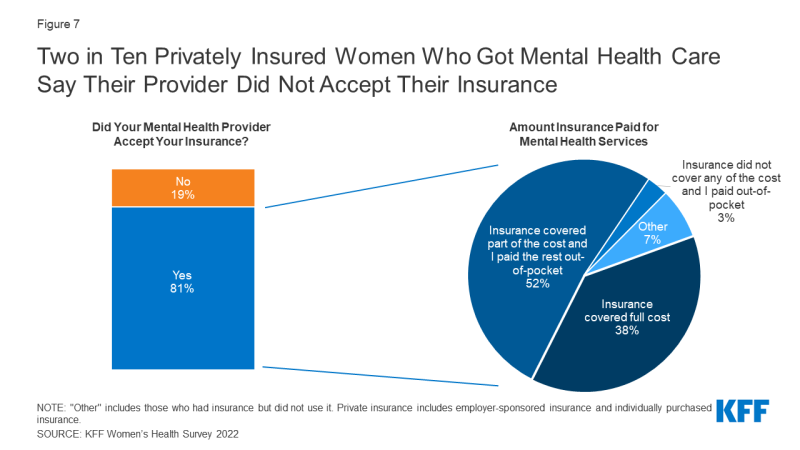
While most privately insured women who received mental health services in the past two years say their provider accepted their insurance for their most recent mental health visit (81{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), two in ten (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their provider did not. Among privately insured women who said their provider accepted their insurance, more than half report having out-of-pocket expenses for their most recent mental health visit. More than one-third (36{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their insurance covered the full cost and 52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say their insurance covered some of the cost. Three percent say their insurance did not cover any of the cost. (Figure 7).

Figure 7: Two in Ten Privately Insured Women Who Got Mental Health Care Say Their Provider Did Not Accept Their Insurance

The Affordable Care Act requires that enrollees in most private health insurance plans have the right to appeal denied claims, though some evidence suggests that many are unfamiliar with appeals processes or are unaware of this protection. Among privately insured women whose insurance was not accepted by their mental health provider, 27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} filed a claim with the health insurance plan to try to get reimbursed for some or all the cost (data not shown).

Telehealth

Social distancing during the pandemic contributed to a sharp increase in the provision of telehealth services, widening the access of counseling, therapy, prescribing, and other services via remote methods such as video and telephone. The rapid expansion of telemedicine/telehealth over the course of the COVID-19 pandemic has broadened access to health care for many, including access to mental health services. Mental health services provided via telehealth include speaking to a mental health provider over telephone or video, or through online apps such as Talkspace.

Sixty percent of women ages 18-64 had a telemedicine/telehealth visit in the past two years. Among these women, 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say the primary purpose of their most recent visit was for mental health services (Figure 8). Accessing mental health care services was the third most common reason for telehealth visits, following annual check-ups (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and visits for minor illness or injury (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Three in ten women ages 18-25 (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their most recent telehealth visit was for mental health services compared to 20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 26 to 35, 18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 36 to 49, and 10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50 to 64 and older. A larger share of White women (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) obtained mental health services at their most recent telehealth visit than Black women (13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Hispanic women (14{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and Asian/Pacific Islander women (7{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

A larger share of women with Medicaid coverage (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report that their most recent telemedicine or telehealth visit was for mental health services than women who are privately insured (15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

A similar share of women living in rural (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and urban/suburban (17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) areas report that the primary purpose of their most recent telehealth or telemedicine visit was for mental health services.

The majority (69{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women who had a telehealth or telemedicine visit in the past two years for mental health care say the quality of care they received at their most recent visit was the same as an in-person visit for this type of care (Figure 9). One-in-five (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report receiving better quality of care during their telehealth visit, while 12{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} report experiencing worse quality than an in-person visit. These findings suggest the quality of mental health care is typically not diminished when accessing care via telehealth.

Conclusion

The demand for mental health care continues to surge as wait lists for professional help grow. Recent reports reveal that mental health providers across the nation are facing an overwhelming demand for services, leaving many individuals without care. Our survey finds that among the half of women who report that they thought they needed mental health services in the past two years, only half got an appointment for care. Unmet mental health needs are known to affect the overall well-being and productivity of individuals, families, and society, and studies have consistently shown that women are disproportionately affected by these unmet needs. Data from the 2022 KFF WHS underscore that addressing issues with provider availability and cost could improve access to mental health care for some. Our findings suggest that affordability barriers are a substantial obstacle for uninsured women.

In response to the COVID-19 pandemic and other changes in the health policy environment, larger shares of employers began expanding coverage of mental health services by including more providers for in-person and telehealth care. Telehealth and telemedicine services have been recognized as an evolving strategy to increase access to care and address health needs, including care for mental health. We found that most women who received mental health services via telehealth say the quality of care they received was the same as in-person care. Telehealth has and likely will continue to play a role in addressing mental health access concerns for women.

Despite federal and state laws intended to expand and strengthen coverage for mental health care, gaps in coverage and problems with affordability continue to hinder access to mental health services even for those with private insurance and Medicaid. Our survey finds that in addition to challenges obtaining services, many women who have insurance faced at least some out-of-pocket costs for their visit. The findings from the 2022 KFF WHS suggest that future policies affecting telehealth, provider availability, health insurance coverage, and affordability will play a significant role in addressing the demand for mental health care.

Experiences with Health Care Access, Cost, and Coverage: Findings from the 2022 KFF Women’s Health Survey

Experiences with Health Care Access, Cost, and Coverage: Findings from the 2022 KFF Women’s Health Survey

Introduction

Women’s access to health care is shaped by a broad range of factors, including coverage and income, the availability of health care providers in their communities, and the affordability of care and health insurance.

The Affordable Care Act (ACA) has expanded pathways to affordable coverage to millions of women by broadening eligibility for Medicaid and providing subsidies to make individual health insurance coverage more affordable for those who do not have access to coverage through their employer. The ACA also contains provisions aimed at alleviating some of the financial barriers to health care; however, many women still face challenges with health care costs and medical bills, particularly those who are uninsured or have low incomes.

This report presents findings from the 2022 KFF Women’s Health Survey (WHS) on women’s health status, use of health care services, and costs. The WHS is a nationally representative survey of 5,145 self-identified women ages 18 to 64, conducted May 10 – June 7, 2022. See the Methodology for more details.

Summary of Findings

  • The majority of women ages 18-64 report being in excellent, very good, or good health (82{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}); however, nearly one in five (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women describe their health as fair or poor, with substantial differences by sociodemographic characteristics.
  • Half of women (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report having an ongoing health condition that requires regular monitoring, medical care, or medication and 18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} report having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities, with higher rates among older women. Ten percent of women with a disability or ongoing health condition do not have a regular doctor or health care provider.
  • Nearly all women ages 18-64 (95{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have seen a doctor or health care provider in the past two years, but a smaller share has had a general check-up or well-woman visit (73{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Uninsured women are significantly less likely than insured women to have seen a provider or had a check-up in the past two years.
  • Overall, women have more interactions with and connections to the health care system than men. Higher shares of women report having a usual source of care and have visited a health care provider in the past two years than men.
  • Most women (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) obtain their health care at doctors’ offices, but health centers and clinics are common sites of care for underserved populations. One in four (25{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) uninsured women, one in five (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) Hispanic women, and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those with Medicaid usually visit health centers or clinics for their routine health care.
  • Most women ages 18-64 (60{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say they have had a telemedicine visit in the past two years. Most (69{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate the quality of care they received via telemedicine as comparable to in-person care. Annual check-ups, minor illnesses and injuries, and mental health services were the top reasons women accessed services via telemedicine.
  • Many women with health insurance report experiencing limitations with their insurance in the past 12 months. One in five (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women with Medicaid say that their plan did not cover care they thought was covered, or paid less than expected, compared to one-third (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women with employer-sponsored coverage.
  • More than one in four (27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women ages 18-64 report having had problems paying medical bills in the past 12 months compared to 23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men.
  • Among women experiencing problems with medical bills in the past year, more than half (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have had difficulty paying for basic necessities like food, heat, or housing because of the bills, including nearly seven in ten (68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women with low incomes.

Health Status and Use of Prescription Medications

Health Status

The majority of women ages 18-64 report being in good or excellent health, but substantial shares of women with low incomes and those with Medicaid describe their health as fair or poor.

Most women ages 18-64 (82{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as excellent, very good, or good; however, 18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women describe their health as fair or poor, similar to other national estimates.

A higher share of women ages 36-49 (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and ages 50-64 (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as fair or poor than those ages 18-35 (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 1). A larger share of Black (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Hispanic (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women report being in fair or poor health than White (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women. (Persons of Hispanic origin may be of any race; other groups are non-Hispanic.) Approximately three in ten women with low incomes (28{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and women with Medicaid coverage (30{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as fair or poor. (This survey defines low income as household income under 200{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of the federal poverty level (FPL); higher income is 200{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} or more of the FPL. The federal poverty level (FPL) for an individual in 2022 is $13,590.) A higher share of women with Medicaid describes their health as fair or poor than women with employer-sponsored insurance (11{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), individual insurance (13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and the uninsured (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

Many women are managing ongoing health conditions or living with disabilities that impact daily life.

Half (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women ages 18-64 report that they have an ongoing health condition that requires regular monitoring, medical care, or medication (Figure 2). This rate increases with age, from 41{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 18-49 to 65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50-64. Smaller shares of Hispanic (41{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (38{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women report having an ongoing health condition than White (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Black (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women. More women with employer-sponsored insurance (46{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report having an ongoing health condition requiring regular care than do uninsured women (36{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women with Medicaid (53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are more likely than those with employer-sponsored insurance or the uninsured to report having an ongoing condition.

Eighteen percent of women ages 18-64 report having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities (Figure 3). Women ages 50-64 are more likely than those ages 18-49 to report having a disability or chronic disease (24{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Lower shares of Hispanic (14{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (6{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women have a limiting disability or chronic condition than do White (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Black (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women. Women with Medicaid coverage (30{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those with low incomes (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are more likely than their counterparts to report having a disability or chronic disease.

Use of Prescription Medications

Almost two-thirds of women ages 18-64 take at least one prescription medication, including birth control pills, on a regular basis.

Women may take prescription medications to treat or manage chronic conditions and acute illnesses or to prevent pregnancy. Sixty-three percent of women report taking at least one prescription medicine, including birth control pills, on a regular basis (Figure 4).

Prescription medication use increases with age, with 58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 18-49 taking at least one on a regular basis compared to 73{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50-64. White women (68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are more likely than Asian/Pacific Islander (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Hispanic (55{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and Black (58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women to take a prescription medication on a regular basis. As may be expected, a higher share of women in fair or poor health report taking a prescription medication regularly than women in excellent or very good health (76{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 54{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Even though more uninsured women (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rate their health as fair or poor than insured women (17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), a higher share of insured women (65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (data not shown) report taking take a prescription medication than uninsured women (43{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). One explanation for this could be that uninsured women have less access to health care and affordable medications than those with insurance, which could result in lower use of prescription medications.

Differences Between Women and Men

In measures of health status and prescription drug use, there are some differences and some similarities between women and men.

More women than men report having an ongoing health condition that requires regular monitoring, medical care, or medication (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 43{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), or taking at least one prescription medication on a regular basis (63{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 48{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 5). The share of women and men who rate their health status as fair or poor is similar (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} and 20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}, respectively), as is the share who report having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}, respectively). (People of all genders, including non-binary people, were asked these questions; however, there are insufficient data to report on non-cisgendered people.)

Accessing Health Care

Sources of Care

While the vast majority of women have a regular provider they turn to for routine care, only half of uninsured women have a usual source of care.

Having a usual source of health care is associated with increased use of preventive care and better health outcomes. Eighty-two percent of women have a regular doctor or health care provider they see when they are sick or need routine care. The share of women who have a regular provider increases with age (Figure 6). Hispanic women (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are slightly less likely than White (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Black (84{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women to have a usual source of care. Fewer women who are uninsured (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those with low incomes (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report having a usual source of care than their counterparts. Women who live in a state that expanded Medicaid are more likely to have a usual source of care than women in states that have not expanded Medicaid (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (data not shown). Ten percent of women with a disability or an ongoing health condition do not have a regular doctor or health care provider (data not shown).

Sites of Care

Most women obtain their health care at doctors’ offices, but health centers and clinics are common sites of care for underserved communities, particularly for uninsured women, those with Medicaid, and Hispanic women.

Eighty-two percent of women have a regular doctor or place they usually go for health care. Among them, eight in ten (79{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) report that they usually obtain their care at a doctor’s office (Figure 7). Ten percent obtain care at an urgent care or retail clinic; 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} usually go to a health center or school-based clinic; and 3{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} cite the emergency room or some other place as their usual site of care.

More women ages 50-64 (88{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), White (84{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Asian/Pacific Islander (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women, women with higher incomes (85{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and those with private health insurance (86{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) rely on an office-based physician for their regular care than their counterparts (Table 1). (Private health insurance includes employer-sponsored insurance and individually purchased insurance.) Health centers and clinics play a larger role as sites of care for women ages 18-49 (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Hispanic women (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), women with low incomes (15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), those with Medicaid (17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and uninsured women (25{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) than their counterparts.

Check-ups

Regular provider visits give people an opportunity to talk with clinicians about a broad range of issues, including preventing illness, the role of lifestyle factors on health, and management of chronic illnesses. Under the Affordable Care Act, most health plans must cover at least one annual check-up/well-woman visit, which can include assessments of diet and physical activity, preconception care, and cancer screenings.

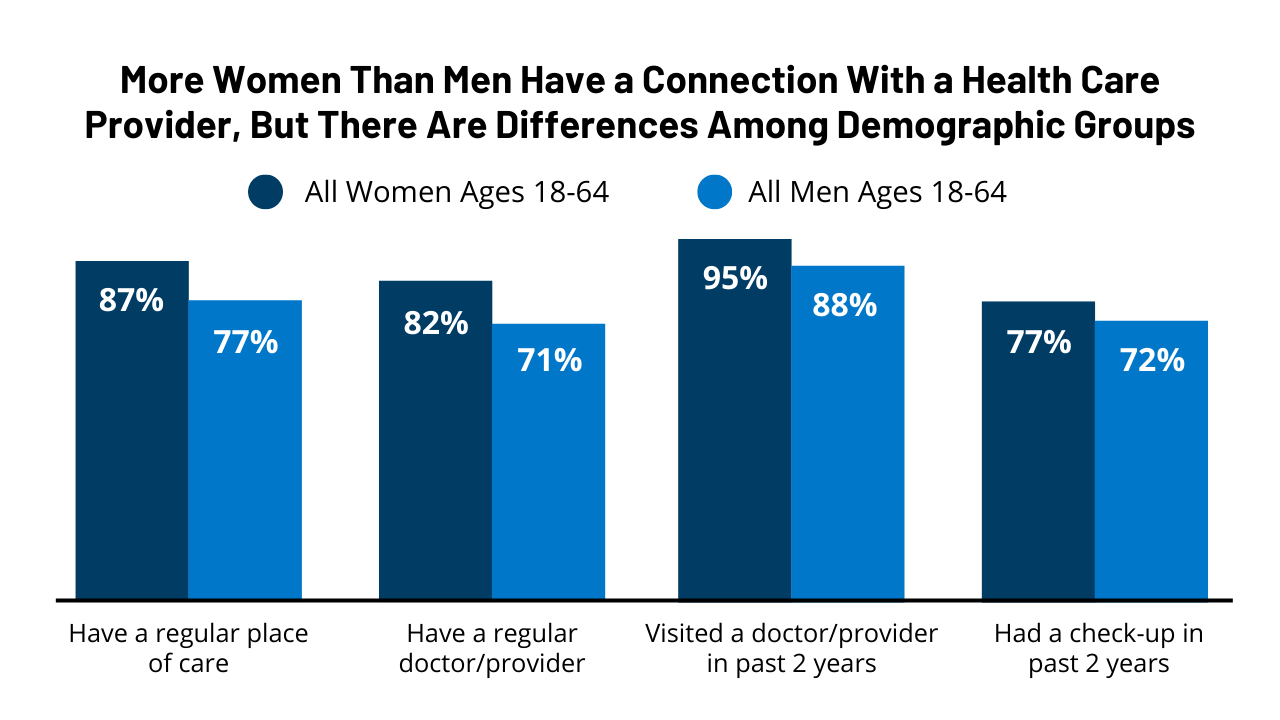
Overall, women have more interactions with and connections to the health care system than men. Higher shares of women than men report having a usual source of care and have visited a health care provider in the past two years.

Women are more likely than men to report having a regular place of care (87{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and a regular doctor or health care provider (82{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 71{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) (Figure 8). Ninety-five percent of women say they have visited a health care provider in the past two years and among them, 77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} have had a check-up, compared to 88{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} and 72{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men, respectively. (People of all genders, including non-binary people, were asked these questions; however, there are insufficient data to report on non-cisgendered people.)

While most women ages 18-64 have visited a doctor in the past two years and had a check-up, rates are lower among younger women and uninsured women.

Nearly all women (95{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have seen a doctor or health care provider in the past two years (Figure 8). However, fewer women ages 18-35 (92{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Hispanic (92{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and uninsured women (78{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have visited a doctor in the past two years than their counterparts.

Among women who have seen a health care provider in the past two years, more than three-quarters (77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) have had a general check-up/well-woman visit during that period. However, a smaller share of uninsured women (61{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and women with low incomes (74{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) had a recent check-up than their counterparts. A smaller share of women ages 18-35 had a check-up than women ages 50-64 (72{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 85{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and more Black women than White women had one (83{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 77{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

Telemedicine

Two years into the pandemic, most women ages 18-64 (60{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say they have had a telehealth visit (Figure 9).

Smaller shares of younger women report having had a telehealth visit in the past two years and fewer than half of uninsured women say they have had one. Women living in rural areas are less likely than those living in urban areas to have had a telehealth visit with a health care provider (49{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) in the past two years, a general trend that has been documented in other studies. This could be due, in part, to patient preferences as well as more limited access to reliable high-speed internet and technology among those living in rural areas than in urban/suburban areas, as has been documented by other research. Slightly fewer women living in Medicaid non-expansion states have had a telehealth visit than those in expansion states (58{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). There were no statistically significant differences by race/ethnicity (data not shown).

Among women ages 18-64 who had a telehealth visit in the past two years, nearly two in ten (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say the primary purpose for their visit was for an annual check-up or well-visit, minor illness or injury, or mental health services (Table 2). The next most common reasons included management of a chronic condition (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), another health concern not listed (13{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), COVID-related symptoms (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), and gynecological or sexual health issues (5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

Primary reasons for telehealth visits often vary by age. Among women ages 18-25 who had a telehealth visit in the past two years, three in ten (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say the primary purpose for their most recent telehealth visit was mental health services, compared to just 10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 50-64. Almost one-quarter (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women ages 50-64 say their most recent telehealth visit was for management of a chronic condition, compared to 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women ages 18-25. Among women ages 18-49 who had a telehealth visit in the past two years, 2{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say prenatal or postpartum care was the primary purpose for the most recent telehealth, including 2{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those ages 18-25, 4{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those ages 26-35, and 5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those ages 36-49 (data not shown).

Most women (70{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say the quality of care they received at their most recent telehealth visit was similar to the quality of in-person care, with 12{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} saying their telehealth care was better and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} saying it was worse than in-person care (Figure 10). Larger shares of women with low incomes (18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those who are uninsured (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their telehealth care was better than in-person care than women with higher incomes (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and those with private insurance (10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Two percent of women who had a telehealth visit in the past two years say they have not had an in-person visit for this type of care.

When looking at specific types of services provided via telehealth, one in five (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) women receiving telehealth services for a gynecological or sexual health issue or mental health services say the care they received via telehealth was better than in-person care (Figure 11). Conversely, about one in five women say their telehealth care for treatment of minor illnesses and injuries (22{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and COVID-related symptoms (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) was worse than in-person care. Among women ages 18-49 who had a telehealth visit in the past two years and whose most recent visit was for prenatal or postpartum care, 18{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} said the quality of care was better than the quality of in-person care, 65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} said it was the same, and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} said it was worse (data not shown).

Health Coverage and Costs

Insurance

More insured women than men report having experienced problems with their insurance covering needed health services or medications in the past 12 months.

Thirty-one percent of women ages 18-64 with health coverage (employer-sponsored insurance, individual insurance, or Medicaid) report that in the past 12 months, they or a family member received care from a doctor, hospital, or lab they thought was covered, but their health plan did not cover the bill at all, or paid less than they expected, compared to 26{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men who say the same (Figure 12). More insured women than men say their plan would not cover a prescription medication or required a very expensive copay or coinsurance for it (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women were slightly more likely than men to say that in the past 12 months, their plan would not cover a test or scan that their doctor recommended (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

These gender differences could be due to several factors, including that women are more likely than men to have visited a health care provider in the past two years, to take prescription medication on a regular basis, and to have an ongoing health condition that requires regular monitoring, medical care, or medication (see “Health Status and Use of Prescription Medications” section above).

Some of these insurance coverage problems vary by type of insurance plan (Table 3).

For example, among women, more women with private insurance (individual or employer-sponsored plans) (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) than women with Medicaid (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their plan did not cover medical care they thought was covered, or paid less than expected, in the past 12 months. A higher share of women with individual coverage (35{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) than women with employer-sponsored coverage (27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) or Medicaid (29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say that their plan did not cover a prescription medication or required high cost sharing for it. Women with individual coverage (28{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are also more likely than women with employer-sponsored coverage (20{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) or Medicaid (21{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) to report their plan did not cover a test or scan their doctor recommended in the past 12 months.

Insurance companies sometimes deny coverage of prescription medications or require large co-payments, but many women are not aware that they can appeal coverage decisions.

The ACA requires that most private health insurance plans have an appeals process for coverage determinations and claims. State Medicaid programs are also required by federal law to have an appeals process. Among the 65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of insured women who take a prescription medication on a regular basis, only four in ten (40{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) are aware that they can ask their insurance company to reconsider covering the cost of a prescription, known as filing an appeal (Figure 13).

Knowledge of this option varies by income level and insurance type. More low-income women with insurance who take a prescription medication are aware that they can file an appeal with their health plan than higher-income women (44{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 38{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women with Medicaid are also more likely than those with employer-sponsored insurance to know that this is an option (45{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 38{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

Many women who take a prescription medication say their out-of-pocket costs for those medications have increased over the past year.

Among the nearly two-thirds (63{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women ages 18-64 who take a prescription medication on a regular basis, almost one-third (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their out-of-pocket costs for those medications have increased compared to 12 months ago (Figure 14). Over half (54{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say their out-of-pocket costs have stayed the same, 6{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say their costs have decreased, and 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} say they do not know.

Changes in out-of-pocket costs vary by type of insurance coverage. Fifty-five percent of women who are uninsured and who take a prescription medication say that their costs have increased compared to 12 months ago, compared to 34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women with private insurance and 17{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of those with Medicaid. Most women with private insurance (53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Medicaid (63{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say that their out-of-pockets costs for their prescription medications has not changed in the past year. Notably, twice as many women with Medicaid (16{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) who take a prescription medication say they do not know how their out-of-pocket costs for those medications has changed, compared to 8{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of all women. (Four percent say they were not taking any of these medications 12 months ago; they are not included in this analysis.)

Medical Bills

While the ACA has addressed some financial barriers to accessing health care, many women, including those with insurance, still report problems paying medical bills. Some women incur significant medical expenses because of an unexpected diagnosis such as cancer, or an illness or injury that limits their ability to work and earn income to pay off bills. Costly medical bills can also arise after receiving care from an out-of-network provider, commonly referred to as surprise medical bills. (The No Surprises Act, which took effect in January 2022, establishes new federal protections against surprise medical bills.)

More than one in four women ages 18-64 report having had problems paying medical bills in the past year, with higher rates among uninsured women and women in poorer health. (Poorer health refers to those who report being in fair or poor health.)

Twenty-seven percent of women report that they or a household family member has had problems paying medical bills in the past 12 months, a slight increase from 2020 (24{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Problems paying medical bills are more common among women than men (23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

Outstanding medical bills are more common among uninsured and women with low incomes and those in poorer health (Figure 15). This includes more than two in five (42{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) uninsured women and women in poorer health, and almost two in five women with low incomes (37{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Approximately one-third of women who live in states that did not expand Medicaid (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}), Black (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) and Hispanic women (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) also report having trouble paying medical bills in the past 12 months. Women who live Medicaid expansion states are less likely than those in non-expansion states to have had trouble paying medical bills (data not shown). More women with children report problems paying medical bills in the past 12 months than do women without children (32{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 25{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

Among women who report having had problems paying medical bills in the past 12 months, one-third (34{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) say it was because they or someone in their family lost a job, income, or unemployment benefits. Seventeen percent say it was because they or someone in their family had health expenses related to COVID-19. The majority (66{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) of women who say they have had trouble paying medical bills in the past 12 months report that it is due to some other reason (Figure 16).

Medical bills can have serious consequences for people’s financial well-being and ability to afford basic necessities. Although more women than men report having problems paying medical bills in the past 12 months, women and men experience financial consequences because of the bills at similar rates.

Among the 27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 23{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men who have had problems paying medical bills in the past 12 months, similar shares have had to set up a payment plan to pay off the bill (65{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men); used up all or most of their savings (62{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 69{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men); been contacted by a collection agency (61{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 56{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men); and had difficulty paying for basic necessities (52{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women and 53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of men) (Table 4). However, a higher share of men than women with recent problems paying medical bills report borrowing money from family or friends (53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 42{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

For women, the financial consequences of medical bills vary by income level (Figure 17).

Among the 27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of women who report having trouble paying medical bills in the past 12 months, women with low incomes are more likely than women with higher incomes to report having difficulty paying for basic necessities such as food, heat, or housing (68{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 39{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}); having been contacted by a collection agency (70{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 53{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}); or borrowing money from family or friends (56{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 29{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Women with higher incomes are more likely than women with low incomes to have had to set up a payment plan with a doctor or hospital (71{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 59{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).

Conclusion

Women’s access to and use of health care services has an impact on their health outcomes. Most women report having a regular source of care and having had a recent doctor’s visit. However, connections to the delivery system are more tenuous for uninsured women and women with low incomes, who are less likely to report a recent visit or regular place of care. Most women report they have had a general check-up/well-woman visit in the past two years, but like other measures on access to care, rates are lower among uninsured women and those with low incomes. When looking at gender differences, women are more likely to have regular connections with the health care system than men.

The COVID-19 pandemic has changed how some people access health care, particularly a shift from in-person care to increased use of telehealth. Federal and state policy changes and market forces also contributed to the growth in the use of telehealth. Most women say they have used telehealth in the past two years, and most of them rate the quality of care they received as comparable to an in-person visit. This pattern is consistent for all types of telehealth services our survey asked about, ranging from check-ups to mental health care services. While many women do not express concerns about quality differences between telehealth and in person care, the extent to which this newer modality will continue to be utilized and grow will also depend on the reimbursement policies that private plans and public payors adopt following the end of the pandemic emergency.

Despite the role that health insurance plays in helping people afford health care and reducing patients’ financial risks when they need routine care, get sick, or need to be hospitalized, scope of coverage and affordability can still be challenging for many women with insurance coverage. A sizeable minority of women with insurance report having problems using their health plan, such as their plan not paying for health care they thought was covered but was not, or their plan not covering their prescription drugs or requiring high cost sharing for them. Many people say they have had problems paying medical bills in the past year, bur rates are higher among women than men. While the ACA strengthened access to coverage and offers protection from some out-of-pocket health care costs, gaps remain. For many, health care and coverage are still unaffordable and represent potential barriers to needed care.

Defendents’ access to medical treatment in jail not a factor in bail decisions, NH Supreme Court rules

Defendents’ access to medical treatment in jail not a factor in bail decisions, NH Supreme Court rules

Judges in New Hampshire are not permitted to take into consideration whether denying bail to a defendant with health-related circumstances jeopardizes their protection though incarcerated, according to an unanimous viewpoint unveiled Friday by the New Hampshire Supreme Court docket.

The justices rejected an appeal from a defendant held inside Valley Road Jail in Manchester who claimed he was not acquiring correct health care procedure for “a collection of advanced health care concerns,” and that beneath the existing bail statute, his protection should really be a aspect in his release on bail.

The defendant, Daniel Laguerre, is currently detained on domestic violence similar prices. He was originally granted bail in August, but allegedly assaulted the very same human being shortly after his launch. Exceptional Court docket Decide William Delker denied Laguerre’s bail request, ruling that underneath recent law, judges are not licensed to look at regardless of whether the ailments inside a jail endanger that person’s health and fitness and welfare.

Attorneys for Laguerre argued that present point out law does allow judges to consider a defendant’s protection, no matter whether released into the community or whilst currently being held in custody, but the New Hampshire Supreme Courtroom disagreed, noting that the Legislature has in no way additional that language into the legislation.

“Although New Hampshire’s bail statute has been revised several occasions, it has consistently demanded courts to look at whether or not a defendant’s launch would endanger the protection of the defendant or the community without having mentioning the defendant’s safety while confined,” wrote Affiliate Justice Patrick Donovan in a seven web page view.

The court pointed out that defendants do have other lawful alternatives, which include the submitting of habeas corpus petitions, if they think their rights are currently being violated.

Cassie Moran, an attorney for Rath, Young and Pignatelli who argued the scenario on behalf of Laguerre, explained that bail hearings were the fastest way to guarantee another person with an rapid health and fitness worry was in a position to protected their launch.

“We have to make guaranteed that everyone’s legal rights are becoming upheld and getting honored, primarily the most susceptible between us,” she claimed.

At the moment, judges weigh if a defendant poses a possibility of flight, or is a hazard to the group or them selves, in analyzing bail conditions. The court famous that if the Legislature wished judges to also take into consideration a defendant’s health care affliction when incarcerated and obtain to appropriate well being care as a issue for launch, elected officers could improve the regulation.

Fighting Cancer, Expanding Access To Care And Protecting Women’s Health

Fighting Cancer, Expanding Access To Care And Protecting Women’s Health

These scientists and entrepreneurs are taking on some of healthcare’s biggest challenges, from cancer to women’s health to ensuring equitable access to care.

By Alex Knapp, Katie Jennings, Arianna Johnson, Sarah Emerson and Ariyana Griffin


When Dina Radenkovic, 27, was working as a doctor and researching diseases related to aging, she discovered that women’s ovaries age about five times faster than the rest of a person’s body. This is partially why women struggle with fertility issues as they get older, and also why she founded her company, Gameto, which uses cell engineering with an aim of making IVF cycles shorter and reducing the need for hormone injections.

“We’re in a golden age where technologies are really able to manipulate biology,” she says, adding that even diseases that were not thought to be curable less than a decade ago now have true cures going through clinical trials, thanks to advances in cell engineering and gene therapy.

Radenkovic isn’t unique in applying new technologies to old problems in healthcare. She’s just one of the rising stars on this year’s 30 Under 30 Healthcare list, which includes entrepreneurs and scientists all working to expand access to care and to treat and cure disease.

For more than a decade, Forbes has highlighted young entrepreneurs, researchers and physicians for our annual 30 Under 30 Healthcare list, with the help of nominations from the public. To be considered for this year’s list, all candidates had to be under the age of 30 as of December 31, 2022, and never before named to a 30 Under 30 list. Candidates were evaluated by a panel of judges featuring Victor Lopez-Carmen, cofounder of the Ohiyesa Premedical Program at Brigham and Women’s Hospital and alumnus of the 2022 Forbes Under 30 Healthcare list; Michelle Davey, cofounder and CEO of Wheel; Hemant Taneja, managing partner of General Catalyst; and Helen Sabzevari, president and CEO of Precigen.

In addition to Raenkovic, several other listmakers are also focused on women’s health. Take Briana Chen, 28, for example, a research scientist who’s studying how the symptoms of mental illnesses like depression diverge between men and women. Then there’s Alison Burklund, 28, whose company Nanopath is developing rapid diagnostics for gynecological exams. Meanwhile, Amira Barkal, 29, is working to develop new treatments for ovarian and breast cancer with her company Pheast Therapeutics.

Several other listmakers this year also have their sights set on cancer. Micronoma, the company cofounded by Gregory Sepich-Poore, 29, is developing microbiome-based screening tests that could detect cancer earlier than conventional screening methods. Meanwhile, Kevin Parker, 28, and his company Cartography Biosciences aim to improve the ability of immunotherapies to target tumors. Shu Jiang, 29, an assistant professor at the Washington University School of Medicine, is developing better statistical methods for precision oncology and risk prevention for breast cancer. That research also focuses on techniques that are developed with inclusivity in mind, so that they work better for all people, not just particular subsets.


That focus on improving more equitable access to care is also top of mind for Ed Gaussen, 28, whose company Mantra Health offers a mental healthcare platform for college students. Then there’s Jared Dauman, 27, whose company Soda Health works with insurance companies to help people manage their health in surprising ways, such as providing transportation options for people who struggle to be able to make it to the doctor.

These are only a few of the incredible finalists on this year’s Forbes 30 Under 30 Healthcare list. Be sure to read up on all of them, plus all of the other 30 Under 30 2023 categories.

This year’s list was edited by Katie Jennings, Alex Knapp, Arianna Johnson, Sarah Emerson and Ariyana Griffin. For a link to our complete Healthcare list, click here, and for full 30 Under 30 coverage, click here.

Gallery: Callouts 30 Under 30 2023

20 images

30 UNDER 30 RELATED ARTICLES

MORE FROM FORBESHailey Bieber Is Out To Prove Her Entrepreneurial Chops Are More Than Skin-DeepMORE FROM FORBESMegan Thee Millions: Rapper Reaps Record RichesMORE FROM FORBESBy The Numbers: Meet The Forbes Under 30 Class Of 2023MORE FROM FORBESMeet The Next Class Of Forbes 30 Under 30 Listers Transforming The Food IndustryMORE FROM FORBESMeet The Under 30s Powering The Future Of Energy And SustainabilityMORE FROM FORBES30 Under 30 Marketing & Advertising 2023: Meet The Creators, Founders And Marketers Pushing Brands Forward

UnitedHealthcare and Peloton to Provide Millions of More People With Access to a Leading Interactive Fitness Platform

UnitedHealthcare and Peloton to Provide Millions of More People With Access to a Leading Interactive Fitness Platform

UnitedHealthcare, element of UnitedHealth Team (NYSE: UNH), and Peloton Interactive, Inc. (Nasdaq: PTON) have renewed and expanded their romance to assistance a lot more individuals get or remain active and enhance their total nicely-remaining.

Less than the newly expanded settlement, as several as 10 million UnitedHealthcare professional members may possibly turn out to be suitable for a yearlong subscription to the Peloton Application Membership – or receive a three-month waiver towards a Peloton All-Accessibility Membership – at no more expense as component of their well being gains*. In addition, suitable UnitedHealthcare members in most states will receive chosen pricing on choose Peloton connected conditioning solutions, like the Peloton Bike, Bike+ and Tread.

The Peloton give is now included in most UnitedHealthcare totally insured employer-sponsored options and is now readily available as an choice for corporations with a self-funded plan and less than 3,000 employees and dependents. Bigger companies with a self-funded strategy might also select to make the Peloton give out there to their staff members by means of a immediate arrangement with Peloton Company Wellness, including most popular pricing on pick out Peloton related fitness products.

“Our original provide with Peloton is proving powerful in serving to motivate lots of of our users to get or keep active, with the objective of supporting their psychological, bodily and emotional wellbeing,” explained Dr. Rhonda Randall, chief healthcare officer for UnitedHealthcare’s business company. “This expanded collaboration will assist even far more individuals optimize the benefit of their wellbeing positive aspects although pursuing their health goals.”

Considering that initially launching the supply in 2021, UnitedHealthcare members are collectively finishing about 1 million Peloton courses for each thirty day period between enrollees who have taken at least a person class throughout a presented thirty day period, users are taking an average of about 3 classes every week.

“Aligned with UnitedHealthcare’s mission, and by way of the electric power of local community and earth-class written content, Peloton is fully commited to delivering the inspiration for persons to reside healthier life,” claimed Cassidy Rouse, senior vice president of expansion partnerships and company wellness, Peloton. “We are inspired by the progress and impact of the collaboration in its first calendar year, and we’re pleased to continue on to do the job with UnitedHealthcare in producing wellness far more obtainable for tens of millions of Us residents.”

Eligible UnitedHealthcare members may perhaps acquire aspects via email about activating their Peloton App or All-Obtain Membership – or they can log into myuhc.com to examine eligibility. When eligible users declare their personalised code by their myuhc.com account, they can activate their 12-month membership to a Peloton App Membership – or a three-thirty day period subscription to a Peloton All-Obtain Membership – at no more price tag. At the finish of the 12-thirty day period membership, UnitedHealthcare strategy contributors will have the prospect to renew the Peloton Application Membership at the market place fee instantly by way of Peloton UnitedHealthcare members’ Peloton App Membership will not routinely renew beyond the 12-thirty day period provide.

Out there by means of the Peloton App, with no gear demanded, or via a Peloton Bicycle, Bike+ or Tread as an All-Access Member, qualified UnitedHealthcare members can use the supply to consider thousands of reside and on-demand from customers fitness classes across various disciplines this sort of as strength, boxing, barre, out of doors running, biking, strolling, meditation and extra. The Peloton App is readily available on any iOS or Android machine, Apple Tv set, Fire Television set, Roku TVs and Chromecast and Android Television set.

Far more data about the collaboration is offered at uhc.com/peloton.

About UnitedHealthcare

UnitedHealthcare is committed to supporting folks dwell more healthy lives and making the wellbeing method do the job better for every person by simplifying the overall health treatment working experience, assembly consumer health and fitness and wellness requires, and sustaining trustworthy interactions with care vendors. In the United States, UnitedHealthcare offers the complete spectrum of well being gain plans for individuals, businesses, and Medicare and Medicaid beneficiaries, and contracts right with more than 1.3 million medical professionals and care experts, and 6,500 hospitals and other treatment facilities nationwide. The company also provides wellbeing benefits and delivers care to people today through owned and operated health care amenities in South The united states. UnitedHealthcare is one of the corporations of UnitedHealth Team (NYSE: UNH), a diversified wellbeing care enterprise. For far more information and facts, go to UnitedHealthcare at www.uhc.com or comply with @UHC on Twitter.

About Peloton

Peloton (NASDAQ: PTON) is the major connected physical fitness system with a highly engaged group of nearly 7 million Customers around the globe. A class innovator at the nexus of health, technologies, and media, Peloton’s very first-of-its-sort membership platform seamlessly combines revolutionary components, distinctive software program, and unique information. Its planet-renowned instructors, mentor and encourage Customers to be the finest model of by themselves whenever, everywhere. Started in 2012 and headquartered in New York Metropolis, Peloton carries on to scale throughout the US, British isles, Canada, Germany, and Australia. For far more information, pay a visit to www.onepeloton.com.