Pennsylvania Senator John Fetterman has checked himself into Walter Reed National Army Health care Center for therapy of medical depression.
PENNSYLVANIA, Usa — Pennsylvania Senator John Fetterman has checked himself into Walter Reed Countrywide Military Clinical Center for treatment of scientific despair, in accordance to a statement from his main of employees, Adam Jentleson.
The statement reads in comprehensive:
“Very last evening, Senator John Fetterman checked himself into Walter Reed Nationwide Military services Professional medical Middle to acquire therapy for clinical melancholy. Although John has professional despair off and on in the course of his lifestyle, it only grew to become significant in new weeks.
On Monday, John was evaluated by Dr. Brian P. Monahan, the Attending Health practitioner of the United States Congress. Yesterday, Dr. Monahan suggested inpatient care at Walter Reed. John agreed, and he is getting cure on a voluntary basis.
After inspecting John, the medical practitioners at Walter Reed informed us that John is getting the treatment he requirements, and will quickly be back to himself.”
Fetterman was evaluated on Monday by the attending doctor of Congress, Dr. Brian P. Monahan, who advised inpatient care at Walter Reed, Jentleson said.
“John agreed, and he is getting cure on a voluntary basis,” Jentleson said. “After inspecting John, the physicians at Walter Reed advised us that John is getting the care he wants, and will quickly be back again to himself.”
Fetterman overcame a stroke days before previous May’s major election and expended the final five months on the marketing campaign trail recovering from the stroke.
Previous 7 days, Fetterman stayed two days in George Washington College, checking himself in just after turning into lightheaded. Fetterman’s business has said checks uncovered no proof of a new stroke or a seizure.
He carries on to suffer the aftereffects of the stroke, in certain auditory processing ailment, which can render somebody unable to communicate fluidly and immediately approach spoken conversation into that means.
Fetterman underwent surgical treatment to implant a pacemaker with a defibrillator to handle two heart conditions, atrial fibrillation and cardiomyopathy, and spent much of the summer time recovering and off the campaign trail.
Even with having time away from the Senate and continuing to recover from the stroke, Franklin&Marshall College political science professor Dr. Stephen Medvic doesn’t count on it to effects Fetterman’s capacity to provide.
“Unless this extends more than a pretty prolonged interval of time, I imagine this, all over again, another instance of when a senator techniques away to offer with whatever overall health challenges they’re dealing with. And that is not uncommon,” stated Dr. Medvic.
His spouse, Gisele Fetterman, asked for privateness for their family by way of Twitter:
Immediately after what he’s been by means of in the past yr, there is most likely no just one who wanted to speak about his very own wellness fewer than John. I’m so proud of him for inquiring for help and having the care he demands. pic.twitter.com/SfuwWTSUcG
Canada has delayed attempts to develop it is clinical assistance in dying program to consist of psychological disease. The plans lifted unease in a place that by now has a liberal assisted demise plan.
AILSA CHANG, HOST:
The expansion of healthcare support in dying to individuals with psychological sickness has been delayed by Canada’s Parliament for one more 12 months. The state presently enables medically assisted dying for some incurable health problems. But as Emma Jacobs experiences, mental well being conditions are even now up for debate. Remember to notice, this tale does consist of dialogue of suicide.
EMMA JACOBS, BYLINE: For John Scully, life has actually grow to be a living nightmare.
JOHN SCULLY: When I wake up, I go, oh, God, I have received to stop it. I have acquired to end it. I have to find a way to stop it.
JACOBS: Scully lives in Toronto. He was diagnosed with depression much more than 30 a long time ago and suffers from perform-linked PTSD and nervousness. He claims he has awful, vivid nightmares.
SCULLY: There is no way to cease it. And for the reason that of that, I’m also forever snooze deprived.
JACOBS: He has been seeing the progress of the enlargement of professional medical help in dying, recognized by its acronym, MAID, really carefully.
SCULLY: I basically physically bought the paperwork for MAID. I have it proper in this article.
JACOBS: Canada’s health-related assistance in dying software was built legally readily available to some older people with terminal health issues in 2016. In 2021, it was expanded to consist of people suffering with significant and persistent bodily disorders. But for a lot of, the prepare to prolong this to individuals suffering with entirely psychological health issues elevated concerns.
KWAME MCKENZIE: We really don’t have quite excellent ways of defining incurability for mental health difficulties.
JACOBS: Kwame McKenzie, a professor of psychiatry at the University of Toronto, suggests these candidates raise a range of challenging inquiries for psychiatrists.
MCKENZIE: If the system’s going to start having into that enterprise, in advance of it features individuals MAID, it should, in my mind, do every little thing it can to make positive that individuals get suitable procedure and social assistance. And I imagine at the minute, our devices in Canada are not carrying out that.
JACOBS: But prior court decisions necessarily mean it is really not a issue of if the designed enlargement will materialize, only when, factors out psychiatrist Mona Gupta.
MONA GUPTA: Now we have a quite diverse landscape, where by all kinds of people with continual medical conditions, who are not nearing the conclusion of daily life, could make requests.
JACOBS: Gupta, who operates at the investigation hospital of the University of Montreal, led a panel the Canadian govt tasked with figuring out how MAID should really be dealt with for applicants with psychological ailments as their only ailments. The tips incorporated extra funding for mental health and fitness and guidance for clinicians examining folks who implement for MAID. Their circumstances ended up centered partly on the knowledge of European nations that by now enable healthcare dying for individuals with psychological circumstances.
GUPTA: If we extrapolate from the European information, most people are turned away, really, and the persons who could essentially arrive at that threshold should to have had, will have experienced considerable histories of treatments.
JACOBS: In Toronto, John Scully feels that he has fatigued all accessible treatment options. He had hoped to use for MAID when it became open up to these whose irremediable problem is a psychological illness.
SCULLY: It presents a dignified dying. It gives a peaceful loss of life.
JACOBS: Governing administration ministers say the delay will give more time to share information and facts with practitioners all through the overall health treatment program. Scully insists that in the meantime, he is currently being denied his correct to regulate his demise. For NPR News, I am Emma Jacobs in Montreal.
CHANG: And if you or anyone you know may perhaps be looking at suicide or is in crisis, connect with or text 988 to access the Suicide and Disaster Lifeline.
NPR transcripts are developed on a hurry deadline by an NPR contractor. This textual content may perhaps not be in its remaining variety and may perhaps be up-to-date or revised in the upcoming. Accuracy and availability might change. The authoritative document of NPR’s programming is the audio file.
Tara Ghormley has always been an overachiever. She finished at the top of her class in high school, graduated summa cum laude from college and earned top honors in veterinary school. She went on to complete a rigorous training program and build a successful career as a veterinary internal medicine specialist. But in March 2020 she got infected with the SARS-CoV-2 virus—just the 24th case in the small, coastal central California town she lived in at the time, near the site of an early outbreak in the COVID pandemic. “I could have done without being first at this,” she says.
Almost three years after apparently clearing the virus from her body, Ghormley is still suffering. She gets exhausted quickly, her heartbeat suddenly races, and she goes through periods where she can’t concentrate or think clearly. Ghormley and her husband, who have relocated to a Los Angeles suburb, once spent their free time visiting their “happiest place on Earth”—Disneyland—but her health prevented that for more than a year. She still spends most of her days off resting in the dark or going to her many doctors’ appointments. Her early infection and ongoing symptoms make her one of the first people in the country with “long COVID,” a condition where symptoms persist for at least three months after the infection and can last for years. The syndrome is known by medical professionals as postacute sequelae of COVID-19, or PASC.
People with long COVID have symptoms such as pain, extreme fatigue and “brain fog,” or difficulty concentrating or remembering things. As of February 2022, the syndrome was estimated to affect about 16 million adults in the U.S. and had forced between two million and four million Americans out of the workforce, many of whom have yet to return. Long COVID often arises in otherwise healthy young people, and it can follow even a mild initial infection. The risk appears at least slightly higher in people who were hospitalized for COVID and in older adults (who end up in the hospital more often). Women and those at socioeconomic disadvantage also face higher risk, as do people who smoke, are obese, or have any of an array of health conditions, particularly autoimmune disease. Vaccination appears to reduce the danger but does not entirely prevent long COVID.
The most common, persistent and disabling symptoms of long COVID are neurological. Some are easily recognized as brain- or nerve-related: many people experience cognitive dysfunction in the form of difficulty with memory, attention, sleep and mood. Others may seem rooted more in the body than the brain, such as pain and postexertional malaise (PEM), a kind of “energy crash” that people experience after even mild exercise. But those, too, result from nerve dysfunction, often in the autonomic nervous system, which directs our bodies to breathe and digest food and generally runs our organs on autopilot. This so-called dysautonomia can lead to dizziness, a racing heart, high or low blood pressure, and gut disturbances, sometimes leaving people unable to work or even function independently.
The SARS-CoV-2 virus is new, but postviral syndromes are not. Research on other viruses, and on neurological damage from the human immunodeficiency virus (HIV) in particular, is guiding work on long COVID. And the recognition that the syndrome may cause its many effects through the brain and the nervous system is beginning to shape approaches to medical treatment. “I now think of COVID as a neurological disease as much as I think of it as a pulmonary disease, and that’s definitely true in long COVID,” says William Pittman, a physician at UCLA Health in Los Angeles, who treats Ghormley and many similar patients.
Although 16 million U.S. sufferers is a reasonable estimate of the condition’s toll, there are other, more dire assessments. A meta-analysis of 41 studies conducted in 2021 concluded that worldwide, 43 percent of people infected with SARS-CoV-2 may develop long COVID, with about 30 percent—translating to approximately 30 million people—affected in the U.S. Some studies have offered more conservative numbers. A June 2022 survey reported by the U.S. National Center for Health Statistics found that among adults who had had COVID, one in five was experiencing long COVID three months later; the U.K. Office for National Statistics put the estimate at one in 10. Even if only a small share of infections result in long COVID, experts say, they will add up to millions more people affected—and potentially disabled.
Most of the first recognized cases of long COVID were in patients who needed extended respiratory therapy or who had obvious organ damage that caused lasting symptoms. People reporting neurological symptoms were often overlooked or dismissed as traumatized by their initial illness and hospitalization. But as 2020 came to an end, says Helen Lavretsky, a psychiatrist at the University of California, Los Angeles, “we started getting to a place of sorting through what was really going on … and it became very evident at that time that neuropsychiatric symptoms were quite prevalent,” most commonly fatigue, malaise, brain fog, smell loss and post-traumatic stress disorder, as well as cognitive problems and even psychosis.
Ghormley was in her late 30s and relatively healthy when she caught the virus, but she had underlying conditions—including rheumatoid arthritis and asthma—that put her at risk for severe COVID. She spent several days at home, struggling to breathe, and then she went to the hospital, where her blood pressure soared and her blood glucose dropped precipitously. She mostly recovered from this acute phase within a few weeks, but, she says, “I never really got better.”
Soon after coming home from the hospital, Ghormley developed what her husband called “goldfish brain.” “I’d put something down and have no idea where I put it,” she recalls. “It kept happening over and over. I was thinking, ‘This is getting weird.’ My husband said I was not remembering anything. I’d try to talk, and I knew what I wanted to say, but I couldn’t think of the word.”
“Everything fell apart for me,” says Tara Ghormley, who has been struggling with long COVID since 2020. Credit: Ewan Burns
She also experienced tremors, dramatic mood swings and painful hypersensitivity to sounds. “My husband opening a paper bag felt like knives stabbing me in the ear,” she recounts. Any exertion—physical or mental—left her exhausted and in pain. The changes were jarring to Ghormley, who prided herself on her sharp mind. “The thing that bothered me the most was that I was really having trouble thinking, speaking, remembering—trying to complete a task and having no idea what it was. Suddenly I had quite profound neurological deficits. Everything fell apart for me at that time. That was horribly traumatic … it kind of broke me. I didn’t feel like me.”
Roots of Dysfunction
As a veterinary internist, Ghormley says, it’s her job to problem solve when mysterious symptoms arise, including her own. “I was actively trying to find reasons and find what I could do.” She theorized that some of her neurological symptoms might be the result of thrombotic events, blood clots that can cause ministrokes. Several early studies showed that COVID attacks endothelial cells, which line blood vessels. That can lead to clotting and oxygen deprivation in multiple organs, including the brain. Even subtle disruption of endothelial cells in the brain could contribute to cognitive dysfunction.
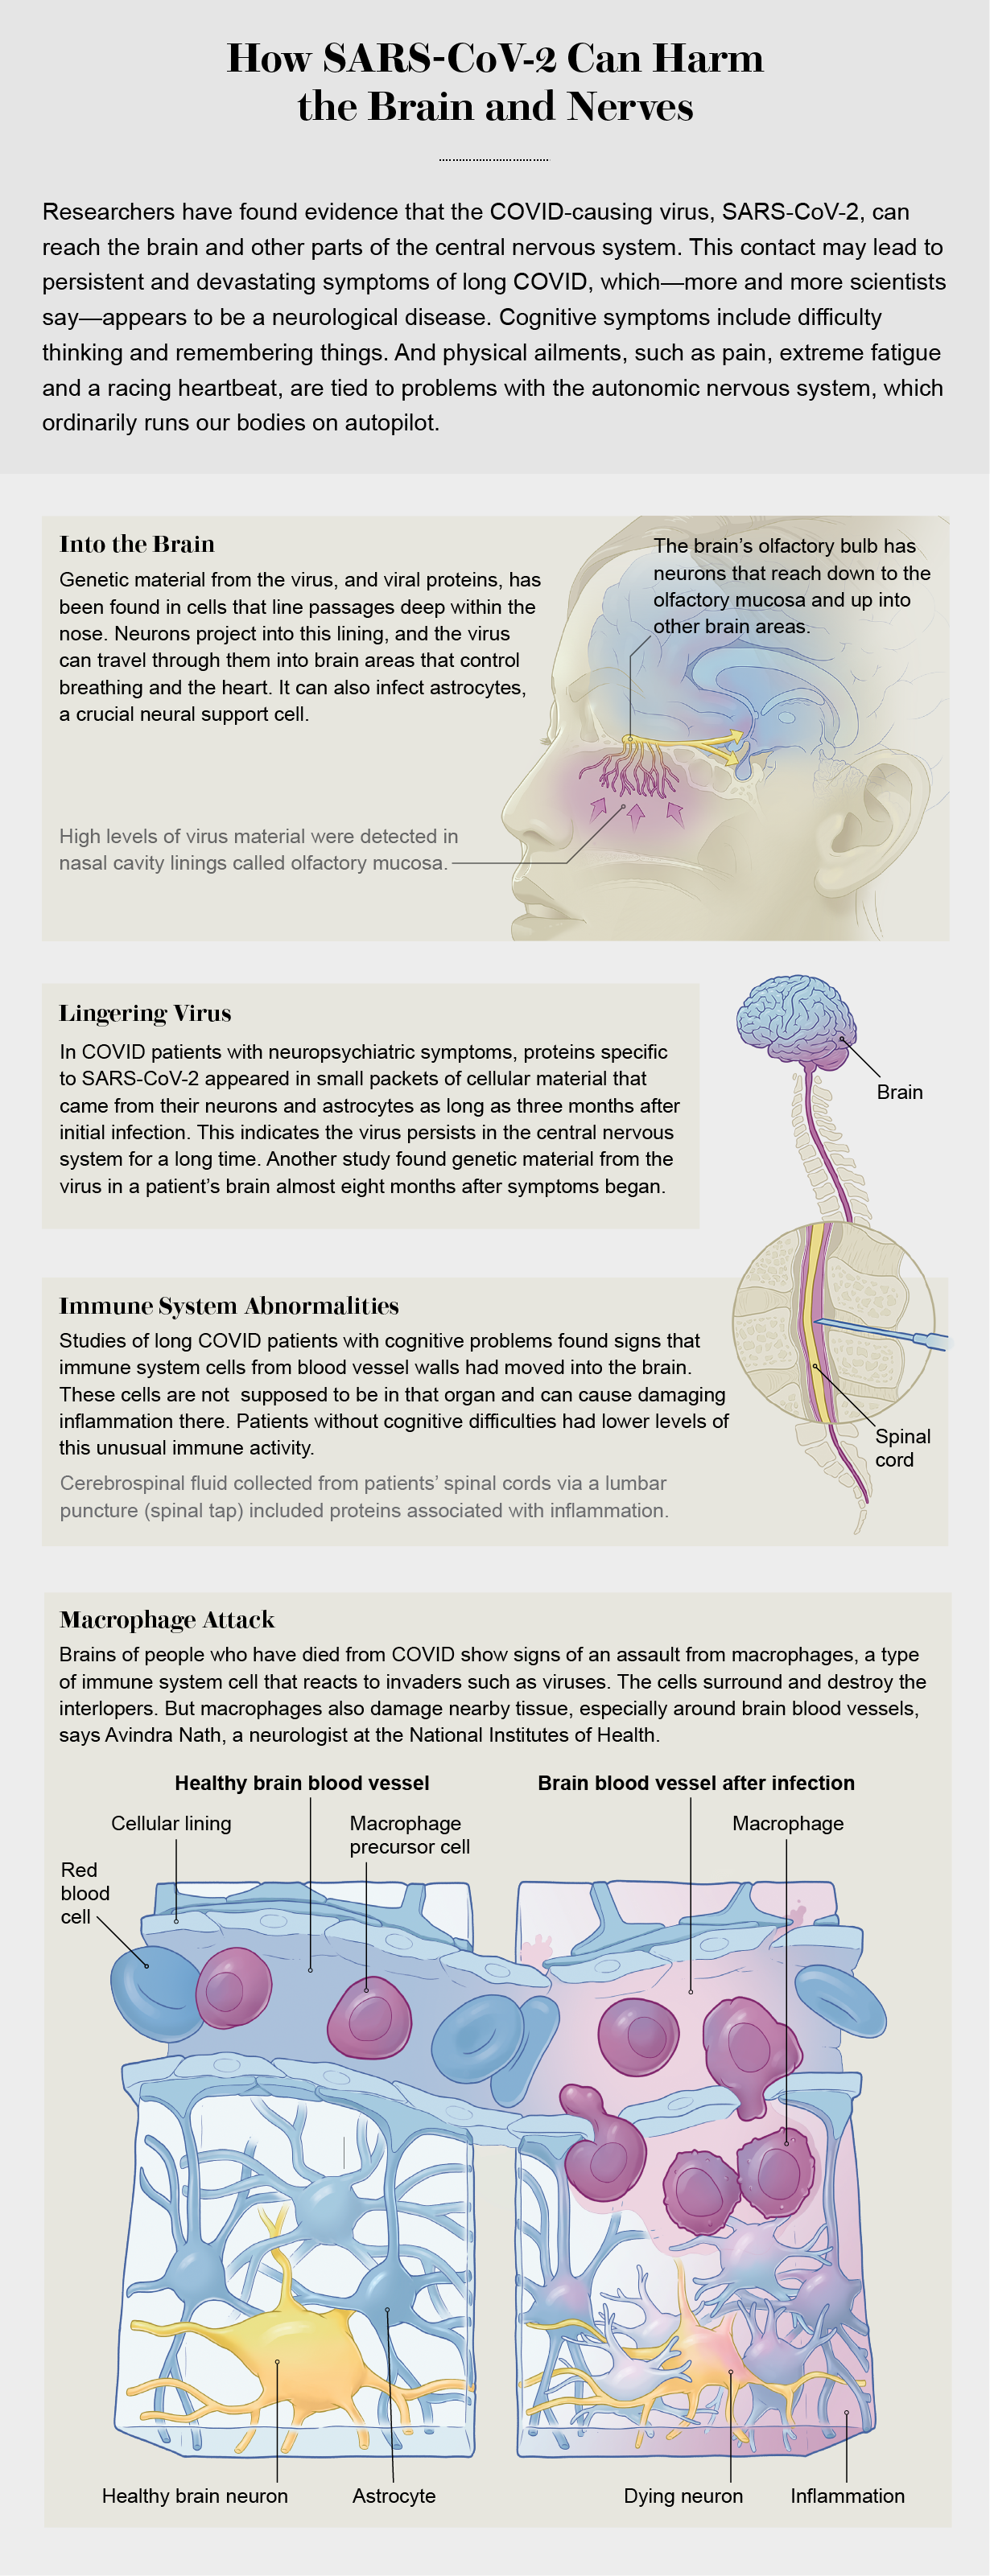
One study found that in people with neurological COVID symptoms, the immune system seems to be activated specifically in the central nervous system, creating inflammation. But brain inflammation is probably not caused by the virus infecting that organ directly. Avindra Nath, who has long studied postviral neurological syndromes at the National Institutes of Health, found something similar in an autopsy study of people who died of COVID. “When you look at the COVID brain, you don’t actually find [huge amounts of virus, but] we found a lot of immune activation,” he says, particularly around blood vessels. The examinations suggested that immune cells called macrophages had been stirred up. “Macrophages are not that precise in their attack,” Nath says. “They come and start chewing things up; they produce all kinds of free radicals, cytokines. It’s almost like blanket bombing—it ends up causing a lot of damage. And they’re very hard to shut down, so they persist for a long time. These are the unwelcome guests” that may be causing persistent inflammation in the brain.
Determining which patients have ongoing inflammation could help inform treatments. Early research identified markers that often are elevated in people with the condition, says Troy Torgerson, an immunologist at the Allen Institute in Seattle. Three cell-signaling molecules—tumor necrosis factor alpha, interleukin 6 and interferon beta—stood out in long COVID patients. But this pattern wasn’t found in absolutely everyone. “We’re trying to sort through long COVID patients and say, ‘This would be a good group to take to trials of an anti-inflammatory drug, whereas this group may need to focus more on rehabilitation,’” Torgerson says. He led a study (currently released as a preprint, without formal scientific review by a journal) in which his team measured proteins from the blood of 55 patients. The researchers found that a subset had persistent inflammation. Among those people, they saw a distinct immune pathway linked to a lasting response to infection. “One subset of patients does appear to have an ongoing response to some virus,” Torgerson says.
Isolated pockets of SARS-CoV-2 or even pieces of viral proteins may remain in the body well after the initial infection and continue to elicit an immune attack. The first solid evidence for “viral persistence” outside the lungs came in 2021 from researchers in Singapore who found viral proteins throughout the gut in five patients who had recovered from COVID as much as six months earlier. A study conducted at the University of California, San Francisco, found evidence for viral particles in the brains of people with long COVID. Scientists collected exosomes, or tiny packets of cellular material, released specifically from cells of the central nervous system. The exosomes contained pieces of viral proteins as well as mitochondrial proteins, which may indicate an immune attack on those vital cellular organelles. Amounts of such suspicious proteins were higher in patients with neuropsychiatric symptoms than in those without them.
The virus could linger in the brain for months, according to research conducted at the NIH and reported in Nature in December 2022. The autopsy study of 44 people who died of COVID found rampant inflammation mainly in the respiratory tract, but viral RNA was detected throughout the body, even in the brain, as long as 230 days after infection. Two other studies, both published last year in the Proceedings of the National Academy of Sciences USA, showed evidence that SARS-CoV-2 may infect astrocytes, a type of neural support cell, gaining entrance via neurons in the skin lining the nose.
Researchers are examining inflammatory signals in patients with long COVID in increasingly fine detail. A small study led by Joanna Hellmuth, a neurologist at U.C.S.F., found that patients with cognitive symptoms had immune-related abnormalities in their cerebrospinal fluid, whereas none of the patients without cognitive symptoms did. At the 2022 meeting of the Society for Neuroscience, Hellmuth reported that she had looked at more specific immune markers in people with cognitive symptoms and found that some patients had an elevated level of VEGF-C, a marker of endothelial dysfunction. Higher VEGF-C concentrations are associated with higher levels of immune cells getting into the brain, she says, and “they’re not doing their normal function of maintaining the blood-brain barrier; they’re distracted and perhaps activated.” Although the studies are small, Hellmuth adds, they reveal “real biological distinctions and inflammation in the brain. This is not a psychological or psychosomatic disorder; this is a neuroimmune disorder.”
What keeps the immune system in attack mode? According to Torgerson, “one option is that you’ve developed autoimmunity,” in which antibodies produced by the immune system to fight the virus also mark a person’s own cells for immune attack. The response to the virus “turns the autoimmunity on, and that doesn’t get better even when the virus goes away,” he says. Several studies have found evidence of autoimmune components called autoantibodies that interact with nerve cells in people with long COVID.
Clues about the inflammatory processes at work could point toward treatments for neurological symptoms. “If it’s a macrophage-mediated inflammatory process … intravenous immunoglobulin could make a difference [to] dampen the macrophages,” Nath says. The treatment, referred to as IVIg, contains a cocktail of proteins and antibodies that can mitigate an overactive immune response.
IVIg can also be used to block autoantibodies. And a therapy called rituximab that targets antibody-producing B cells provides “a time-tested therapy for a lot of autoantibody-mediated syndromes,” Nath says. Another strategy is to use corticosteroids to dampen immune activity altogether, although those drugs can be used for only a limited time. “That’s a sledgehammer approach, and you can see if it makes a difference. At least it gives you an idea that, yes, it’s an immune-mediated phenomenon, and now we need to find a better way to target it,” Nath says.
If the virus does hang around in some form, antiviral medications could potentially clear it, which might help resolve neurological symptoms. That’s the hope of scientists running a clinical trial of Paxlovid, Pfizer’s antiviral drug for acute COVID.
A Chronic Fatigue Connection?
Postviral syndromes have been documented for more than a century, arising after infection with viruses from HIV to the flu. Epstein-Barr virus, which causes mononucleosis, is one of several viruses linked to a condition called myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), which is estimated to affect at least one and a half million people in the U.S. ME/CFS bears striking resemblances to long COVID, with symptoms such as immune system dysregulation, fatigue and cognitive dysfunction. “One of the patterns we see is patients who definitely meet the criteria for ME/CFS. This is something we are seeing and treating all the time” in long COVID patients, Pittman says. ME/CFS can be severe, with some people losing mobility and becoming bedbound.
Credit: Now Medical Studios; Sources: “Neurovascular Injury with Complement Activation and Inflammation in COVID-19,” by Myoung-Hwa Lee et al., in Brain, Vol. 145; July 2022 (blood vessel reference); “Olfactory Transmucosal SARS-CoV-2 Invasion as a Port of Central Nervous System Entry in Individuals with COVID-19,” by Jenny Meinhardt et al., in Nature Neuroscience, Vol. 24; February 2021 (nasal passage reference)
Nath, who also studies ME/CFS, says that “we think mechanistically they are going to be related.” Researchers suspect that ME/CFS, like some cases of long COVID, could be autoimmune in nature, with autoantibodies keeping the immune system activated. ME/CFS has been difficult to study because it often arises long after a mild infection, making it hard to identify a viral trigger. But with long COVID, Nath says, “the advantage is that we know exactly what started the process, and you can catch cases early in the [development of] ME/CFS-like symptoms.” In people who have had ME/CFS for years, “it’s done damage, and it’s hard to reverse that.” Nath speculates that for long COVID, if doctors could study people early in the illness, they would have a better chance of reversing the process.
Torgerson hopes that researchers will ultimately come to better understand ME/CFS because of COVID. “COVID has been more carefully studied with better technology in the time we’ve had it than any other infectious disease ever. I think we’ll learn things that will be applicable to other inflammatory diseases driven by infection followed by an autoimmune process.”
Team Treatment
Ghormley, after months of illness, sought care at UCLA Health’s long COVID clinic, among the country’s few comprehensive, multidisciplinary programs for people with this syndrome. Even though her symptoms are rooted in nervous system dysfunction, she needed an array of medical specialists to treat them. The clinic grew out of a program aimed at coordinating care for medically complex COVID patients, says its director Nisha Viswanathan, an internist and primary care physician. In following up with COVID patients after several months, she realized that “we had a group of patients who still had symptoms. There was no understanding around the condition; we were just trying to see what we could offer them.” Viswanathan and others convened a biweekly meeting of UCLA Health doctors in pulmonology, cardiology, neurology, psychiatry and other specialties to discuss individual cases and overall trends.
At UCLA Health, Pittman coordinates Ghormley’s treatment. He says the interdisciplinary team is crucial to getting patients the best possible care. “Oftentimes there are so many symptoms,” and some patients have seen multiple specialists before arriving, but not necessarily the right ones. As long COVID primary care providers, he says, “we do the initial testing and get them to the right person.” For Ghormley, that list of providers includes Pittman, along with a neurologist, a pulmonologist, a cardiologist, a psychiatrist, a trauma counselor, a rheumatologist and a gynecologist.
The team approach has also been critical for doctors trying to understand a brand-new disease, Pittman says. “It’s been a very interesting journey from knowing almost nothing to knowing a little bit now, and we’re learning more every day, every week, every month,” he says. The term “long COVID” “is an umbrella, and I think there are multiple diseases under that umbrella.” Although each long COVID patient is unique, Pittman says, “we start to see patterns developing. And with Ghormley, we saw a pattern of dysautonomia, which we see frequently.”
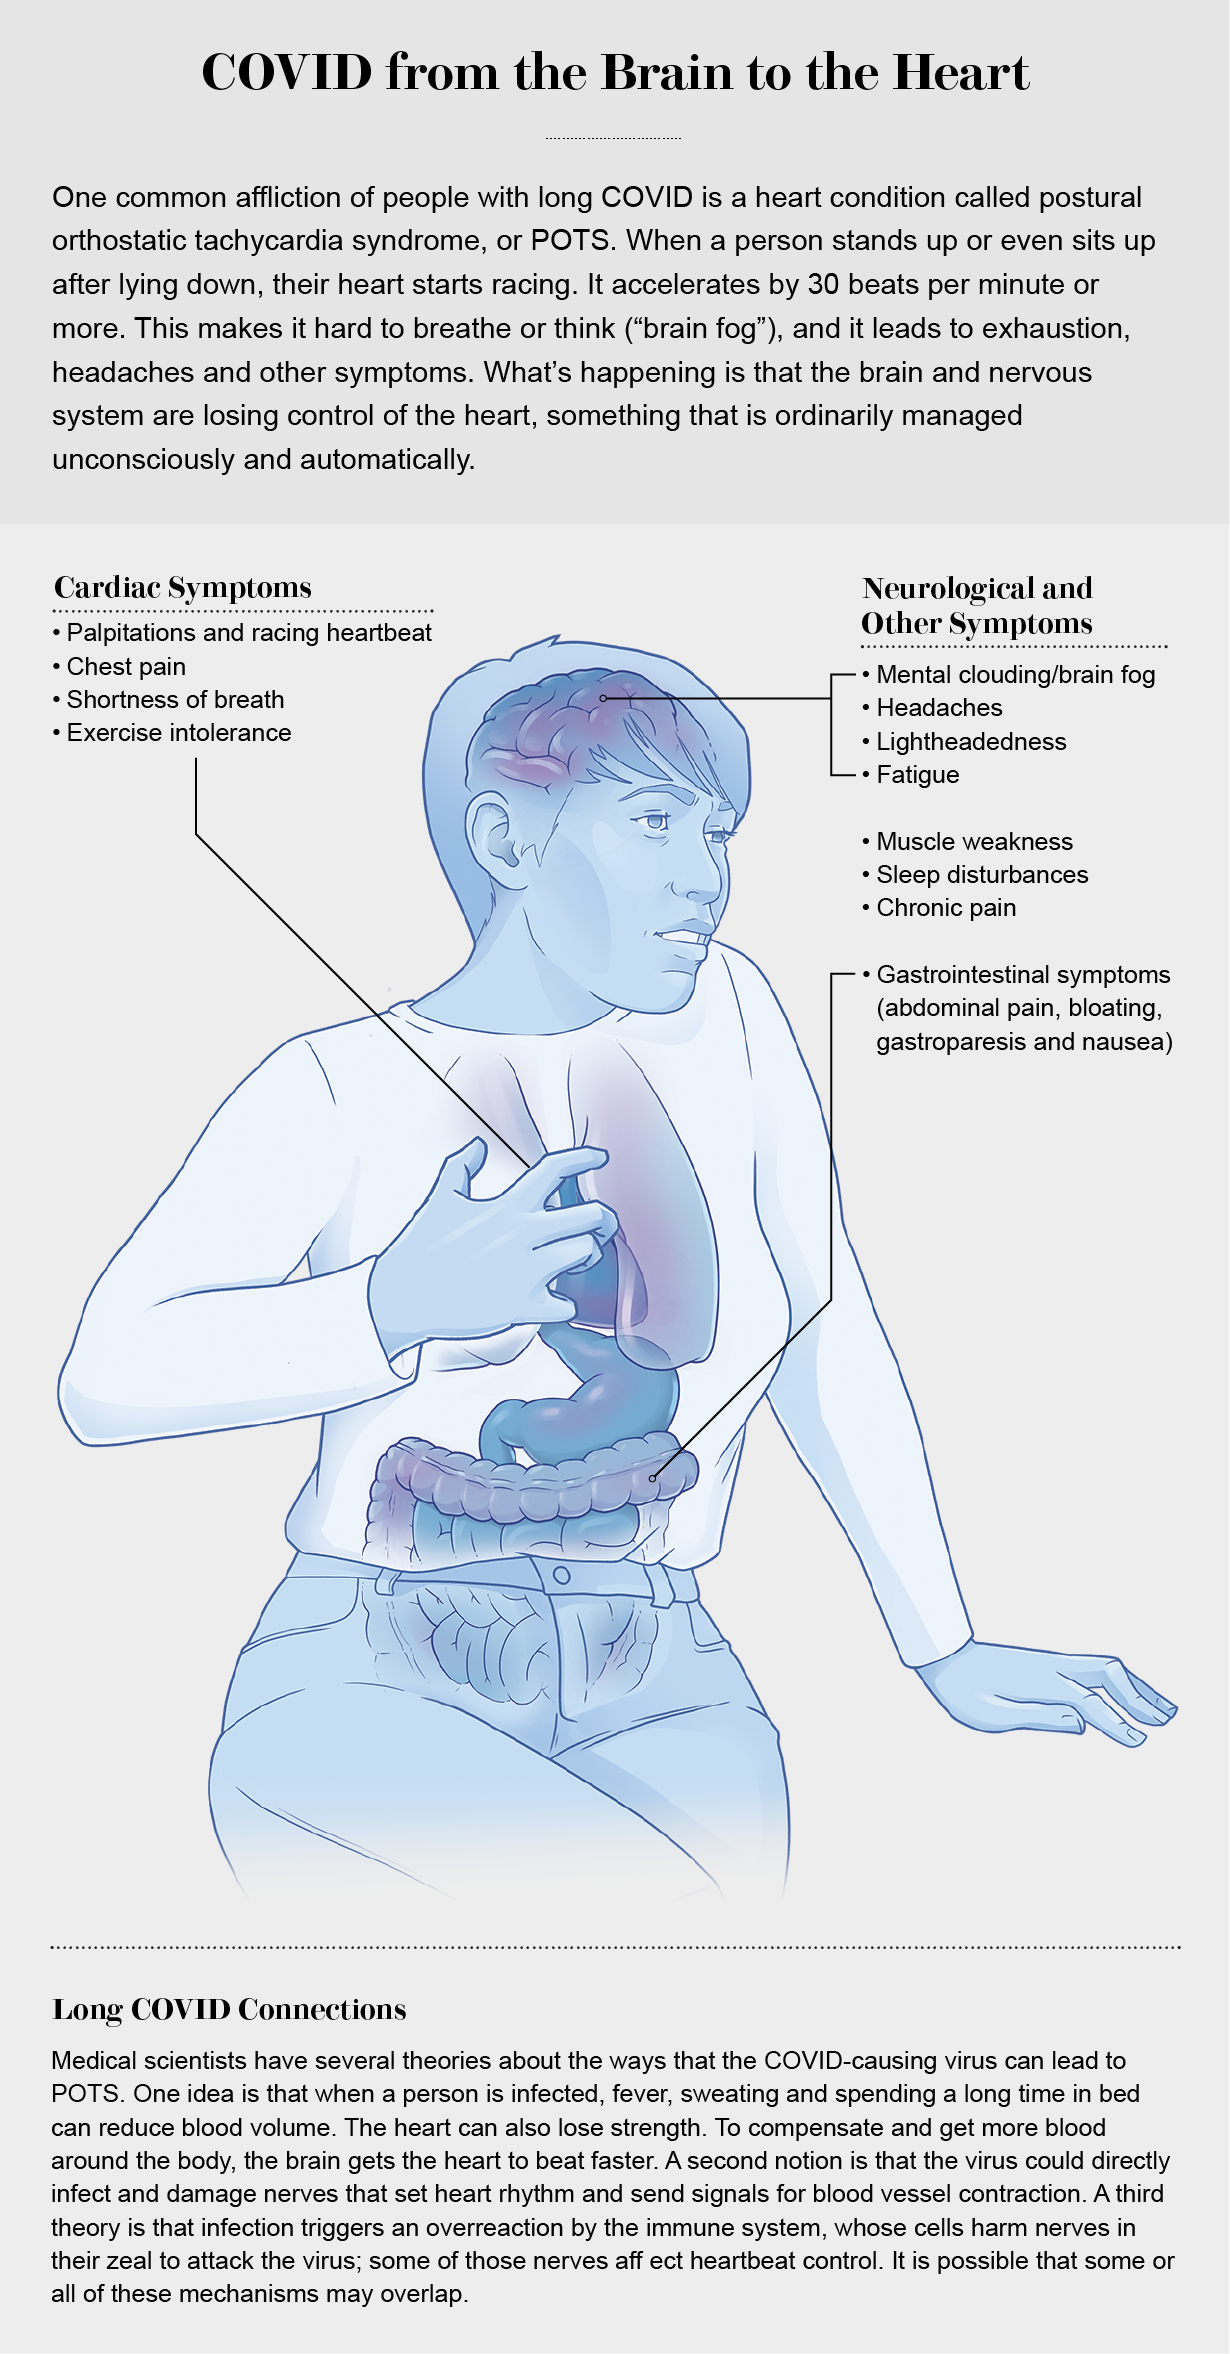
Dysautonomia impairs the autonomic nervous system, a network of nerves that branch out from the brain or spinal cord and extend through the body, controlling unconscious functions such as heartbeat, breathing, sweating and blood vessel dilation. For Ghormley, like many people with long COVID, dysautonomia takes the form of postural orthostatic tachycardia syndrome, or POTS. The syndrome encompasses a collection of symptoms that include a racing heart rate—particularly on standing—and fatigue, and it can cause bowel and bladder irregularities. POTS can also be a component of the exhaustion that comes with PEM. Although the symptoms may seem to affect the body, they stem from nervous system dysfunction.
Ghormley’s dysautonomia led her to see cardiologist Megha Agarwal at a UCLA clinic near her home. Many physicians are not familiar with POTS, but Agarwal is particularly attuned to it, having seen it in some of her patients before COVID hit. “There’s dysregulation of the nervous system, and so many things can cause it: some cancer therapies, viruses, autoimmune conditions.” Agarwal recognized POTS in Ghormley in the fall of 2020, when very little was known about long COVID. Now she believes “POTS is really what long-haul COVID is causing” in many patients. Luckily, Agarwal says, there are medical interventions that can help.
Tachycardia—the T in POTS—causes the heartbeat to speed up, contributing to exhaustion and fatigue in addition to stressing the heart itself. Drugs called beta-blockers (for the beta-adrenergic receptors they shut off in the heart) can lower the heart rate and improve symptoms. “When heart rate is controlled, not only does the pump improve,” Agarwal says, “[but people’s] energy improves, their fatigue is gone, and sometimes there’s better mental clarity.” For some patients like Ghormley, beta-blockers are not enough, so Agarwal adds a medication called ivabradine. “It’s a bit off-label, but it’s currently being aggressively studied” for POTS. For Ghormley, the combination led to real improvements, “so now she doesn’t feel like she ran the Boston Marathon when all she did was sit down and stand up at work or take a shower,” Agarwal says.
Among Ghormley’s toughest symptoms is her brain fog, a catchall term for a slew of cognitive problems that make it hard for her to function. For days when Ghormley works, her psychiatrist prescribes Adderall, a stimulant used to treat attention deficit hyperactivity disorder that helps her concentrate and stay focused. That has “helped immensely,” Ghormley says.
Ghormley credits her doctors and Agarwal in particular with doing the detective work to dig into her symptoms. “Nobody knew anything about it, but everyone listened to me,” Ghormley says. Perhaps because she was a professional from a medical field, no one “brushed me aside.”
That’s unusual for people with long COVID, many of them women, who are often dismissed by physicians who doubt their complaints are real. “Patients just don’t feel heard,” Viswanathan says. “I had a patient who told me everything, and after, I just said, ‘This must be so hard for you. I want you to know that everything you’re feeling is real, and I’ve seen so many patients like you.’ And she started crying. She said, ‘No one has told me that. I can’t tell you the number of times I was told it was in my head.’”
Credit: Now Medical Studio; Sources: “Postural Orthostatic Tachycardia Syndrome as a Sequela of COVID-19,” by Cameron K. Ormiston et al., in Heart Rhythm, Vol. 19; November 2022; “Long COVID-19 and Postural Orthostatic Tachycardia Syndrome—Is Dysautonomia to Be Blamed?” by Karan R. Chadda et al., in Frontiers in Cardiovascular Medicine; March 2022 (references)
In addition to drugs, other types of therapies, including physical therapy, can help improve some symptoms. But people who experience PEM face a particular challenge when using movement therapies. Pittman says the exertion can make these patients feel worse. “We don’t want patients to go to not moving at all, but sometimes the type of movement they’re doing may be flaring their symptoms.” He notes that often PEM strikes young, previously healthy people who will say, “‘I need to push myself,’ and then they go way too far and get worse. Our job is to try to find that middle ground and then make that consistent over time, so they’re not getting further deconditioned but they don’t have the PEM, which has been shown to set them back.”
The Long Haul
Some patients, Pittman says, “have the expectation that they’re going to come in, and within a month they’re going to be back to normal. And resetting those expectations can be really challenging. You have to be really empathetic because people’s lives have completely changed.” But sometimes patients’ quality of life can improve noticeably when they are able to adjust to a new normal. Still, he says, “patients have so many questions, and I can’t lead them down a physiological pathway. I can tell them there’s neuroinflammation, maybe there’s autoimmunity, but we still don’t have the answers. Sometimes it’s really tough for us to accept and for the patient to accept that we just have to try our best.”
A number of people, Viswanathan says, benefit from reducing various treatments they have accumulated. Some people become so desperate that they will try anything from supplements to off-label medications to untested potions from the Internet. Stopping those sometimes leads to improved symptoms, she says.
Psychological care and support groups can help. Lavretsky adds that “lifestyle choices can play a huge role in improvement,” particularly better sleep habits and the use of breathing exercises to control anxiety. She tells people their bodies can heal themselves if the patients and clinicians find the right tools.
Whether that’s true for everyone remains to be seen, Viswanathan says. “We see many patients who have gotten better with time. I have patients whose symptoms have disappeared in the course of a year, or they disappear and occasionally flare up again.” But for some, she says, “it could last many years.”
“We’re going to be addressing this for probably decades,” Viswanathan says. “COVID is not going to go away so much as we’re just going to get used to living with it, but part of [that] means that people will continue to develop long COVID.”
Vaccination appears to reduce the risk of long COVID. But a study published in May 2022 in Nature Medicine suggests the protection, though real, is not as good as one might hope. The survey of electronic health records from the U.S. Department of Veterans Affairs looked at the relatively small portion of vaccinated people who subsequently became infected. They developed long COVID only 15 percent less often than unvaccinated people. “These patients can have symptoms for one to two years or longer, and so every month you’re racking up more patients. Even if it’s 15 percent less, the total population of patients is still growing and exploding,” Pittman says. The best way to avoid getting long COVID, experts all agree, is to avoid getting COVID at all.
The syndrome is still mired in a lot of medical uncertainty. Patients might have one or a combination of the problems investigated so far: Long COVID might be caused by viral particles that persist in the brain or other parts of the nervous system. Or it might be an autoimmune disorder that lasts long after the virus has disappeared. Maybe overactive immune cells continue to perturb the nervous system and nearby blood vessels. Fortunately, the increasing ability to recognize specific problems is helping clinicians hone treatments that give patients the best chance of recovery.
Although Ghormley says her care has dramatically improved her symptoms and allowed her to “do some normal things again,” she continues to experience flare-ups that make it impossible for her to work for weeks at a time. One day last year she skipped a dose of her heart medication and made a Target run in the southern California heat. “I got home and basically collapsed in the hallway. Since then, everything has been out of whack. If I try to move around, my legs give out.” Most frustrating—and scary—to Ghormley is the unpredictability of her symptoms. “They have changed so much; some are manageable, some debilitating. One thing will get better, and another thing comes back. I’m always hopeful that it’s going to get better, but I just don’t know.”
On Tuesday, November 29th, just a several days immediately after Thanksgiving, Mayor Eric Adams announced that the Town of New York would move up efforts to involuntarily hospitalize homeless individuals with serious mental illness, even if they did not depict a danger of violence. The announcement provoked wary, anxious responses from all sides, at the very least according to The New York Situations. A person government official called the exertion “deeply problematic,” when other people predicted authorized problems to the plan. Inquiries had been right away lifted about particularly how the plan would be used, and no matter whether the law enforcement had been the finest positioned group to implement it.
The Mayor himself famous that there were quite a few hundreds dwelling in general public sites who are “in urgent require of treatment and frequently refuse it,” and that the city would “make every effort to guide those who are suffering from psychological illness.” He confidently predicted that, “We will obtain a bed for everyone” in require of hospitalization.
Many general public advocates have been a lot less assured. “The mayor talked about a ‘trauma-knowledgeable strategy,’ but coercion is alone traumatic,” explained one. One more said, “Instead of applying the least restrictive tactic, we are defaulting to an extreme that takes away standard human legal rights.” But most have been careful, recognizing both that the plan was “well intentioned,” and that it was not likely to be productive thanks to the severe undersupply of inpatient and outpatient mental wellbeing care.1
In the meantime, Governor Gavin Newsome signed a new legislation strengthening involuntary treatment method in California earlier in the fall. In accordance to the Connected Push, Newsome signed the invoice over the objections of the ACLU, Human Rights View, Disability Legal rights California, and “numerous other companies.” However his action seems to be component of a gradual nationwide go toward lawfully mandated treatment method of serious mental disease, a transfer that revives fears of coercive, oppressive, and traumatizing responses to psychological disease.2 For some advocates, the dim prospect of an era of reinstitutionalization looms, fulfilled with renewed phone calls for “housing not handcuffs.”3
But The place Are all the Psychiatrists?
Curiously ample, there is just one group lacking from the range of mental wellness buyers, legal specialists, homelessness advocates, and social libertarians quoted in these stories: psychiatrists. Psychiatrists, it turns out, do not appear to have a outstanding public position in these discussions.4 And it is not tough to consider a motive for this. Involuntary procedure raises the specter of coercive psychiatry, and the graphic of the psychiatrist as a energy-hungry sadist. It revives and reinforces the hoary impact that the psychiatrist is an enforcer of social command rather than as a healer of the intellect. And this is an picture that pretty couple of psychiatrists wish to revisit.
There are 2 visuals intently tied to antipsychiatric emotions in the public consciousness: electroconvulsive therapy (ECT)5 and involuntary cure.6 ECT continues to linger in the general public intellect as a barbaric and unpleasant intervention which is more like a kind of torture than a treatment. Couple in the community understand that ECT is by far the most efficient and nicely established therapy for everyday living-threatening despair, as well as other significant psychiatric crises. Involuntary hospitalization, on the other hand, conjures up illustrations or photos of “the gentlemen in white coats” who display up to deprive those with mental sickness of their freedoms with out a phrase, slamming them in the van and driving off to the mental clinic without the need of a trace of because of approach. Involuntary cure, in the inaccurate images of community perception, lowers the individual with mental disease to the position of a nonperson, a noncitizen without having lawful or even human rights. It paints the psychiatrist as a harsh, uncaring instrument of an oppressive social order. Somebody, in fact, who only misuses the powers of a physician for the sake of energy and particular acquire. And below, just as with ECT, the general public perception is improper.
Involuntary Dedication: What the Public Does not Know
Involuntary Procedure is Typical in Health care Treatment. Involuntary care is not distinctive to psychiatry. In contrast to public impressions, involuntary therapy is a staple of all clinical care for significant and life-threatening disorders. Take into account, for occasion, an unconscious victim of a car or truck accident who is seriously injured. Do we wait on cure? Do we ponder if the particular person seriously desires treatment method? Of study course not. Health-related pros just carry on with the style of therapy that most folks would opt for in these types of a condition. Medical practitioners and nurses decide to intervene to protect lifestyle and restore overall health, as considerably as they are in a position. As the injured unique returns to standard consciousness, they can make a decision for on their own no matter whether to acknowledge or reject even more treatment method.
Or consider a marginally more advanced scenario. A medical center patient with delirium believes that she is in a noisy dance club, and insists on likely dwelling. Do we let her? Of program not. Healthcare facility team will detain her for cure, restraining her by tying her to the bed with gentle restraints if necessary. I would wager, in point, that there are hospital individuals restrained to their beds in each individual healthcare facility in this region appropriate now. When they have returned to their ordinary mental point out (or if spouse and children takes responsibility for their care), they can leave the healthcare facility and return dwelling at will.
The Ethics of Involuntary Treatment are the Same for Psychiatry as Other Health-related Specialties. The ethical principal is the similar for psychiatry as for other branches of medicine: people today with serious and existence-threatening ailments can refuse treatment, but only if they are in their typical state of mind to do so. They can refuse if and only if they are able to think as a result of and apply the choices they would make when in their healthy state of mind. If not, household, health-related pros, or other legally selected people today ought to make the selection on the patient’s behalf. A individual with lifestyle threatening most cancers can refuse cure, if they realize the mother nature and outcomes of their final decision.
Certainly, there is an more wrinkle involved with psychiatry: what about individuals with long-term health-related sicknesses that partially impair their choice-earning capability? To be precise, these with psychotic health problems may perhaps deal with the influence of unreal beliefs (delusions) or impaired cognition which profoundly impact their conclusion creating. At the exact time, they might keep some capacity to cause about the outcomes of their choices, and some skill to have them out. Ought to men and women in this position be permitted to refuse therapy? To be trustworthy, our culture does not know, and our investigation foundation is grossly inadequate.7 As a outcome, our culture is profoundly ambivalent about this question. So, although there is a definite ethical line which sets the boundaries for involuntary therapy, that line is wide and blurry. Numerous folks with chronic psychological disease discover by themselves astride it, in a decidedly unpleasant placement.
Psychiatrists Do not Force Any one to Do Anything. In the finish, what psychiatrists imagine about involuntary cure is not decisive. For the reason that psychiatrists do not choose whether to compel men and women to accept psychiatric cure. Psychiatrists do not have the potential to lock people today up or inject them with prescription drugs from their will. Only the state has the ability to power people today to do matters against their will. At most, a psychiatrist can do what other medical experts do: quickly interpret regulations for involuntary therapy right up until a choose can rule on the case. But it is the state that would make the conclusion about involuntary care, and, in a democracy, the state is probably to comply with the prevalent being familiar with of the community.
Psychiatrists Should Only Teach the Public on Involuntary Motivation, Not Tell It What to Do. Personally, I assume psychiatrists are clever to remain out of the discussion about distinct involuntary determination legislation. We do not make the choices about psychiatric treatment for the community as a complete or even our people individually. The public does not see us as impartial, science-centered professionals in regard to this dilemma. It sees us as folks who have a conflict of interest. Relatively than weigh in with an viewpoint on exactly how to make and put into action our rules, I believe that psychiatrists ought to attempt to educate the public (and governing administration officers) about the mother nature of their possibilities. I do feel that the community and even lots of governing administration officers are very cloudy and conflicted about a lot of of the choices they are earning. Encouraging them realize their selections involves exhibiting them that involuntary psychiatric remedy is not essentially distinct than other forms of involuntary health-related cure, and that psychiatrists, in this regard, are no different from any other type of health practitioner.
Dr Morehead is a psychiatrist and director of coaching for the basic psychiatry residency at Tufts Healthcare Middle in Boston. He usually speaks as an advocate for mental wellness and is creator of Science Above Stigma: Training and Advocacy for Psychological Overall health, posted by the American Psychiatric Association. He can be reached at dmorehead@tuftsmedicalcenter.org.
1 with respiratory failure will not be equipped to breathe freely on his/her very own as respiratory failure takes place when the lungs are not in a position to acquire enough oxygen into the blood therefore, a single will wrestle to breathe and may well have to have oxygen remedy. It is crucial to search for well timed healthcare notice without any hold off.
In an job interview with HT Way of living, Dr Arvind Kate, Pulmonologist at Zen Multispecialty Healthcare facility, shared, “Respiratory failure is noticed when the respiratory technique fails to get out sufficient carbon dioxide from your blood, setting up up in your system. Respiratory failure can be classified into two varieties – acute and long-term respiratory failure: hypoxemic and hypercapnic. You will be stunned to know that these fatal situations can guide to severe complications.”
He included, “Moreover, hypoxemic respiratory failure, or hypoxemia, occurs when 1 doesn’t have the required quantity of oxygen in the blood. Just one is regarded to have hypercapnic respiratory failure or hypercapnia when there is a big quantity of carbon dioxide in the blood.”
Speaking about will cause of respiratory failure, he exposed, “One can have respiratory failure owing to obstruction in the throat if some thing gets stuck up there, a spinal cord, or a mind injuries that impacts the breathing course of action. What’s more, acute respiratory distress syndrome owing to pneumonia, sepsis, head trauma and pancreatitis can also invite respiratory failure. Also, inhaling the smoke (from fires) or damaging fumes can guide to this issue.”
As for the hazard elements, he highlighted using tobacco, alcohol, a relatives background of respiratory ailment or circumstances, a weak immune program and persistent respiratory circumstances, this sort of as lung cancer, COPD or asthma can bring about respiratory failure. According to him, “Those who are known to have lower ranges of oxygen can experience indications like shortness of breath, drowsiness, and problems in executing day by day activities, this sort of as dressing or climbing stairs simply because of tiredness. Types with substantial carbon dioxide amounts are likely to come upon fast breathing, confusion, and head aches. 1 will be suggested treatment method following the diagnosis is verified.”
As for the complications, Dr Arvind Kate explained, “Unmanaged respiratory failure can turn deadly for you. It can direct to pulmonary embolism, pulmonary fibrosis, pneumonia, pneumothorax (collapsed lung) renal (kidney) failure, and hepatic (liver) failure.” Highlighting the procedure, he stated, “If you are acquiring issue then you will be approved agony medication to assistance you breathe freely. Even a respiration tube can be inserted into the mouth or nose and related the tube to a ventilator to allow you to breathe. Oxygen remedy can be advised to assistance you breathe. Aside from that, even a tracheotomy can be completed if necessary.”
The American Academy of Pediatrics recently published guidelines for the diagnosis and management of pediatric obesity for ages 2-19 years.
Initially, media outlets have seized on a very small part of the document that focuses on medication and surgery treatments for severe obesity. While these treatments for children certainly deserve consideration, there is so much more to these guidelines than that.
The guidelines emphasize the complexity of pediatric obesity as a medical problem but also a socioeconomic, psychological, cultural and racial problem. A total of 19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of all children in the United States have obesity. It is a chronic medical problem associated with increased disability and disparity. Having overweight makes it more likely that a child will have diabetes, heart disease, high blood pressure, arthritis, chronic pain and depression. And, it is associated with increased health care expenditure; in fact, the document quotes a cost of $9.4 to $14 billion lifetime medical costs for the population of 10-year-olds with obesity alone.
A child has obesity if they are greater than the 95th percentile for body mass index. The precursor to this is overweight, which is a BMI in the 85th to 95th percentile. While numbers certainly matter, most pediatricians have moved away from strict BMI discussions in favor of expressing concerns for current and long-term health, mental health and family history. There is a long history of judgment and stigma conveyed towards children with overweight/obesity from both the medical establishment and society in general.
This publication emphasizes the importance of awareness of this stigma and moving past it to recognize weight concerns as a medical diagnosis not a personal or parenting failure. The first step towards reversing this stigma is to move to person-first language: a child with obesity, not an obese child, or a teen with overweight, not who is overweight.
Messages from report
Important take-home messages from the document include:
— Obesity and overweight are multifactorial problems that must be addressed individually, locally and globally. The first step towards improving the lives of those affected by obesity is to acknowledge and begin to understand the complexity of the problem.
— The greater the number of Adverse Childhood Experiences, the greater the likelihood of obesity in a child. Poverty, mental illness and divorce all serve as increased risk factors for obesity.
— Obesity is a chronic disease that leads to metabolic and anatomical changes. Children with obesity become adults with obesity. They are at risk for heart disease, diabetes, high cholesterol, mobility challenges and mental health disorders.
— Socioeconomic status and living in an under-resourced community have a direct correlation with pediatric obesity. If future programs are to be successful, they must address these big problems in addition to focusing on the individual child. Food insecurity has been shown to alter eating patterns and lead to higher risk of overweight.
— Neighborhoods matter: A prevalence of fast food restaurants, safe outdoor play and fresh produce all have an impact on pediatric obesity. Communities who take these things into consideration can make changes to have long-term effects on this problem.
— Parents have the greatest effect on childhood obesity. A combination of genetics, culture and habits contribute to the passing on of obesity from parent to child. Maternal weight gain during pregnancy to controls on screen time of adolescents and everything in between, exemplify the many diverse ways parents affect a child’s risk of obesity. Healthy weight maintenance can only be achieved through family-focused care.
Multidisciplinary approach
The guidelines recommend that pediatricians evaluate children and teens with overweight and obesity carefully including a complete history, family history, physical exam and lab work. While the initial screening may take place at a wellness checkup, the time needed to properly address this problem will require follow-up appointments.
Further, a multidisciplinary approach using a dietitian, physical therapy and mental health provider expertise is essential after the diagnosis of obesity. It is also critical that providers make “co-morbid” diagnoses such as diabetes, sleep apnea, high blood pressure or depression and begin to address those medically.
Early intervention for problems such as these has been shown to decrease long-term impact and even reverse detrimental changes.
The guidelines share recommendations for 26 or more hours of face-to-face, family-centered, multi-component intervention being an effective way to treat pediatric obesity. This includes practical nutritional expertise, exercise support and behavioral therapy.
Availability of these types of care are very limited in Lancaster and nationwide. Pediatricians must work to provide access to what is available while advocating for the development of improved services in their communities.
Small changes
Providers are encouraged to help families focus on small changes such as eliminating sugar beverages or adding in 60 additional minutes of exercise a week.
Despite some media-coverage emphasis, the use of medication or surgery to combat pediatric obesity is a very small part of the content.
There are several medications available for use in children over the age of 12 that can be used as an adjunct to other therapies for children and teens whose condition requires further intervention.
Some of these medications require off-label use, and most of them have side effects, for these reasons many pediatricians may choose to refer a child to a Weight Management Expertise Clinic for surveillance. There is no evidence to suggest that medication alone is a sufficient treatment for pediatric obesity.
The American Academy of Pediatrics guidelines state that bariatric surgery has been shown to be safe and effective in children over the age of 12. Any child or teen with a consistent BMI greater than 35 can be considered for escalated care in the form of intensive therapies, and perhaps medication and/or surgery. Eligibility for bariatric surgery is based on multiple factors, with the presence of secondary problems such as diabetes placing more urgency on intervention.
The American Academy of Pediatrics publishes guidelines like this to inform and guide providers, but also for the importance of advocacy. Guidelines like these will hopefully affect decisions at a local and national level about things like physical education, housing developments, programs to address food insecurity, and of course insurance coverage.
If you are concerned about your child’s weight, start with their healthcare provider. Remember that overweight and obesity are chronic, multifactorial diagnoses that can respond to many different interventions.
Educate yourself about your family history, and consider other problems that could be contributing to your child’s weight gain. And finally, consider starting with small, household-wide changes, as they have been shown to make a big difference.
Dr. Pia Fenimore, of Lancaster Pediatric Associates, answers questions about children’s health. You can submit questions at Features@LNPnews.com.
Success! An email has been sent with a link to confirm list signup.
Error! There was an error processing your request.