TODAY’S Al Roker has shared an emotional update on his recovering well being in a new video from his family’s wintertime getaway.
On Tuesday, just months soon after the meteorologist’s scary hospitalization, Al shared just one of the most up-to-date major advancements he’s built as he continues to heal.
4
Al Roker shared some delighted news with enthusiasts on TuesdayCredit history: Instagram
4
The Nowadays display host unveiled he is been acquiring an less difficult time with with his respiratory, following a hospitalization for blood clots in his lungs and legsCredit score: Instagram/alroker
Al and his wife, Deborah Roberts, have been executing their best to hold anxious supporters updated on his development right after he returned from the medical center before this month.
In a new Instagram put up, the weatherman shared a video clip of a roaring fire he was savoring inside of at their Upstate New York getaway property.
In the caption, Al unveiled that he was experience some optimistic emotions around his latest wellbeing update.
The Nowadays host wrote: “Hope your Tuesday provides you health and joy.
“Being in a position to breathe deeply though seeing a fireplace is my happy position.”
Followers hopped into the responses area to share how glad they were being to hear that Al, who endured blood clots in his legs and lungs, is having an a lot easier time.
A single energized follower wrote: “Breathing deeply is a great issue. Continue on to recuperate.”
A different sweetly shared: “I had the very same overall health difficulty you are working with now. Remaining able to just take a deep breath and a total shower was rewarding. Continue to keep healing.”
Most read in Entertainment
“Miss you Al. Joyful you are getting much better just about every day,” a 3rd gushed.
“Happy you are obtaining again to your old self,” said a fourth enthusiast.
Health Fight
The Tv set star has experienced a hard stop to 2022 following he revealed in November that he was suffering from blood clots in his legs and lungs.
Following returning to his New York Town dwelling from the clinic a few months in the past, Al and his household decided to escape the metropolis and head upstate for the holidays.
His spouse, Deborah, went dwell on Instagram more than the weekend to give followers a bit of an update on everything.
Bundled up in a puffy jacket and hat, she stood in the snow exterior their residence to gush about how substantially she and her family members are taking pleasure in currently being in the “winter wonderland.”
While “Al stepped away for a small while” and was not in a position to join her for the sweet chat with fans, Deborah did make positive to share the latest on his highway to recovery.
The ABC correspondent began: “I just typically required extra than something else required to say to all of you, I hope you have a excellent holiday break weekend.
“I want to thank you for all of your excellent wishes and warm ideas and prayers, and just uplifting ideas more than the last handful of weeks. It has manufactured these a change.”
Deborah went on to incorporate: “I wished to tell you all that Al is searching much better each working day. He is accomplishing very well.
“He is trying to put on bodyweight, which is, I consider, the 1st time he’s experienced that challenge, he suggests, in his lifetime.
“But he is carrying out perfectly, and we are so, so happy to tell you that.”
4
Al and his household, which include spouse Deborah, lately headed to Upstate New York for a very little getaway for the holiday seasonsCredit score: Instagram/debrobertsabc
4
The meteorologist’s wife has been holding lovers current on Al’s enhancing wellness, as perfectlyCredit history: Instagram
TODAY’S Craig Melvin and Sheinelle Jones have offered enthusiasts the reward of a new update on how Al Roker is performing immediately after recently returning residence from the hospital.
Cardinal Dolan, the Archbishop of New York, has sweetly requested the hosts about the missing meteorologist whilst stopping by the morning exhibit on Friday.
4
Craig Melvin and Sheinelle Jones shared a wellbeing update on their co-host Al RokerCredit rating: NBC
4
Al is now recovering after struggling blood clotsCredit: Instagram/debrobertsabc
To kick off their “tradition,” as Sheinelle set it, of owning Cardinal Dolan in the studio around this time of the calendar year, the trio all toasted with some eggnog.
The Currently show guest obtained points off on a cheery notice by cracking a joke about the efficiency of the drink.
Craig could not quit laughing soon after Cardinal Dolan stated: “It won’t be the 12 Days of Christmas, it could be the 12-stage method of Christmas if we retain [this up], wow!”
He then immediately switched to a extra serious issue and requested about how Al is undertaking amid his wellness issues.
Sheinelle unveiled that they ended up actually “texting with him this morning” and planned to speak about him a bit.
Cardinal Dolan sweetly questioned: “Is he undertaking Ok?”
Appreciating his inquiry about the missing host, Sheinelle replied: “Yes! Thank you for inquiring.”
To share a little bit much more about how Al’s undertaking, Craig jumped in: “He is on the highway to restoration. He is much improved. But say a exclusive prayer for our pal.”
Most study in Leisure
Lightening up the temper at the time more, Cardinal cracked Craig up once more as he joked: “Well, with out him, there is a lot more eggnog!”
“I have a experience we’ll get a textual content from him in just a moment,” Sheinelle teasingly warned the visitor.
Al not long ago discovered that Craig has been serving to out with his recovery by sending him some wholesome surprises.
On Wednesday, Al took to Instagram to post a online video of his protein shake and shared that he acquired the ingredients to make it from his co-host.
Although Al could not be noticed in the clip, only his hand, he did a voiceover to go by means of the techniques of putting the consume together.
The meteorologist instructed admirers: “So my Now relatives put with each other a do-it-your self smoothie kit- frozen fruit, peanut butter, protein powder.
“And I made my very first protein shake from my buddies, Mr. Melvin and props to Currently Food for finding it alongside one another and acquiring it in excess of right here.”
“I are not able to wait around,” Al explained, prior to he picked up the cup, took a sip, and included: “Mmmm. Yummy!”
The tune Clean Operator by Sade performed in excess of the movie.
The meteorologist captioned the write-up: “Thanks @todayshow and @todayfood family for a bunch of #diy #proteinsmoothie kits @craigmelvinnbc @katie.stilo #thebest.”
Al has been off from the Now demonstrate due to the fact early November, owing to currently being hospitalized with blood clots in his lungs and legs.
After returning property a few of weeks ago, the Television host resolved to escape New York Town this 7 days and head upstate for the holiday seasons.
Al’s wife Deborah Roberts shared a sweet loved ones picture from their car or truck trip with their daughter, Leila.
The ABC identity also shared a several scenic snaps from their upstate household, which include one particular searching out a window at the snowy landscape.
4
The meteorologist just lately shared that Craig is aiding him with his restoration by sending around elements for protein shakesCredit score: Instagram / Al Roker
4
Al and his family escaped the town this week to head upstate for the holiday seasonsCredit rating: Instagram/debrobertsabc
Stark racial disparities in maternal and infant health in the U.S. have persisted for decades despite continued advancements in medical care. The disparate impact of the COVID-19 pandemic for people of color has brought a new focus to health disparities, including the longstanding inequities in maternal and infant health. Additionally, with Roe v. Wade now overturned, increased barriers to abortion for people of color may widen the already existing large disparities in maternal and infant health. Recently, there has been increased attention and focus on improving maternal and infant health and reducing disparities in these areas, including a range of efforts at the federal level. This brief provides an overview of racial disparities for selected measures of maternal and infant health, discusses the factors that drive these disparities, and provides an overview of recent efforts to address them. It finds:
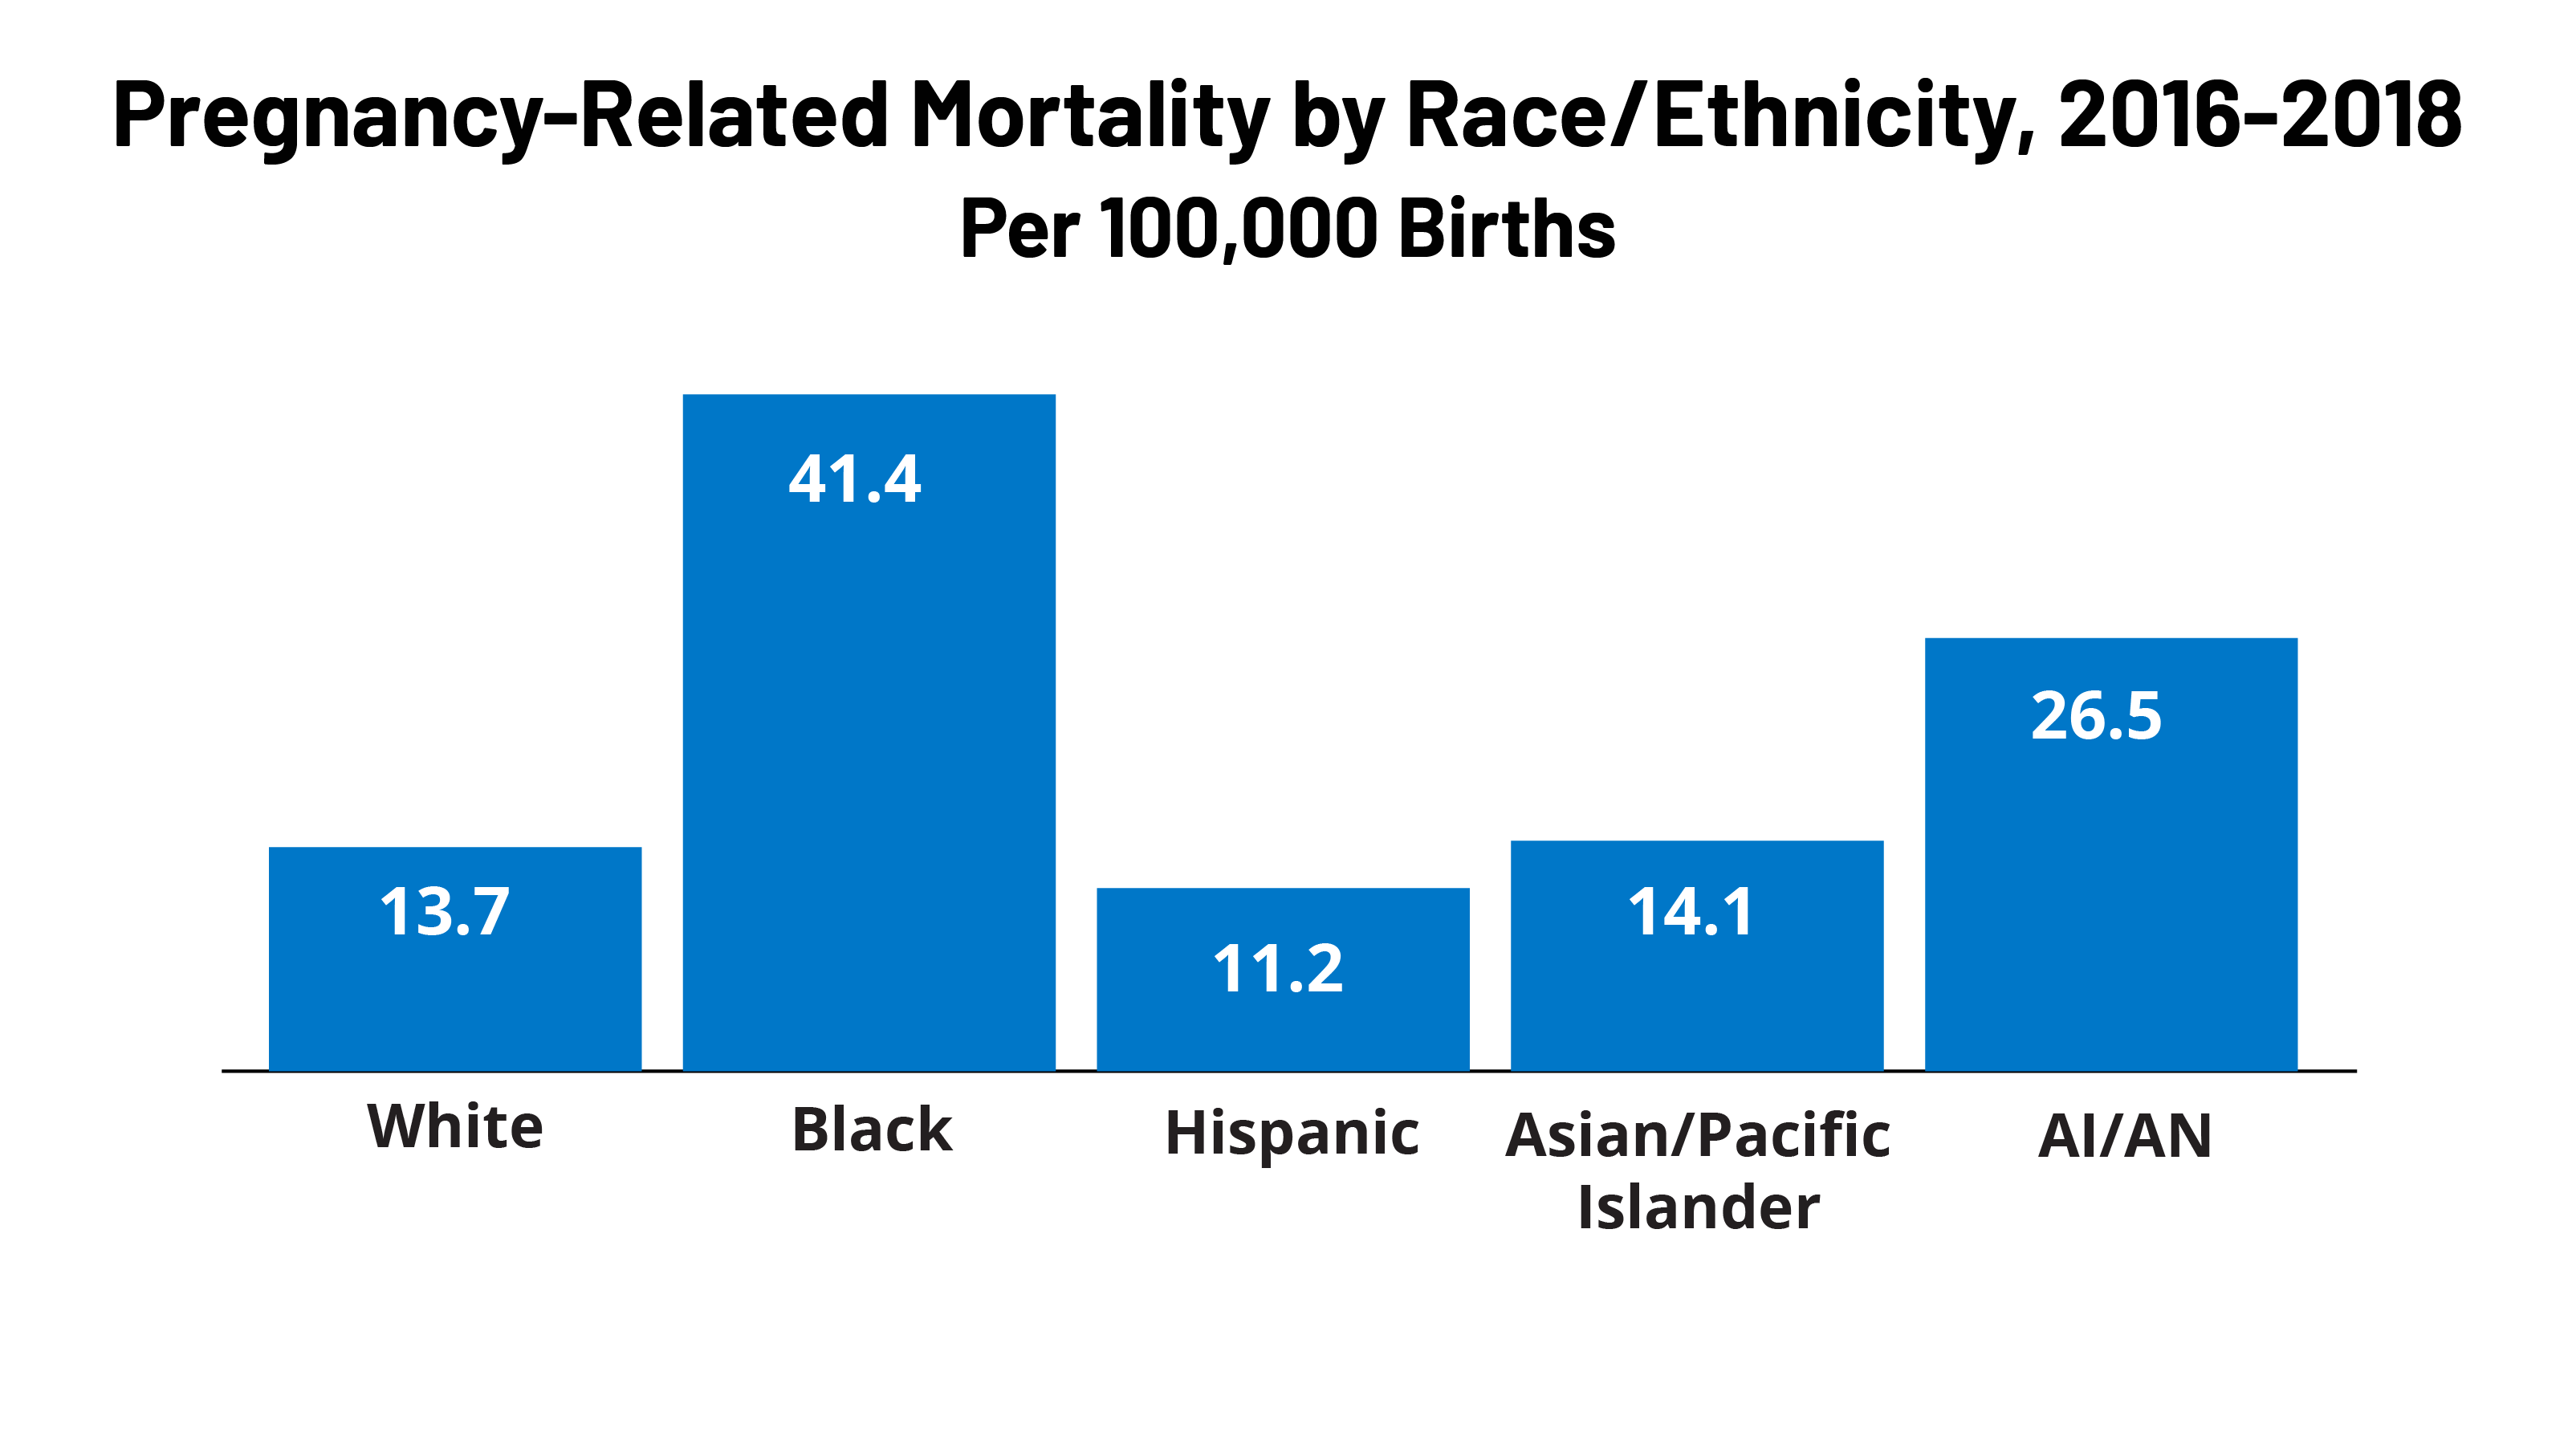
Black and American Indian and Alaska Native (AIAN) women have higher rates of pregnancy-related death compared to White women. Pregnancy-related mortality rates among Black and AIAN women are over three and two times higher, respectively, compared to the rate for White women (41.4 and 26.2 vs. 13.7 per 100,000). Black, AIAN, and Native Hawaiian and Other Pacific Islander (NHOPI) women also have higher shares preterm births, low birthweight births, or births for which they received late or no prenatal care compared to White women. Infants born to Black, AIAN, and NHOPI people have markedly higher mortality rates than those born to White women. Maternal death rates increased during the COVID-19 pandemic and racial disparities widened for Black women.
Maternal and infant health disparities are symptoms of broader underlying social and economic inequities that are rooted in racism and discrimination. Differences in health insurance coverage and access to care play a role in driving worse maternal and infant health outcomes for people of color. However, inequities in broader social and economic factors and structural and systemic racism and discrimination are primary drivers for maternal and infant health. Notably, disparities in maternal and infant health persist even when controlling for certain underlying social and economic factors, such as education and income, pointing to the roles racism and discrimination play in driving disparities.
The increased awareness and attention to maternal and infant health have contributed to a rise in efforts and resources focused on improving health outcomes in these areas and reducing disparities. These include efforts to expand access to coverage and care, increase access to a broader array of services and providers that support maternal and infant health, diversity the health care workforce, and enhance data collection and reporting. However, addressing social and economic factors that contribute to poorer health outcomes and disparities will also be important. Moreover, the persistence of disparities in maternal health across income and education levels, points to the importance of addressing the roles of racism and discrimination within the health care system as part of efforts to improve health and advance equity.
Introduction
The COVID-19 pandemic has exacerbated longstanding disparities in health and health care for people of color, including stark disparities in maternal and infant health. Despite continued advancements in medical care, rates of maternal mortality and morbidity and pre-term birth have been rising in the U.S. Maternal and infant mortality rates in the U.S. are far higher than those in similarly large and wealthy countries, and people of color are at increased risk for poor maternal and infant health outcomes compared to their White peers. Amid the COVID-19 pandemic, maternal deaths have continued to rise and racial disparities have further widened. Moreover, with the overturning of Roe v. Wade, increased barriers to abortion for people of color may widen the already existing large disparities in maternal and infant health. Together these factors have contributed to growing attention and efforts to improve overall maternal and infant health and reduce disparities in these areas.
This issue brief provides analysis of racial and ethnic disparities across selected measures of maternal and infant health, discusses the factors that drive these disparities, and provides an overview of recent efforts to address them. It is based on KFF analysis of publicly available data from CDC WONDER online database, the National Center for Health Statistics (NCHS) National Vital Statistics Reports, CDC Pregnancy Mortality Surveillance System, and a report from the US Government Accountability Office (GAO). While this brief focuses on racial/ethnic disparities in maternal and infant health, wide disparities also exist across other dimensions; for example, there is significant variation in some of these measures across states and disparities within rural communities.
Status of Racial Disparities in Maternal and Infant Health
Pregnancy-Related Mortality Rates
Approximately 700 women die in the U.S. each year as a result of pregnancy or its complications. Pregnancy-related deaths are deaths that occur within one year of pregnancy. Approximately one third (31{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) occur during pregnancy, another third (36{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) occur during labor or within the first week postpartum, and the remaining third (33{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) occur one week to one year postpartum, underscoring the importance of access to health care beyond the period of pregnancy. Recent data has found that more than eight out of ten (84{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}) pregnancy-related deaths are preventable. Although leading causes of pregnancy-related death vary by race and ethnicity, cardiovascular conditions are the leading cause of pregnancy-related death among women overall, highlighting the importance of care for chronic conditions on pregnancy-related outcomes. More recent data from detailed maternal mortality reviews in 36 states found mental health conditions to be the overall leading cause of pregnancy related deaths.
Black and AIAN women have pregnancy-related mortality rates that are about three and two times higher, respectively, compared to the rate for White women (41.4 and 26.5 vs. 13.7 per 100,000 live births) (Figure 1). These disparities increase by maternal age. For example, the pregnancy-related mortality rate for Black women between ages 30 to 34 widens to over four times higher than the rate for White women (48.6 vs. 11.3 per 100,000), while the rate for AIAN women in the same age group is nearly four times as high as the rate for White women (41.2 per 100,000). Moreover, they persist across education levels. Notably, the pregnancy-related mortality rate for Black women who completed college education or higher is 5.2 times higher than the rate for White women with the same educational attainment and 1.6 times higher than the rate for White women with less than a high school diploma. There are small differences in the rate pregnancy-related death between Asian and Pacific Islander and White women (14.1 vs. 13.7 per 100,000), and the rate for Hispanic women is lower compared to that of White women (11.2 vs. 13.7 per 100,000). These findings may mask underlying differences in subgroups of these populations. Other research also shows that Black women are at significantly higher risk for severe maternal morbidity, such as preeclampsia, which is significantly more common than maternal death. Further, Black women have higher rates of admission to the intensive care unit during delivery compared to White women, which is considered a marker for severe maternal morbidity.
Maternal death rates increased during the COVID-19 pandemic and racial disparities widened for Black women. According to recent GAO analysis that examined maternal deaths during pregnancy or within 42 days of pregnancy, Black women had the highest maternal mortality rates across racial and ethnic groups during the pandemic in 2020 and 2021 and also experienced the largest increase when compared to the year before the pandemic in 2019 (Figure 2). The maternal mortality rate for Hispanic women was less than the rate for White women prior to the pandemic but increased significantly and was similar to the rate for White women in 2020 and 2021. Data show that most of the increase in maternal deaths in 2020 and all of the increase in 2021 can be attributed to COVID-19 related deaths, which were higher among Black and Hispanic women (13.2 and 8.9 per 100,000, respectively) compared to White women (4.5 per 100,000).
Birth Risks and Outcomes
Black, AIAN, and NHOPI women are more likely than White women to have certain birth risk factors that contribute to infant mortality and can have long-term consequences for the physical and cognitive health of children. Preterm birth (birth before 37 weeks gestation) and low birthweight (defined as a baby born less than 5.5 pounds) are some of the leading causes for infant mortality. Receiving pregnancy-related care late in a pregnancy (defined as starting in the third trimester) or not receiving any pregnancy-related care at all can also increase risk of pregnancy complications. Black, AIAN, and NHOPI women have higher shares of preterm births, low birthweight births, or births for which they received late or no prenatal care compared to White women (Figure 3). Notably, NHOPI women are four times more likely than White women to begin receiving prenatal care in the third trimester or to receive no prenatal care at all (19{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}). Black women also are nearly twice as likely compared to White women to have a birth with late or no prenatal care compared to White women (9{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} vs. 5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}).
While teen birth rates overall have declined over time, they are higher among Black, Hispanic, AIAN, and NHOPI teens compared to their White counterparts (Figure 4). In contrast, the birth rate among Asian teens is lower than the rate for White teens. Many teen pregnancies are unplanned, and pregnant teens may be less likely to receive early and regular prenatal care. Teen pregnancy also is associated with increased risk of complications during pregnancy and delivery, including preterm birth. Teen pregnancy and childbirth can also have social and economic impacts on teen parents and their children, including disrupting educational completion for the parents and lower school achievement for the children. The drivers of teen pregnancy are multi-faceted and include poverty, history of adverse childhood events, and access to comprehensive education and health care services. Research studies have found that increased use of contraception as well as support for comprehensive sex education have helped lower the rate of teen births nationally.
Reflecting these increased risk factors, infants born to women of color are at higher risk for mortality compared to those born to White women. Infant mortality is defined as the death of an infant within the first year of life, but most cases occur within the first month after birth. The primary causes of infant mortality are birth defects, preterm birth and low birthweight, maternal pregnancy complications, sudden infant death syndrome, and injuries. Infants born to Black women are over twice as likely to die relative to those born to White women (10.4 vs. 4.4 per 1,000), and the mortality rate for infants born to AIAN and NHOPI women (7.7 and 7.2 per 1,000) is nearly twice as high (Figure 5). The mortality rate for infants born to Hispanic mothers is similar to the rate for those born to White women (4.7 vs. 4.4 per 1,000), while infants born to Asian women have a lower mortality rate (3.1 per 1,000). Data also show that fetal death or stillbirths—that is, pregnancy loss after 20-week gestation—are more common among Black women compared to White and Hispanic women. Moreover, causes of stillbirth vary by race and ethnicity, with higher rates of stillbirth attributed to diabetes and maternal complications among Black women compared to White women.
Factors Driving Disparities in Maternal and Infant Health
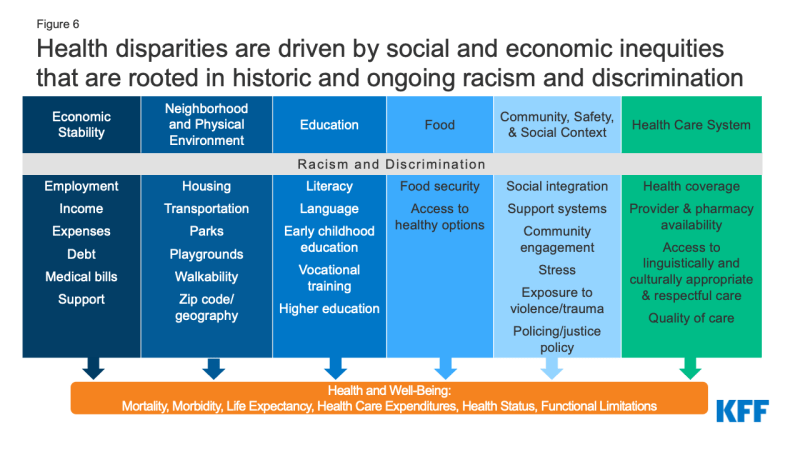
The factors driving disparities in maternal and infant health are complex and multifactorial. They include differences in health insurance coverage and access to care. However, broader social and economic factors and structural and systemic racism and discrimination, also play a major role (Figure 6). In maternal and infant health specifically, the intersection of race, gender, poverty, and other social factors shapes individuals’ experiences and outcomes. Recently there has been broader recognition of the principles of reproductive justice, which emphasize the role that the social determinants of health and other factors play in reproductive health for communities of color. Notably, Hispanic women and infants fare similarly to their White counterparts on many measures of maternal and infant health despite experiencing increased access barriers and social and economic challenges typically associated with poorer health outcomes. Research suggests that this finding, sometimes referred to as the Hispanic or Latino health paradox, in part, stems from variation in outcomes among subgroups of Hispanic people by origin, nativity, and race, with better outcomes for some groups, particularly recent immigrants to the U.S. However, the findings still are not fully understood.
Figure 6: Health disparities are driven by social and economic inequities that are rooted in historic and ongoing racism and discrimination
Disparities in maternal and infant health, in part, reflect increased barriers to care for people of color. Research shows that coverage before, during, and after pregnancy facilitates access to care that supports healthy pregnancies, as well as positive maternal and infant outcomes after childbirth. Overall, people of color are more likely to be uninsured and face other barriers to care. Medicaid helps to fill these coverage gaps during pregnancy and for children. However, women of color are at increased risk of being uninsured prior to their pregnancy and, historically, many have lost coverage at the end of the 60-day Medicaid postpartum coverage period due to lower eligibility levels for parents compared to pregnant women, particularly in states that have not implemented the Affordable Care Act (ACA) Medicaid expansion. Beyond health coverage, people of color face other increased barriers to care, including limited access to providers and hospitals and lack of access to culturally and linguistically appropriate care. These challenges may be particularly pronounced in rural and medically underserved areas. For example, research suggests that a rise in closures of hospitals and obstetric units in rural areas has a disproportionate impact in communities with larger shares of Black patients.
Research also highlights the role of racism and discrimination plays in driving racial disparities in maternal and infant health. Research has documented that social and economic factors, racism, and chronic stress contribute to poor maternal and infant health outcomes, including higher rates of perinatal depression and preterm birth among African American women and higher rates of mortality among Black infants. In recent years, research and news reports have raised attention to the effects of provider discrimination during pregnancy and delivery. News reporting and maternal mortality case reviews have called attention to a number of maternal deaths and near misses among women of color where providers did not or were slow to listen to patients. In one study, Indigenous, Hispanic, and Black women reported significantly higher rates of mistreatment (such as shouting and scolding, ignoring or refusing requests for help) during the course of their pregnancy. Even controlling for insurance status, income, age, and severity of conditions, people of color are less likely to receive routine medical procedures and experience a lower quality of care. One recent study of hospital births in Florida found that there were significant improvements in mortality for Black newborns who were cared for by Black physicians, pointing to the importance of culturally concordant or competent care. A KFF/The Undefeated survey found that most Black adults believe the health care system treats people unfairly based on their race, and one in five Black and Hispanic adults report they were personally treated unfairly because of their race or ethnicity while getting health care in the past year, with a higher share of Black mothers reporting unfair treatment. Black adults also were more likely than White adults to report feeling a provider didn’t believe they were telling the truth and being refused a test, treatment, or pain medication they thought they needed.
Current Efforts to Address Maternal and Infant Health Disparities
Increased awareness and attention to maternal and infant health have contributed to a rise in efforts and resources focused on improving health material and infant health outcomes and reducing disparities. These include efforts to expand access to coverage and care, increase access to a broader array of services and providers that support maternal and infant health, diversity the health care workforce, and enhance data collection and reporting.
In June 2022, the Biden Administration released the Blueprint for Addressing the Maternal Health Crisis. The Blueprint outlines priorities and actions across federal agencies to improve access to coverage and care, expand and enhance data collection and research, grow, and diversify the perinatal workforce, strengthen social and economic support, and increase trainings and incentives to support women being active participants in their care before, during and after pregnancy. Several of these proposals are included in the MOMNIBUS, a federal legislative package sponsored by the Congressional Black Maternal Health Caucus. Federal agencies also have announced plans and actions to support the Blueprint, including the Centers for Medicare & Medicaid Services (CMS), which released a maternity care action plan in July 2022; the Health Resources and Services Administration (HRSA), which has committed $350 million to states to strengthen maternal and child health, and the Office of the Assistant Secretary for Health (OASH), which invested $8.5 million in initiatives designed to reduce pregnancy-related deaths and complications that disproportionately impact people of color and those living in rural areas.
Recent federal legislation has expanded access to and helped stabilize Medicaid coverage during the postpartum period. Medicaid covers almost half of births nationally. However, historically, many pregnant women lost coverage at the end of a 60-day postpartum coverage period because eligibility levels are lower for parents than pregnant women in many states, particularly those that have not implemented the Affordable Care Act (ACA) Medicaid expansion. The American Rescue Plan Act (ARPA) of 2021 provided states a new option for five years, beginning April 1, 2022, to extend postpartum coverage to a full year. As of October 27, 2022, 27 states, including DC, had implemented a 12-month postpartum coverage extension, and an additional seven states were planning to implement the extension. KFF analysis suggests that the coverage extension could prevent hundreds of thousands of enrollees from losing coverage in the months after delivery. In addition, at the start of the pandemic, Congress enacted the Families First Coronavirus Response Act (FFCRA), which included a requirement that Medicaid programs keep people continuously enrolled through the end of the month in which the COVID-19 PHE ends in exchange for enhanced federal funding. This provision has prevented coverage gaps or losses that otherwise might have occurred during the postpartum period due to changes in eligibility and/or administrative challenges associated with maintaining coverage. However, coverage losses may occur after states resume redeterminations of eligibility when the PHE ends. Additional actions may also help to reduce disparities, including adoption of the ACA Medicaid expansion in the 12 remaining states that have not yet expanded, as nearly six in ten adults in the coverage gap in these states are adults of color. Further, Medicaid expansion promotes continuity of coverage in the prenatal and postpartum periods. The Biden Administration Blueprint encourages states to take-up the ARPA postpartum coverage option and urges Congress to close the Medicaid coverage gap and require all states to provide 12 months postpartum Medicaid and CHIP coverage.
Implementation of evidence-based best practices may help to improve maternal and infant health outcomes. As part of its maternity care action plan, CMS has outlined a proposal for a “Birthing-Friendly” hospital designation that would provide public information on hospitals that have implemented best practices in areas of health care quality, safety, and equity for pregnant and postpartum patients. Moreover, in 2022, CMS has launched a new effort within its maternal and infant health initiative to reduce low-risk Cesarean births to improve infant and maternal health. This program is centered around a learning collaborative that outlines approaches Medicaid and CHIP agencies can put in place to reduce low-risk cesarean deliveries and works directly with states to implement evidence-based best practices in their state.
Recent actions have enhanced access to data on maternal and infant health outcomes and disparities. For example, the Centers for Disease Control and Prevention (CDC) conducts national pregnancy-related mortality surveillance and regularly releases findings as a source of information around the risk factors and causes of pregnancy-related deaths. The CDC also developed Levels of Care Assessment Tool (LOCATe) to assist states by standardizing their assessments of levels of maternal and neonatal care and promotes the Hear Her campaign to raise awareness of urgent maternal warning signs during and after pregnancy. In addition, the CDC supports state efforts to prevent maternal deaths through several efforts including the Enhancing Reviews and Surveillance to Eliminate Maternal Mortality (ERASE MM) program and perinatal quality collaboratives (PQCs), which aide in increasing understanding of the drivers of pregnancy related mortality and identify health care processes that contribute to improved outcomes for mothers and infants to reduce racial disparities and geographic disparities. Maternal mortality review committees in several states are comprised of clinicians, community members, researchers, and other experts to review all deaths within one year of pregnancy, and identify causes, drivers, and opportunities for quality improvement. Data collection by these committees has been particularly important in understanding that a large share of deaths are preventable as well as identifying the significant portion of deaths that occur after delivery and encouraging efforts to strengthen care in the postpartum period. Moreover, there are several research and data collection initiatives directed by CDC to monitor sudden unexpected infant deaths, reduce infant mortality and build epidemiological support at the state and local level to improve maternal and child health programs.
A variety of efforts are underway to increase workforce diversity and expand access to doula and other services to improve maternal and infant health outcomes and reduce disparities. Studies have shown that a more diverse healthcare workforce and the use of doulas may improve birth outcomes. The percent of maternal health physicians and registered nurses that are Hispanic or Black is lower than their share of the female population of childbearing age. The Biden Administration’s Blueprint includes efforts by HRSA to develop a maternal care pipeline to provide scholarships to students from underrepresented communities in health professions and nursing schools to grow and diversify the maternal care workforce. The use of doula services is another approach to increase diversity and expand the maternal health workforce. Doulas are trained non-clinicians who assist a pregnant person before, during and/or after childbirth by providing physical assistance, labor coaching, emotional support, and postpartum care. Pregnant women who receive doula support have been found to have shorter labors and lower C-sections rates, fewer birth complications, are more likely to initiate breastfeeding, and their infants are less likely to have low birth weights. The Biden Administration’s Blueprint includes a FY2023 budget request for $20 million to grow and diversify the doula workforce. Additionally, in recent years there has been growing interest in expanding coverage of doula services through Medicaid. Federal legislation has been introduced to expand coverage of doula services through Medicaid, and some states are taking steps to include coverage through their state programs. State efforts to date have had mixed success, in part because of challenges with certification requirements and low reimbursement levels. In 2022, there were at least 17 states considering, planning, or implementing coverage of doula services through Medicaid reimbursements. Some states are also implementing or expanding coverage for other services focused on improving maternal and infant health including home visiting programs to teach positive parenting and other skills; postpartum services provided by lactation counselor and consultants, public health nurses, and medical caseworkers; as well as targeted case management and other programs to meet needs of pregnant and postpartum individuals with substance use disorders.
States, providers and health systems, foundations, and communities also are engaged in a broad range of efforts to advance maternal and child health and reduce disparities. Several states have developed plans and initiatives to address disparities in maternal and infant outcomes. For example, New Jersey launched the Nurture NJ Strategic Plan to outline challenges, action areas, and recommendation to achieve equity for all women with a focus on dismantling structural racism and addressing social determinants of health. In addition, many state Medicaid programs have implemented policies, programs, and initiatives to improve maternity care and outcomes and , including expanding eligibility for people during and after pregnancy, conducting outreach and education to enrollees and providers, expanding coverage for benefits such as doula care, home visits, and substance use disorder and mental health treatment, and using new payment, delivery, and performance measurement approaches. Also, five states reported including Performance Improvement Projects (PIPS) for their Medicaid services that focused specifically on reducing disparities related to maternal and child health in Fiscal Year 2022, including Illinois, Michigan, Minnesota, Nevada, and Texas. California is in the process of implementing provisions from legislation passed in recent years requiring implicit bias training for all perinatal health workers, as well as elements of the California MOMNIBUS, which directs the state to invest in improved data analysis, streamlining administrative procedures within the welfare program for pregnant people, and broadening the midwifery workforce. Northwell Health, the largest healthcare provider in New York, recently launched a Center for Maternal Health to address pregnancy related health risks facing Black women by seeking to address issues within healthcare and in the community that arise before, during, and after pregnancy. The Changing Woman Initiative is a Native American midwifery organization in New Mexico providing culturally centered care to address maternal health disparities, high rates of gestational diabetes, and low birth weight deliveries among Indigenous women.
A range of organizations are advocating for more interventions and supports to address maternal mental health and substance use issues, major causes of pregnancy-related mortality and morbidity. The field of maternal mental health and substance use encompasses a large range of conditions that affect the health of parents and their infants. Some studies have found higher rates of postpartum depression among some pregnant and postpartum women of color, but many mental health conditions are undiagnosed and untreated due to stigma and poor access to treatment. These issues also limit access to services for pregnant and postpartum people suffering from substance use disorders. Community-based and provider organizations are calling for a number of policy and structural changes to address these large challenges, including broader insurance coverage for behavioral health care, higher reimbursement for existing treatment services, greater education and awareness about screening for mental health and substance use conditions among health care providers and childbearing people. Federal initiatives in this area include CMS’ Maternal Opioid Misuse (MOM) Model, a grant program for states to better integrate care for mothers and infants exposed to opioids, and state-level learning communities on mental health, supported by the Health Resources and Services Administration (HRSA) .
At the same time many efforts are focused on improving maternal and infant health and reducing disparities, the recent overturning of Roe v. Wade may contribute to widening disparities in maternal and infant health, People of color are likely to be disproportionately affected by state actions to fully prohibit or implement extensive restrictions on abortions as they are more likely to seek abortions and more likely to face structural barriers that will make it more difficult to travel out of state for an abortion, including more limited access to health care and fewer financial and transportation resources. Increased barriers to abortion for people of color may widen the already existing large disparities in maternal and infant health, have negative economic consequences for families, and increase risk of criminalization for pregnant people of color.
Looking Ahead
Overall, these data show that racial disparities in maternal and infant health persist. Improving maternal and infant health is key for preventing unnecessary illness and death and advancing overall population health. Healthy People 2030, which provides 10-year national health objectives, identifies the prevention of pregnancy complications and maternal deaths and improvement of women’s health before, during, and after pregnancy as a public health goal. The COVID-19 pandemic further highlights the urgency and importance of addressing disparities in health more broadly and increased attention to disparities in maternal and infant health specifically. Moreover, the overturning of Roe v. Wade may contribute to worsening disparities in maternal and infant health, further amplifying the importance of attention to these areas.
The increased awareness and attention to maternal and infant health have contributed to a rise in efforts and resources focused on improving health outcomes in these areas and reducing disparities. These include efforts to expand access to coverage and care, increase access to a broader array of services and providers that support maternal and infant health, diversity the health care workforce, and enhance data collection and reporting. However, addressing social and economic factors that contribute to poorer health outcomes and disparities will also be important. Moreover, the persistence of disparities in maternal health across income and education levels, points to the importance of addressing the roles of racism and discrimination within and beyond the health care system as part of efforts to improve health and advance equity.
Here’s your weekly update with everything you need to know on the COVID situation in B.C. and around the world.iStock/Getty Images Plus
Article content
Here’s your update with everything you need to know about the COVID situation in B.C. and around the world for the week of Dec. 22-28. This page will be updated with the latest COVID news and related research developments daily throughout the week, so be sure to check back often.
Advertisement 2
This advertisement has not loaded yet, but your article continues below.
Article content
You can also get the latest COVID-19 news delivered to your inbox weeknights at 7 p.m. by subscribing to our newsletter here.
Start your day with a roundup of B.C.-focused news and opinion delivered straight to your inbox at 7 a.m., Monday to Friday.
By clicking on the sign up button you consent to receive the above newsletter from Postmedia Network Inc. You may unsubscribe any time by clicking on the unsubscribe link at the bottom of our emails or any newsletter. Postmedia Network Inc. | 365 Bloor Street East, Toronto, Ontario, M4W 3L4 | 416-383-2300
Thanks for signing up!
A welcome email is on its way. If you don’t see it, please check your junk folder.
The next issue of Sunrise presented by Vancouver Sun will soon be in your inbox.
We encountered an issue signing you up. Please try again
Article content
Here are the latest weekly B.C. figures given on Dec. 22:
• Hospitalized cases: 349 (down 25) • Intensive care: 35 (up four) • New cases: 609 over seven days ending Dec. 17 (down 50) • Total number of confirmed cases: 391,897 • Total deaths over seven days ending Dec. 17: 22 (total 4,806)
A weekly COVID update from the B.C. Centre for Disease Control revealed 22 deaths of people who died within 30 days of a positive COVID test as of Dec. 17, a drop of five from the previous week.
That number is preliminary, however, and will be updated in later reports as more data comes in.
Advertisement 3
This advertisement has not loaded yet, but your article continues below.
Article content
There were 349 people in hospital who tested positive for the virus, with 35 of those in intensive care, as of Thursday.
Three out of 10 Canadians say they wear masks in public: Study
Three out of 10 Canadians say they mask-up in public, according to a new Angus Reid Institute study.
It says a large group of unmasked Canadians say they wouldn’t like the government to force them to take a more cautionary approach.
Half of Canadians are in favour of re-implementing mask mandates if cases of COVID-19 go up this winter.
Thirty-one per cent of people in the study say they wear a mask more than half of the time in public.
Read the full story here.
Health Canada monitoring massive outbreak ‘starting to rip through’ China
Health Canada says it’s monitoring the growing wave of COVID-19 cases in China, which experts are warning could kill a million people in the next few months, as the country allows the virus free rein.
Advertisement 4
This advertisement has not loaded yet, but your article continues below.
Article content
China has done a dramatic U-turn in recent weeks, ending its zero-COVID policy that required regular COVID tests, mandatory quarantine and sweeping, restrictive lockdowns to control the virus.
Dr. Isaac Bogoch, an infectious disease physician at Toronto’s University Health Network, said ending the zero-COVID policy, especially in a population with lower vaccine rates, will mean a wave of new infections.
“They don’t have the same degree of community-level protection that other parts of the world have, either through vaccination, through recovery from infection or from both,” he said. “What we’re seeing obviously, very sadly, is that, you know, the virus is starting to rip through populations.”
Read the full story here.
Advertisement 5
This advertisement has not loaded yet, but your article continues below.
Article content
— The Canadian Press
China hospital data absent from WHO’s latest COVID reports, raising concern
The World Health Organization has received no data from China on new COVID-19 hospitalisations since Beijing lifted its zero-COVID policy, prompting some health experts to question whether it might be hiding information on the extent of its outbreak.
However, the WHO has said gaps in data might be due to Chinese authorities simply struggling to tally cases.
WHO weekly reports showed rising hospitalisations for COVID-19 in China running up to Beijing’s Dec. 7 decision to ease restrictions on movement that were meant to stamp out any transmission of the virus but which prompted extraordinary public protests and hobbled the world’s second largest economy.
Advertisement 6
This advertisement has not loaded yet, but your article continues below.
Article content
They peaked at 28,859 through to Dec. 4, according to a WHO graph, the highest reported figure in China since the virus first emerged three years ago, but figures have been absent in the last two reports.
Regular exercise protects against fatal COVID, study shows
Men and women who worked out at least 30 minutes most days were about four times more likely to survive COVID-19 than inactive people, according to an eye-opening study of exercise and coronavirus outcomes among almost 200,000 adults in Southern California.
The study found that exercise, in almost any amount, reduced people’s risks for a severe coronavirus infection. Even people who worked out for as little as 11 minutes a week — yes, a week — experienced lower risks of hospitalization or death from covid than those who moved about less.
Advertisement 7
This advertisement has not loaded yet, but your article continues below.
Article content
“It turns out exercise is even more powerful than we thought” at protecting people from severe covid, said Robert Sallis, a clinical professor at Kaiser Permanente Bernard J. Tyson School of Medicine in Los Angeles and senior author of the new study.
The findings add to mounting evidence that any amount of exercise helps lower the ferocity of coronavirus infections, a message with particular relevance now, as holiday travel and gatherings ramp up and COVID cases continue to rise.
Read the full story here.
— The Washington Post
Immunity debt is not a myth: Why it seems like everybody is sick right now
Although Canada has never maintained a running tally of seasonal illnesses, it’s clear that the country is being absolutely hammered by a tidal wave of flu and respiratory viruses right now.
Advertisement 8
This advertisement has not loaded yet, but your article continues below.
Article content
Children’s hospitals have been overwhelmed since Halloween with what one Montreal physician has described as an “explosive” flu season. The country’s critical shortage of childhood cold medication also continues apace, with Health Canada now saying the backlog won’t fully clear until sometime in 2023.
There is compelling evidence that much of this sickness is a side effect of COVID restrictions — although there remain members of the medical community who are resolutely claiming otherwise.
The basic idea is that social distancing, masking and school closures not only slowed the circulation of COVID-19, but also curbed the usual spread of illnesses such as the flu, respiratory syncytial virus (RSV) and common cold. And now, with civil society reopened, all these seasonal viruses are playing a vicious game of catchup.
Advertisement 9
This advertisement has not loaded yet, but your article continues below.
Article content
Read the full story here.
— Tristin Hopper
China’s COVID wave spurs fears that dangerous new variant could emerge
The tsunami of COVID-19 that’s taking hold across China is spurring concern that a dangerous new variant could emerge for the first time in more than a year, just as genetic sequencing to catch such a threat is dwindling.
The situation in China is unique because of the path it’s followed throughout the pandemic. While almost every other part of the world has battled infections and embraced vaccinations with potent mRNA shots to varying degrees, China largely sidestepped both. The result is a population with low levels of immunity facing a wave of disease caused by the most contagious strain of the virus yet to circulate.
Advertisement 10
This advertisement has not loaded yet, but your article continues below.
Article content
The expected surge of infections and deaths are taking hold in China within a black box since the government is no longer releasing detailed COVID data. The rise has medical experts and political leaders in the U.S. and elsewhere worried about another round of disease caused by the mutating virus. Meanwhile, the number of cases sequenced globally each month to find those changes has plunged.
“There will certainly be more Omicron subvariants developing in China in the coming days, weeks and months, but what the world must anticipate in order to recognize it early and take rapid action is a completely new variant of concern,” said Daniel Lucey, a fellow at the Infectious Diseases Society of America and professor at Dartmouth University’s Geisel School of Medicine. “It could be more contagious, more deadly, or evade drugs, vaccines and detection from existing diagnostics.”
Advertisement 11
This advertisement has not loaded yet, but your article continues below.
Article content
Read the full story here.
— Bloomberg News
What are B.C.’s current public health measures?
MASKS: Masks are not required in public indoor settings though individual businesses and event organizers can choose to require them.
Masks are also encouraged but not required on board public transit and B.C. Ferries, though they are still required in federally regulated travel spaces such as trains, airports and airplanes, and in health care settings.
GATHERINGS AND EVENTS: There are currently no restrictions on gatherings and events such as personal gatherings, weddings, funerals, worship services, exercise and fitness activities, and swimming pools.
There are also no restrictions or capacity limits on restaurants, pubs, bars and nightclubs; and no restrictions on sport activities.
Advertisement 12
This advertisement has not loaded yet, but your article continues below.
Article content
CARE HOMES: There are no capacity restrictions on visitors to long-term care and seniors’ assisted living facilities, however, visitors must show proof of vaccination before visiting. Exemptions are available for children under the age of 12, those with a medical exemption, and visitors attending for compassionate visits related to end-of-life.
Visitors to seniors’ homes are also required to take a rapid antigen test before visiting the facility or be tested on arrival. Exemptions to testing are available for those attending for compassionate visits or end-of-life care.
How do I get vaccinated in B.C.?
Everyone who is living in B.C. and eligible for a vaccine can receive one by following these steps:
• Get registered online at gov.bc.ca/getvaccinated to book an appointment in your community. • Or, if you prefer, you can get registered and then visit a drop-in clinic in your health authority. • The system will alert you when it is time to go for your second dose. • The same system will also alert you when it is time for your booster dose.
Advertisement 13
This advertisement has not loaded yet, but your article continues below.
Article content
We apologize, but this video has failed to load.
Where can I get a COVID-19 test?
TESTING CENTRES: B.C.’s COVID-19 test collection centres are currently only testing those with symptoms who are hospitalized, pregnant, considered high risk or live/work with those who are high risk. You can find a testing centre using the B.C. Centre for Disease Control’s testing centre map.
If you have mild symptoms, you do not need a test and should stay home until your fever is gone. Those without symptoms do not need a test.
TAKE-HOME RAPID ANTIGEN TESTS: Eligible British Columbians over the age of 18 with a personal health number can visit a pharmacy to receive a free take-home test kit containing five COVID-19 rapid antigen tests.
We apologize, but this video has failed to load.
More news, fewer ads: Our in-depth journalism is possible thanks to the support of our subscribers. For just $3.50 per week, you can get unlimited, ad-lite access to The Vancouver Sun, The Province, National Post and 13 other Canadian news sites. Support us by subscribing today: The Vancouver Sun | The Province.
B.C. government continues the pandemic wage top-up for care home workers
The viral immunity debate has no simple answer — but masks make a difference, says researcher
UBC researchers discover compound that could halt colds, COVID
Holiday parties are back as British Columbians tap a need to be together
Share this article in your social network
Advertisement 1
This advertisement has not loaded yet, but your article continues below.
Nowexhibit anchor Al Roker is sharing an update on his health immediately after returning property from a thirty day period-extensive hospitalization for blood clots.
The 68-year-aged weatherman shared on Instagram that he’s “so thankful to be perfectly enough” to rejoice Xmas with his spouse and children while recovering at home.
Roker does not strategy to return to Nowadays just however as he’s focused on regaining his energy.
Today present weatherman Al Roker is back on the mend—and absolutely embracing the Xmas spirit with his loved ones!
The 68-calendar year-aged a short while ago gave an update on his well being following his hospitalization for blood clots very last thirty day period, sharing a sequence of photos on Instagram of his spouse and children decorating and posing in entrance of the Xmas tree—including his wife Deborah Roberts, along with their children Leila and Nick. “So thankful to be well ample to adorn the Roker Household #christmastree,” he wrote in the caption.
Fans, of training course, manufactured absolutely sure to flood the remarks with messages of assist for Roker. “So content you are home and undertaking better…Enjoy the holidays with your household ❤️,” one user wrote.
There ended up loads of get-properly and holiday wishes for the Right now anchor, also. “Miss you Al on Currently. Praying for a entire recovery. ❤️❤️❤️,” just one supporter commented, although one more wrote, “So joyful you are on the mend Al. Merry Christmas and looking forward to viewing you back again at These days in the new calendar year!! Slow and regular wins the race!!”
Before this thirty day period, Roker returned property soon after a four-week-prolonged remain in the healthcare facility. He was initial hospitalized in late November for blood clots in his legs and lungs and was unveiled around Thanksgiving in time to celebrate with his family—only to be “rushed” back again to the healthcare facility in 24 several hours of his launch because of to difficulties. Sadly, this forced the anchor to overlook Macy’s Thanksgiving Thanksgiving Working day Parade as effectively as the Rockefeller Middle Christmas tree lighting.
Luckily, he was capable to return residence on December 8 just in time to equipment up for Xmas, having to Instagram to share the good news.
“Home! So exceptionally grateful to family members, good friends, health-related people, @todayshow family, and all your views and prayers,” Roker wrote at the time, along with snaps of himself in his family’s kitchen, including types jointly with his spouse and daughter.
Of program, there’s been no shortage of aid for Roker from his enthusiasts and These days colleagues on his street to recovery. The Nowadays forged and crew—including co-hosts Hoda Kotb and Savannah Guthrie—even made certain to carry Roker some festive vacation cheer to his home final 7 days, surprising the weather conditions anchor by accumulating on his doorstep to sing Christmas carols.
Roker later on created sure to categorical his gratitude for the emotional shock in an Instagram article. “Words can not convey how a great deal I adore my @todayshow loved ones for coming above to do a very little caroling like a exclusive rendition of ‘I’ll Be Household For #Christmas,’” he wrote.
Roker also appeared on Nowadays by way of a digital video clip simply call very last 7 days to share an update on his overall health with his colleagues and viewers, admitting that his recent well being struggles have been a complicated time for him—but that the outpouring of assist and adore has assisted bolster his spirit while he’s on the mend.
“Listen, it’s been a difficult slog. I’m not heading to deny this,” he claimed. “It is been the hardest 1 yet…It gives you a profound sense of gratitude for this outpouring of prayers and thanks. I’m a pretty fortunate particular person.”
As for when he will return to Right now, Roker shared that he’s not ready to resume his obligations at the NBC morning display pretty nevertheless as he’s still concentrated on regaining his strength.
“You drop a specified quantity of muscle mass for just about every 7 days you’re in the hospital, and I was in the hospital for 4 months,” he discussed. “It’s just a specified amount of money of weak spot. I’m carrying out actual physical therapy each individual working day, occupational treatment. I have obtained to just get my toughness back again.”
We’re hoping to see Roker back again on the Now display very soon—but in the meantime, we’re wishing him a speedy restoration!
Editorial Assistant
Hannah (she/her) is an editorial assistant for Excellent Housekeeping, the place she writes well being information and assists with social media tactic throughout platforms including Instagram, TikTok, Facebook and Twitter. Beforehand GH’s editorial fellow, she earned her bachelor’s degree in creating seminars and psychology from Johns Hopkins College. When she is not endlessly scrolling as a result of social media, you can normally uncover her clicking absent driving a digicam, fangirling over Taylor Swift or trying out new meals places in New York City.
COLUMBUS, Ohio — With relatives gatherings proper all-around the corner for Xmas and New Calendar year celebrations, Ohio overall health officers gave a statewide update on respiratory viruses throughout a push conference Wednesday morning.
Amid the biggest messages:
Get vaccinated in opposition to flu and COVID
Take into consideration carrying a mask indoors in public
“I assume shifting ahead, there are several scenarios where by persons really should decide, definitely, to don a substantial-excellent mask,” mentioned Dr. Joe Gastaldo, Clinical Director of Infectious Illnesses for OhioHealth. “Specifically, pay out focus to what is going about in your area. The CDC nevertheless created a county-by-county COVID neighborhood stage. If you live in a county and you listen to of an advisory to have on a mask indoors in general public irrespective of your vaccination standing, you should be adhering to that suggestion if it arrives to that.”
We streamed the complete press meeting, which you can view in full beneath:
SUBSCRIBE : Get the day’s leading headlines despatched to your inbox each and every weekday morning with the no cost 3News to GO! publication
Dr. Gastaldo stressed masking for those who have at-chance situations or are considered immunocompromised.
Ohio Division of Overall health Director Dr. Bruce Vanderhoff, who led the push meeting, also outlined quite a few updates with regards to the distribute of RSV, flu and COVID.
“These viruses all have the skill to lead to major ailment – and of class, massive gatherings and indoor options only improve that possibility,” he mentioned.
Where does Ohio stand ideal now with each individual style of sickness? Here is how Dr. Vanderhoff broke down the details…

RSV
“Thankfully, more than the previous handful of weeks, we’ve observed RSV begin to decrease each here in Ohio and nationally,” Dr. Vanderhoff described. “In simple fact, the CDC stories that RSV hospitalizations have fallen by two-thirds more than the past thirty day period. The rate stays high, but it’s not in the vicinity of the peak we skilled in mid-November. However, RSV is not absent and we have to have to be aware that it carries on to pose a risk.”

FLU
“Flu begun early and elevated pretty swiftly to a single of the maximum peaks that we’ve seen in new yrs,” Vanderhoff claimed. “As with RSV, though, we’re relieved that past 7 days both of those the CDC and our personal statewide surveillance exposed a fall in influenza-similar hospitalizations. When that slight drop is welcome, primarily based on earlier practical experience it would seem not likely that influenza circumstances will now drop speedily towards a reduced amount. Far more very likely, we’re seeking at a problem where we could see sustained substantial ranges with peaks and valleys for a amount of months. That type of sustained large plateau – perhaps with compact peaks and valleys – is rather usual of influenza.”

COVID
Dr. Vanderhoff noted that COVID-19 situations have been climbing in recent weeks.
“Despite the dominance of the BQ.1 subvariant of omicron as properly as its descendants, which look to have a significant capability to evade antibody-primarily based immunity, these variants don’t seem to be to be obtaining a great deal good results in evading the much more resilient B and T mobile immunity stimulated by our COVID-19 vaccines,” he said. “B and T mobile immunity, as you will recall, is the vital to protecting most of us from the kind of significant health issues that leads to COVID hospitalizations.”
For further context, Dr. Vanderhoff explained that Ohio was dealing with everywhere from 2,000 to 3,000 men and women hospitalized from COVID every single 7 days in December of 2020 and 2021 .This year, individuals numbers are approximately 600 for each 7 days.
“We’re in a far better location than we have been in the past two several years. We have additional applications at our disposal – specially when it comes to COVID-19.”
Dr. Sumita Khatri of the Cleveland Clinic explained to 3Information previous 7 days that the flu is “coming again with a vengeance.”
“Unless we all get vaccinated for the flu, our pandemic will turn into that tripledemic which we’re previously seeing with RSV, flu, and COVID,” she said.
Even though it normally takes two weeks for your system to construct protection after acquiring a flu shot, health and fitness gurus say you can nonetheless get just one now to have some protection before collecting with loved types and friends for the holiday getaway season.
Editor’s observe: Movie in the player earlier mentioned was initially released in a earlier story on Dec. 14, 2022.
Want to be amid the initially to know the most crucial area and national news? You can obtain the cost-free WKYC app and get the most current updates suitable on your cellular phone: Android, Apple.