The Biden administration’s selection to stop the COVID-19 community health and fitness emergency in May perhaps will institute sweeping improvements throughout the health treatment method that go far outside of many individuals owning to shell out far more for COVID checks.
In response to the pandemic, the federal authorities in 2020 suspended numerous of its regulations on how treatment is delivered. That reworked effectively each individual corner of American wellness care — from hospitals and nursing homes to public wellness and treatment method for folks recovering from dependancy.
Now, as the governing administration prepares to reverse some of individuals ways, here’s a glimpse at means clients will be afflicted:
Training guidelines for nursing residence employees get stricter
The close of the unexpected emergency usually means nursing households will have to meet increased requirements for teaching workers.
Advocates for nursing home residents are keen to see the old, more durable coaching needs reinstated, but the market states that go could worsen staffing shortages plaguing amenities nationwide.
In the early times of the pandemic, to help nursing properties function beneath the virus’s onslaught, the federal governing administration relaxed education needs. The Facilities for Medicare & Medicaid Solutions instituted a national plan declaring nursing houses needn’t comply with regulations requiring nurse aides to undergo at the very least 75 hrs of condition-approved schooling. Generally, a nursing property couldn’t make use of aides for additional than four months except they met people prerequisites.
Final 12 months, CMS decided the peaceful training guidelines would no lengthier utilize nationwide, but states and amenities could talk to for permission to be held to the reduced criteria. As of March, 17 states had these kinds of exemptions, according to CMS — Ga, Indiana, Louisiana, Maryland, Massachusetts, Minnesota, Mississippi, New Jersey, New York, Oklahoma, Pennsylvania, Rhode Island, South Carolina, Tennessee, Texas, Vermont, and Washington — as did 356 individual nursing homes in Arizona, California, Delaware, Florida, Illinois, Iowa, Kansas, Kentucky, Michigan, Nebraska, New Hampshire, North Carolina, Ohio, Oregon, Virginia, Wisconsin, and Washington, D.C.
Nurse aides frequently provide the most immediate and labor-intensive care for inhabitants, which includes bathing and other hygiene-linked jobs, feeding, monitoring crucial indications, and trying to keep rooms thoroughly clean. Investigate has revealed that nursing households with staffing instability keep a reduce top quality of treatment.
Advocates for nursing household residents are delighted the schooling exceptions will close but worry that the top quality of care could nevertheless deteriorate. Which is for the reason that CMS has signaled that, right after the looser criteria expire, some of the hrs that nurse aides logged all through the pandemic could depend toward their 75 hrs of expected schooling. On-the-occupation experience, on the other hand, is not always a audio substitute for the training workers missed, advocates argue.
Adequate education of aides is very important so “they know what they are doing right before they present care, for their personal superior as perfectly as for the residents,” explained Toby Edelman, a senior coverage attorney for the Middle for Medicare Advocacy.
The American Health Treatment Association, the major nursing house lobbying team, produced a December survey finding that roughly 4 in 5 amenities have been working with reasonable to superior amounts of staff members shortages.
Cure threatened for folks recovering from habit
A looming rollback of broader entry to buprenorphine, an crucial medicine for men and women in restoration from opioid addiction, is alarming sufferers and medical professionals.
Through the general public health and fitness emergency, the Drug Enforcement Administration reported providers could prescribe certain managed substances pretty much or over the cell phone with out initially conducting an in-man or woman clinical analysis. A person of these medicine, buprenorphine, is an opioid that can stop debilitating withdrawal signs or symptoms for men and women striving to get well from addiction to other opioids. Analysis has proven utilizing it far more than halves the risk of overdose.
Amid a nationwide epidemic of opioid habit, if the expanded plan for buprenorphine finishes, “countless numbers of persons are heading to die,” claimed Ryan Hampton, an activist who is in restoration.
The DEA in late February proposed polices that would partly roll again the prescribing of managed substances as a result of telemedicine. A clinician could use telemedicine to purchase an preliminary 30-day supply of remedies this kind of as buprenorphine, Ambien, Valium, and Xanax, but clients would have to have an in-particular person evaluation to get a refill.
For another group of medicines, which include Adderall, Ritalin, and oxycodone, the DEA proposal would institute tighter controls. People trying to find those medicines would have to have to see a health practitioner in man or woman for an first prescription.
David Herzberg, a historian of drugs at the College at Buffalo, stated the DEA’s approach reflects a elementary obstacle in building drug policy: conference the wants of persons who depend on a drug that can be abused without having earning that drug far too easily readily available to some others.
The DEA, he added, is “evidently critically wrestling with this trouble.”
Hospitals return to ordinary, to some degree
All through the pandemic, CMS has attempted to restrict challenges that could occur if there weren’t enough wellbeing treatment staff to take care of people — primarily right before there had been COVID vaccines when workers were at greater risk of having sick.
For case in point, CMS permitted hospitals to make broader use of nurse practitioners and medical professional assistants when caring for Medicare individuals. And new physicians not however credentialed to work at a certain clinic — for instance, simply because governing bodies lacked time to conduct their evaluations — could however practice there.
Other alterations through the public overall health emergency had been intended to shore up hospital potential. Crucial entry hospitals, modest hospitals located in rural places, failed to have to comply with federal policies for Medicare stating they ended up minimal to 25 inpatient beds and patients’ stays could not exceed 96 several hours, on normal.
At the time the crisis finishes, those exceptions will vanish.
Hospitals are attempting to persuade federal officials to keep numerous COVID-period insurance policies outside of the emergency or operate with Congress to change the law.
Surveillance of infectious health conditions splinters
The way condition and area general public wellness departments observe the unfold of condition will change immediately after the crisis ends, due to the fact the Section of Well being and Human Expert services will never be ready to call for labs to report COVID testing data.
Without a uniform, federal need, how states and counties track the distribute of the coronavirus will fluctuate. In addition, even though hospitals will nevertheless provide COVID info to the federal govt, they might do so significantly less usually.
Public well being departments are continue to obtaining their arms all around the scope of the adjustments, said Janet Hamilton, govt director of the Council of State and Territorial Epidemiologists.
In some approaches, the conclude of the crisis gives public health officers an possibility to rethink COVID surveillance. In comparison with the pandemic’s early days, when at-property exams had been unavailable and men and women relied intensely on labs to determine irrespective of whether they have been contaminated, screening facts from labs now reveals much less about how the virus is spreading.
Community wellness officials don’t assume “receiving all test success from all lab assessments is likely the correct approach anymore,” Hamilton mentioned. Flu surveillance gives a prospective different model: For influenza, general public wellbeing departments request check final results from a sampling of labs.
“We are nonetheless seeking to get the job done out what is the very best, reliable system. And I will not think we have that nonetheless,” Hamilton explained.
KHN (Kaiser Overall health Information) is a national newsroom that provides in-depth journalism about well being concerns. Collectively with Policy Evaluation and Polling, KHN is a single of the a few big running plans at KFF (Kaiser Spouse and children Foundation). KFF is an endowed nonprofit business delivering details on health issues to the country.
The following announcement is from the Fairfield Chamber of Commerce:
FAIRFIELD, CT — The Fairfield Chamber of Commerce, in partnership with the City of Fairfield and its Section of Group & Economic Development, announce that Totally free Covid Vaccines and Overall health Screenings will now be readily available at the upcoming 2023 Health and fitness and Exercise Expo on March 11th – these services will be furnished by Griffin Medical center.
“It has been three yrs since we past held this party, and we are thrilled to mark its return,” states Beverly Balaz, President of the Fairfield Chamber of Commerce. This yr, the Fairfield Well being and Physical fitness Expo will have one thing for the whole spouse and children to enjoy. Free of charge, and open up to the community, the Expo will aspect 60+ exhibitors additionally exclusive pursuits for younger and aged alike. “We are delighted to be doing work with the Fairfield Chamber of Commerce to host this celebration,” stated Fairfield Community & Economic Improvement Director Mark Barnhart. “It claims to be a pleasurable-loaded working day with wellness-aware activities for the complete family,” Barnhart continued. Parking for the function is no cost.
The two the Chamber and City are proud to host an celebration that encourages a balanced life style knowledge for youthful and outdated, and invites everyone to go to to have enjoyment, view some conditioning demos, and get answers from our company homeowners to determine what is required to remain in shape and healthier … and how to assist our seniors! Regardless of whether people are intrigued in conditioning, or want medical, wellness, or senior providers facts, it is in this article … conveniently all in a person place!
Exhibitor Partial Checklist, like Sponsors:
Superior EyeCare of Connecticut (sponsor) Adventure Park at The Discovery Museum AFC Urgent Treatment Atlas Nutrition & Wellness BEMER Bridgeport Clinic (sponsor) Cardio Kick Studio Collins Professional medical Gear and Accessibility Methods (sponsor) ComForCare Household Care (sponsor) ConnectFairfield (sponsor) Comparion Insurance Company CycleBar Cornerstone Healthcare Instruction Heart Crowe and Associates David Lerner Associates, Inc Dental Associates of Connecticut Docs Urgent Care Fairfield CARES Group Coalition Fairfield Family members Dentistry Fairfield Moms (sponsor) Fairfield College Frontier c/o Initially Phase Internet marketing (sponsor) Granola Bar JFitness Linda Stephens Conditioning Countrywide Healthcare Associates (Cambridge & Ludlow) Nuvance Wellness (sponsor) Oasis Senior Advisors Procedure Hope Pharmanex Senior Dwelling Selections, LLC Southport Chiropractic
StretchLab Fairfield Sturges Ridge of Fairfield (sponsor) United Health care University of Bridgeport (sponsor) Uss Wellness (sponsor) Traveling to Angels Wakeman Boys & Women Club Whip Salon And lots of, many far more!
Celebration data is up to date everyday, so individuals ought to take a look at and look at the Fairfield Chamber Web page and the Chamber’s Facebook Party Webpage, as well as the Town’s “Experience Fairfield” web-site for the most recent exhibitor listings and things to do. Volunteers are also desired all over the day to fulfill and greet attendees.
The Town and Chamber thank their generous sponsors, for all their support, and Collins Health care Products and Accessibility Options as the occasion sponsor.
Shamrock Enjoyable Operate/Sponsored by Seem Runner
Craft Pursuits by the YMCA.
Other Expert services:
Arms-Only CPR & AED Education/Fairfield Fire Office
Prescription Drug Just take-Back again/Fairfield Law enforcement Office
Health and fitness Demos
Convenience Dog/Fairfield University’s “Dakota”
Senior Providers
Digital Fact Dementia Simulation
Hassle-free Absolutely free Parking – Kelley Middle Parking Garage, throughout from the RecPlex
And far more …
For more data regarding this Expo, such as a total list of exhibitors, instructions to the RecPlex and parking, remember to stop by the Fairfield Chamber of Commerce web-site: FairfieldCTChamber.com. Or get in touch with Michele@FairfieldCTChamber.com (203-255-1011).
2023 Fairfield Overall health & Health and fitness Expo
Specifics: Date: Saturday, March 11th (Rain or Shine) Time: 11:00am – 4:00PM
Area: Fairfield University/RecPlex 1073 N. Benson Highway Fairfield, CT 06824
King Charles was questioned about his wife’s wellbeing as he frequented Milton Keynes on Thursday


Queen Consort Camilla was not able to go to a joint outing to Milton Keynes with her husband, King Charles, following screening beneficial for COVID-19 earlier this week.
The King, 74, travelled on your own to celebrate Milton Keynes’ new metropolis status, and shared an update on his wife’s wellness all through a brief walkabout.
Watch: King Charles comes in Milton Keynes to cheers irrespective of protest
Right after meeting local community representatives within Church of Christ the Cornerstone, he stopped to speak to effectively-wisher Tazmin Farrington, who explained later on she requested about Camilla’s wellness and Charles replied: “She’s acquiring greater”.
The Queen Consort was compelled to terminate her engagements this 7 days immediately after contracting the virus.
Buckingham Palace reported in a statement on Monday night: “After struggling the symptoms of a cold, Her Majesty The Queen Consort has tested good for the Covid virus.
“With regret, she has hence cancelled all her general public engagements for this week and sends her honest apologies to individuals who experienced been owing to go to them.”
Protestors have been among the the group
As the King arrived in Milton Keynes, he arrived encounter-to-face with all over 20 protestors from the anti-monarchy group Republic, who held up indications emblazoned with “Not My King”.
Having said that, the monarch seemed unfazed by the demonstration as he was greeted with cheers and chants of “God Help you save The King”.
Charles later achieved volunteers at a food items lender in the suburbs of the town who were not anticipating him.
They were only informed he was browsing an hour right before he arrived and the King laughed when he was told the identity of their VIP visitor experienced been held secret, expressing: “You failed to know why?”
Charles at MK Foods Financial institution
Just one of the themes of the King’s to start with Xmas tackle was the expense of dwelling crisis and the broadcast featured footage of a foods bank.
Louisa Hobbs, operations manager of MK Food stuff Financial institution which supports extra than 5,000 family members across the metropolis, confirmed Charles close to and said his desire was evidently “legitimate” after he explicitly asked for to stop by a foodstuff bank in the metropolis.
Listen: Previous press secretary reveals how she created record for the duration of Prince George’s birth
Make guaranteed you in no way pass up a ROYAL story! Signal up to The Royal Explainer publication to receive your weekly dose of royal functions and other distinctive articles straight to your inbox.
Tara Ghormley has always been an overachiever. She finished at the top of her class in high school, graduated summa cum laude from college and earned top honors in veterinary school. She went on to complete a rigorous training program and build a successful career as a veterinary internal medicine specialist. But in March 2020 she got infected with the SARS-CoV-2 virus—just the 24th case in the small, coastal central California town she lived in at the time, near the site of an early outbreak in the COVID pandemic. “I could have done without being first at this,” she says.
Almost three years after apparently clearing the virus from her body, Ghormley is still suffering. She gets exhausted quickly, her heartbeat suddenly races, and she goes through periods where she can’t concentrate or think clearly. Ghormley and her husband, who have relocated to a Los Angeles suburb, once spent their free time visiting their “happiest place on Earth”—Disneyland—but her health prevented that for more than a year. She still spends most of her days off resting in the dark or going to her many doctors’ appointments. Her early infection and ongoing symptoms make her one of the first people in the country with “long COVID,” a condition where symptoms persist for at least three months after the infection and can last for years. The syndrome is known by medical professionals as postacute sequelae of COVID-19, or PASC.
People with long COVID have symptoms such as pain, extreme fatigue and “brain fog,” or difficulty concentrating or remembering things. As of February 2022, the syndrome was estimated to affect about 16 million adults in the U.S. and had forced between two million and four million Americans out of the workforce, many of whom have yet to return. Long COVID often arises in otherwise healthy young people, and it can follow even a mild initial infection. The risk appears at least slightly higher in people who were hospitalized for COVID and in older adults (who end up in the hospital more often). Women and those at socioeconomic disadvantage also face higher risk, as do people who smoke, are obese, or have any of an array of health conditions, particularly autoimmune disease. Vaccination appears to reduce the danger but does not entirely prevent long COVID.
The most common, persistent and disabling symptoms of long COVID are neurological. Some are easily recognized as brain- or nerve-related: many people experience cognitive dysfunction in the form of difficulty with memory, attention, sleep and mood. Others may seem rooted more in the body than the brain, such as pain and postexertional malaise (PEM), a kind of “energy crash” that people experience after even mild exercise. But those, too, result from nerve dysfunction, often in the autonomic nervous system, which directs our bodies to breathe and digest food and generally runs our organs on autopilot. This so-called dysautonomia can lead to dizziness, a racing heart, high or low blood pressure, and gut disturbances, sometimes leaving people unable to work or even function independently.
The SARS-CoV-2 virus is new, but postviral syndromes are not. Research on other viruses, and on neurological damage from the human immunodeficiency virus (HIV) in particular, is guiding work on long COVID. And the recognition that the syndrome may cause its many effects through the brain and the nervous system is beginning to shape approaches to medical treatment. “I now think of COVID as a neurological disease as much as I think of it as a pulmonary disease, and that’s definitely true in long COVID,” says William Pittman, a physician at UCLA Health in Los Angeles, who treats Ghormley and many similar patients.
Although 16 million U.S. sufferers is a reasonable estimate of the condition’s toll, there are other, more dire assessments. A meta-analysis of 41 studies conducted in 2021 concluded that worldwide, 43 percent of people infected with SARS-CoV-2 may develop long COVID, with about 30 percent—translating to approximately 30 million people—affected in the U.S. Some studies have offered more conservative numbers. A June 2022 survey reported by the U.S. National Center for Health Statistics found that among adults who had had COVID, one in five was experiencing long COVID three months later; the U.K. Office for National Statistics put the estimate at one in 10. Even if only a small share of infections result in long COVID, experts say, they will add up to millions more people affected—and potentially disabled.
Most of the first recognized cases of long COVID were in patients who needed extended respiratory therapy or who had obvious organ damage that caused lasting symptoms. People reporting neurological symptoms were often overlooked or dismissed as traumatized by their initial illness and hospitalization. But as 2020 came to an end, says Helen Lavretsky, a psychiatrist at the University of California, Los Angeles, “we started getting to a place of sorting through what was really going on … and it became very evident at that time that neuropsychiatric symptoms were quite prevalent,” most commonly fatigue, malaise, brain fog, smell loss and post-traumatic stress disorder, as well as cognitive problems and even psychosis.
Ghormley was in her late 30s and relatively healthy when she caught the virus, but she had underlying conditions—including rheumatoid arthritis and asthma—that put her at risk for severe COVID. She spent several days at home, struggling to breathe, and then she went to the hospital, where her blood pressure soared and her blood glucose dropped precipitously. She mostly recovered from this acute phase within a few weeks, but, she says, “I never really got better.”
Soon after coming home from the hospital, Ghormley developed what her husband called “goldfish brain.” “I’d put something down and have no idea where I put it,” she recalls. “It kept happening over and over. I was thinking, ‘This is getting weird.’ My husband said I was not remembering anything. I’d try to talk, and I knew what I wanted to say, but I couldn’t think of the word.”
“Everything fell apart for me,” says Tara Ghormley, who has been struggling with long COVID since 2020. Credit: Ewan Burns
She also experienced tremors, dramatic mood swings and painful hypersensitivity to sounds. “My husband opening a paper bag felt like knives stabbing me in the ear,” she recounts. Any exertion—physical or mental—left her exhausted and in pain. The changes were jarring to Ghormley, who prided herself on her sharp mind. “The thing that bothered me the most was that I was really having trouble thinking, speaking, remembering—trying to complete a task and having no idea what it was. Suddenly I had quite profound neurological deficits. Everything fell apart for me at that time. That was horribly traumatic … it kind of broke me. I didn’t feel like me.”
Roots of Dysfunction
As a veterinary internist, Ghormley says, it’s her job to problem solve when mysterious symptoms arise, including her own. “I was actively trying to find reasons and find what I could do.” She theorized that some of her neurological symptoms might be the result of thrombotic events, blood clots that can cause ministrokes. Several early studies showed that COVID attacks endothelial cells, which line blood vessels. That can lead to clotting and oxygen deprivation in multiple organs, including the brain. Even subtle disruption of endothelial cells in the brain could contribute to cognitive dysfunction.
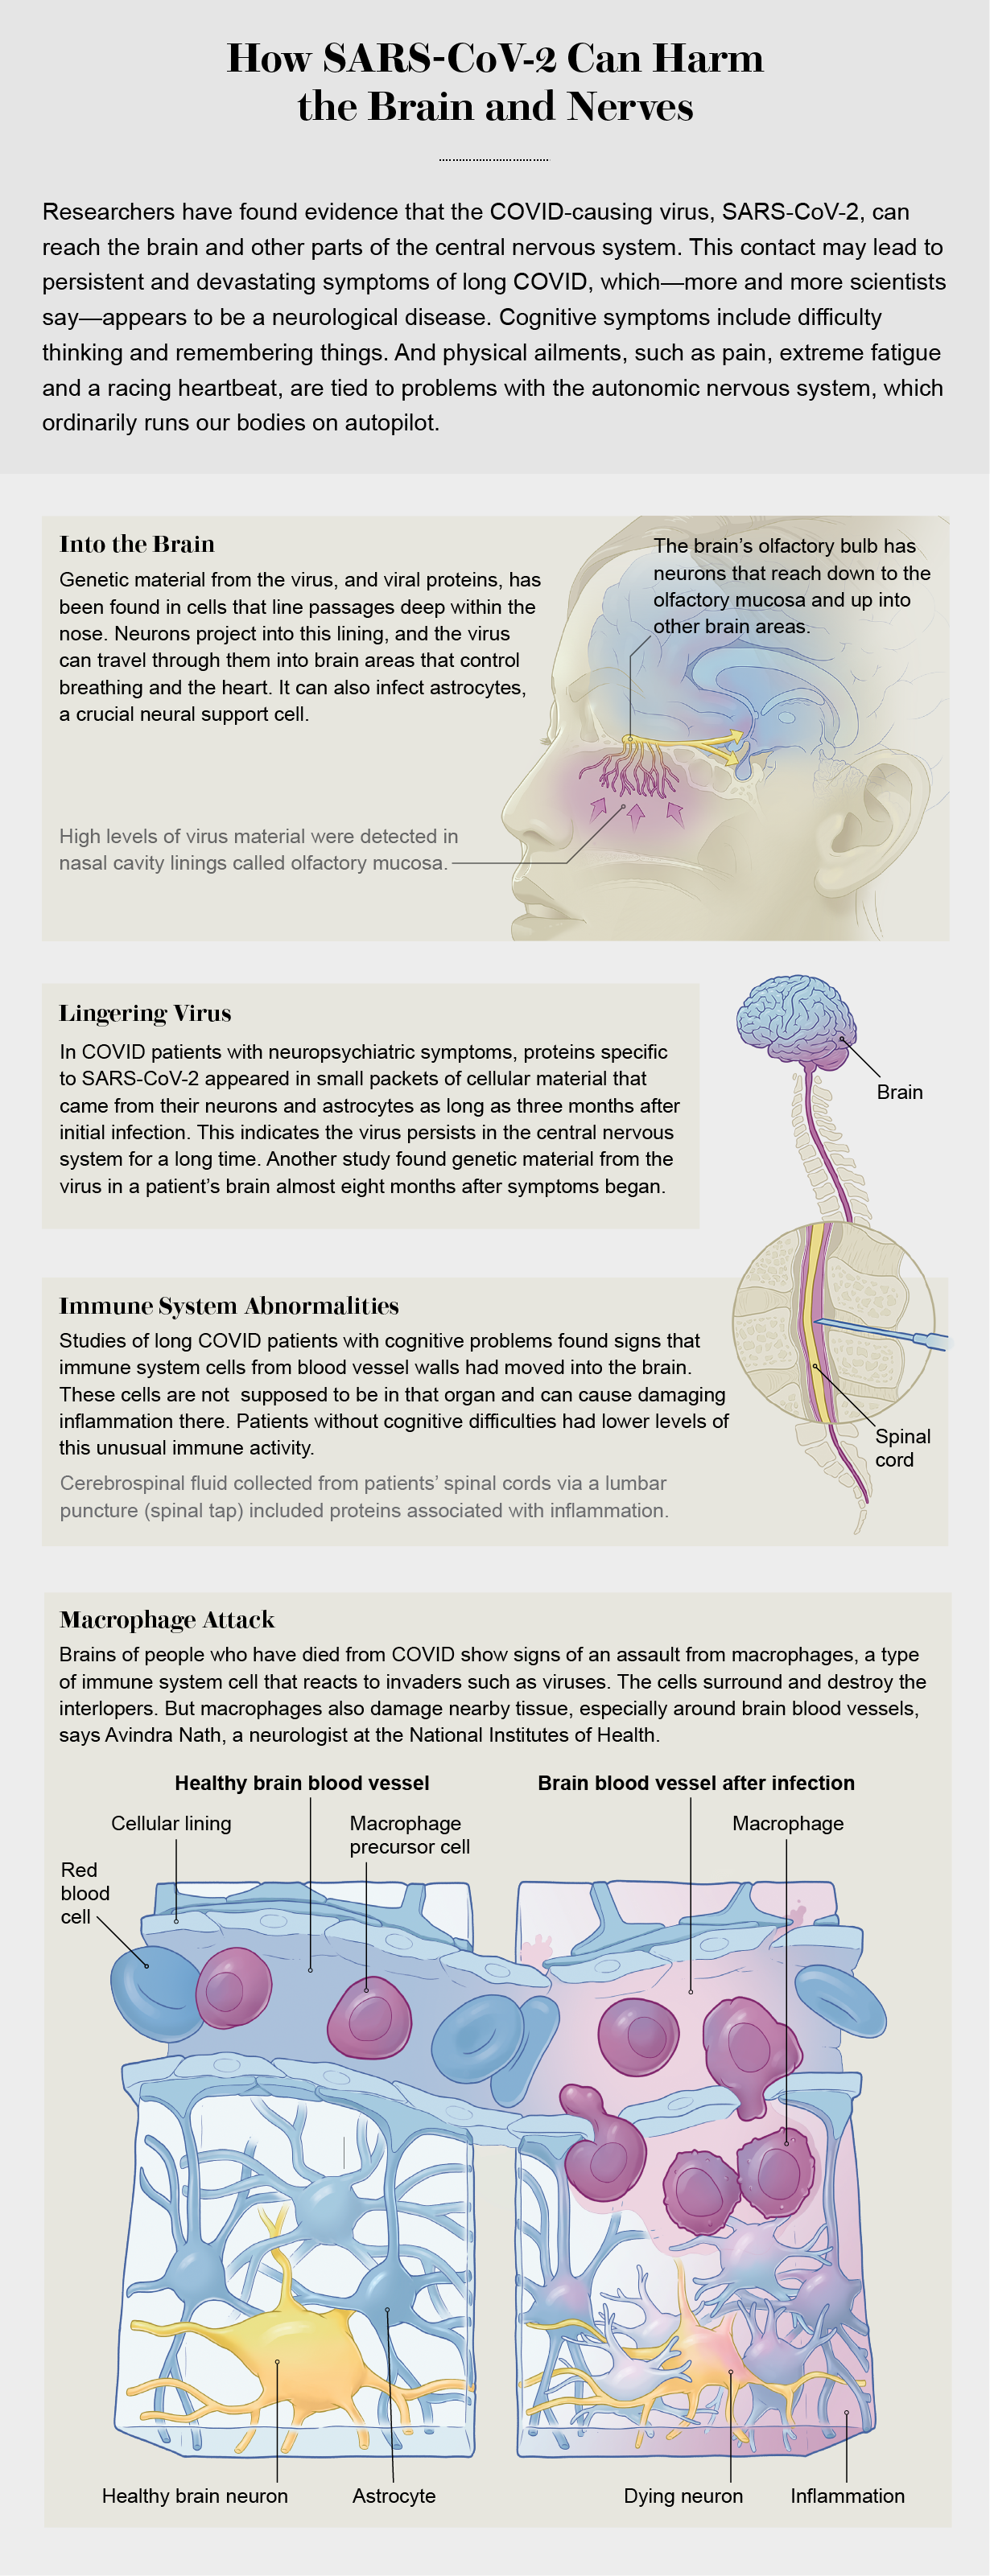
One study found that in people with neurological COVID symptoms, the immune system seems to be activated specifically in the central nervous system, creating inflammation. But brain inflammation is probably not caused by the virus infecting that organ directly. Avindra Nath, who has long studied postviral neurological syndromes at the National Institutes of Health, found something similar in an autopsy study of people who died of COVID. “When you look at the COVID brain, you don’t actually find [huge amounts of virus, but] we found a lot of immune activation,” he says, particularly around blood vessels. The examinations suggested that immune cells called macrophages had been stirred up. “Macrophages are not that precise in their attack,” Nath says. “They come and start chewing things up; they produce all kinds of free radicals, cytokines. It’s almost like blanket bombing—it ends up causing a lot of damage. And they’re very hard to shut down, so they persist for a long time. These are the unwelcome guests” that may be causing persistent inflammation in the brain.
Determining which patients have ongoing inflammation could help inform treatments. Early research identified markers that often are elevated in people with the condition, says Troy Torgerson, an immunologist at the Allen Institute in Seattle. Three cell-signaling molecules—tumor necrosis factor alpha, interleukin 6 and interferon beta—stood out in long COVID patients. But this pattern wasn’t found in absolutely everyone. “We’re trying to sort through long COVID patients and say, ‘This would be a good group to take to trials of an anti-inflammatory drug, whereas this group may need to focus more on rehabilitation,’” Torgerson says. He led a study (currently released as a preprint, without formal scientific review by a journal) in which his team measured proteins from the blood of 55 patients. The researchers found that a subset had persistent inflammation. Among those people, they saw a distinct immune pathway linked to a lasting response to infection. “One subset of patients does appear to have an ongoing response to some virus,” Torgerson says.
Isolated pockets of SARS-CoV-2 or even pieces of viral proteins may remain in the body well after the initial infection and continue to elicit an immune attack. The first solid evidence for “viral persistence” outside the lungs came in 2021 from researchers in Singapore who found viral proteins throughout the gut in five patients who had recovered from COVID as much as six months earlier. A study conducted at the University of California, San Francisco, found evidence for viral particles in the brains of people with long COVID. Scientists collected exosomes, or tiny packets of cellular material, released specifically from cells of the central nervous system. The exosomes contained pieces of viral proteins as well as mitochondrial proteins, which may indicate an immune attack on those vital cellular organelles. Amounts of such suspicious proteins were higher in patients with neuropsychiatric symptoms than in those without them.
The virus could linger in the brain for months, according to research conducted at the NIH and reported in Nature in December 2022. The autopsy study of 44 people who died of COVID found rampant inflammation mainly in the respiratory tract, but viral RNA was detected throughout the body, even in the brain, as long as 230 days after infection. Two other studies, both published last year in the Proceedings of the National Academy of Sciences USA, showed evidence that SARS-CoV-2 may infect astrocytes, a type of neural support cell, gaining entrance via neurons in the skin lining the nose.
Researchers are examining inflammatory signals in patients with long COVID in increasingly fine detail. A small study led by Joanna Hellmuth, a neurologist at U.C.S.F., found that patients with cognitive symptoms had immune-related abnormalities in their cerebrospinal fluid, whereas none of the patients without cognitive symptoms did. At the 2022 meeting of the Society for Neuroscience, Hellmuth reported that she had looked at more specific immune markers in people with cognitive symptoms and found that some patients had an elevated level of VEGF-C, a marker of endothelial dysfunction. Higher VEGF-C concentrations are associated with higher levels of immune cells getting into the brain, she says, and “they’re not doing their normal function of maintaining the blood-brain barrier; they’re distracted and perhaps activated.” Although the studies are small, Hellmuth adds, they reveal “real biological distinctions and inflammation in the brain. This is not a psychological or psychosomatic disorder; this is a neuroimmune disorder.”
What keeps the immune system in attack mode? According to Torgerson, “one option is that you’ve developed autoimmunity,” in which antibodies produced by the immune system to fight the virus also mark a person’s own cells for immune attack. The response to the virus “turns the autoimmunity on, and that doesn’t get better even when the virus goes away,” he says. Several studies have found evidence of autoimmune components called autoantibodies that interact with nerve cells in people with long COVID.
Clues about the inflammatory processes at work could point toward treatments for neurological symptoms. “If it’s a macrophage-mediated inflammatory process … intravenous immunoglobulin could make a difference [to] dampen the macrophages,” Nath says. The treatment, referred to as IVIg, contains a cocktail of proteins and antibodies that can mitigate an overactive immune response.
IVIg can also be used to block autoantibodies. And a therapy called rituximab that targets antibody-producing B cells provides “a time-tested therapy for a lot of autoantibody-mediated syndromes,” Nath says. Another strategy is to use corticosteroids to dampen immune activity altogether, although those drugs can be used for only a limited time. “That’s a sledgehammer approach, and you can see if it makes a difference. At least it gives you an idea that, yes, it’s an immune-mediated phenomenon, and now we need to find a better way to target it,” Nath says.
If the virus does hang around in some form, antiviral medications could potentially clear it, which might help resolve neurological symptoms. That’s the hope of scientists running a clinical trial of Paxlovid, Pfizer’s antiviral drug for acute COVID.
A Chronic Fatigue Connection?
Postviral syndromes have been documented for more than a century, arising after infection with viruses from HIV to the flu. Epstein-Barr virus, which causes mononucleosis, is one of several viruses linked to a condition called myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), which is estimated to affect at least one and a half million people in the U.S. ME/CFS bears striking resemblances to long COVID, with symptoms such as immune system dysregulation, fatigue and cognitive dysfunction. “One of the patterns we see is patients who definitely meet the criteria for ME/CFS. This is something we are seeing and treating all the time” in long COVID patients, Pittman says. ME/CFS can be severe, with some people losing mobility and becoming bedbound.
Credit: Now Medical Studios; Sources: “Neurovascular Injury with Complement Activation and Inflammation in COVID-19,” by Myoung-Hwa Lee et al., in Brain, Vol. 145; July 2022 (blood vessel reference); “Olfactory Transmucosal SARS-CoV-2 Invasion as a Port of Central Nervous System Entry in Individuals with COVID-19,” by Jenny Meinhardt et al., in Nature Neuroscience, Vol. 24; February 2021 (nasal passage reference)
Nath, who also studies ME/CFS, says that “we think mechanistically they are going to be related.” Researchers suspect that ME/CFS, like some cases of long COVID, could be autoimmune in nature, with autoantibodies keeping the immune system activated. ME/CFS has been difficult to study because it often arises long after a mild infection, making it hard to identify a viral trigger. But with long COVID, Nath says, “the advantage is that we know exactly what started the process, and you can catch cases early in the [development of] ME/CFS-like symptoms.” In people who have had ME/CFS for years, “it’s done damage, and it’s hard to reverse that.” Nath speculates that for long COVID, if doctors could study people early in the illness, they would have a better chance of reversing the process.
Torgerson hopes that researchers will ultimately come to better understand ME/CFS because of COVID. “COVID has been more carefully studied with better technology in the time we’ve had it than any other infectious disease ever. I think we’ll learn things that will be applicable to other inflammatory diseases driven by infection followed by an autoimmune process.”
Team Treatment
Ghormley, after months of illness, sought care at UCLA Health’s long COVID clinic, among the country’s few comprehensive, multidisciplinary programs for people with this syndrome. Even though her symptoms are rooted in nervous system dysfunction, she needed an array of medical specialists to treat them. The clinic grew out of a program aimed at coordinating care for medically complex COVID patients, says its director Nisha Viswanathan, an internist and primary care physician. In following up with COVID patients after several months, she realized that “we had a group of patients who still had symptoms. There was no understanding around the condition; we were just trying to see what we could offer them.” Viswanathan and others convened a biweekly meeting of UCLA Health doctors in pulmonology, cardiology, neurology, psychiatry and other specialties to discuss individual cases and overall trends.
At UCLA Health, Pittman coordinates Ghormley’s treatment. He says the interdisciplinary team is crucial to getting patients the best possible care. “Oftentimes there are so many symptoms,” and some patients have seen multiple specialists before arriving, but not necessarily the right ones. As long COVID primary care providers, he says, “we do the initial testing and get them to the right person.” For Ghormley, that list of providers includes Pittman, along with a neurologist, a pulmonologist, a cardiologist, a psychiatrist, a trauma counselor, a rheumatologist and a gynecologist.
The team approach has also been critical for doctors trying to understand a brand-new disease, Pittman says. “It’s been a very interesting journey from knowing almost nothing to knowing a little bit now, and we’re learning more every day, every week, every month,” he says. The term “long COVID” “is an umbrella, and I think there are multiple diseases under that umbrella.” Although each long COVID patient is unique, Pittman says, “we start to see patterns developing. And with Ghormley, we saw a pattern of dysautonomia, which we see frequently.”
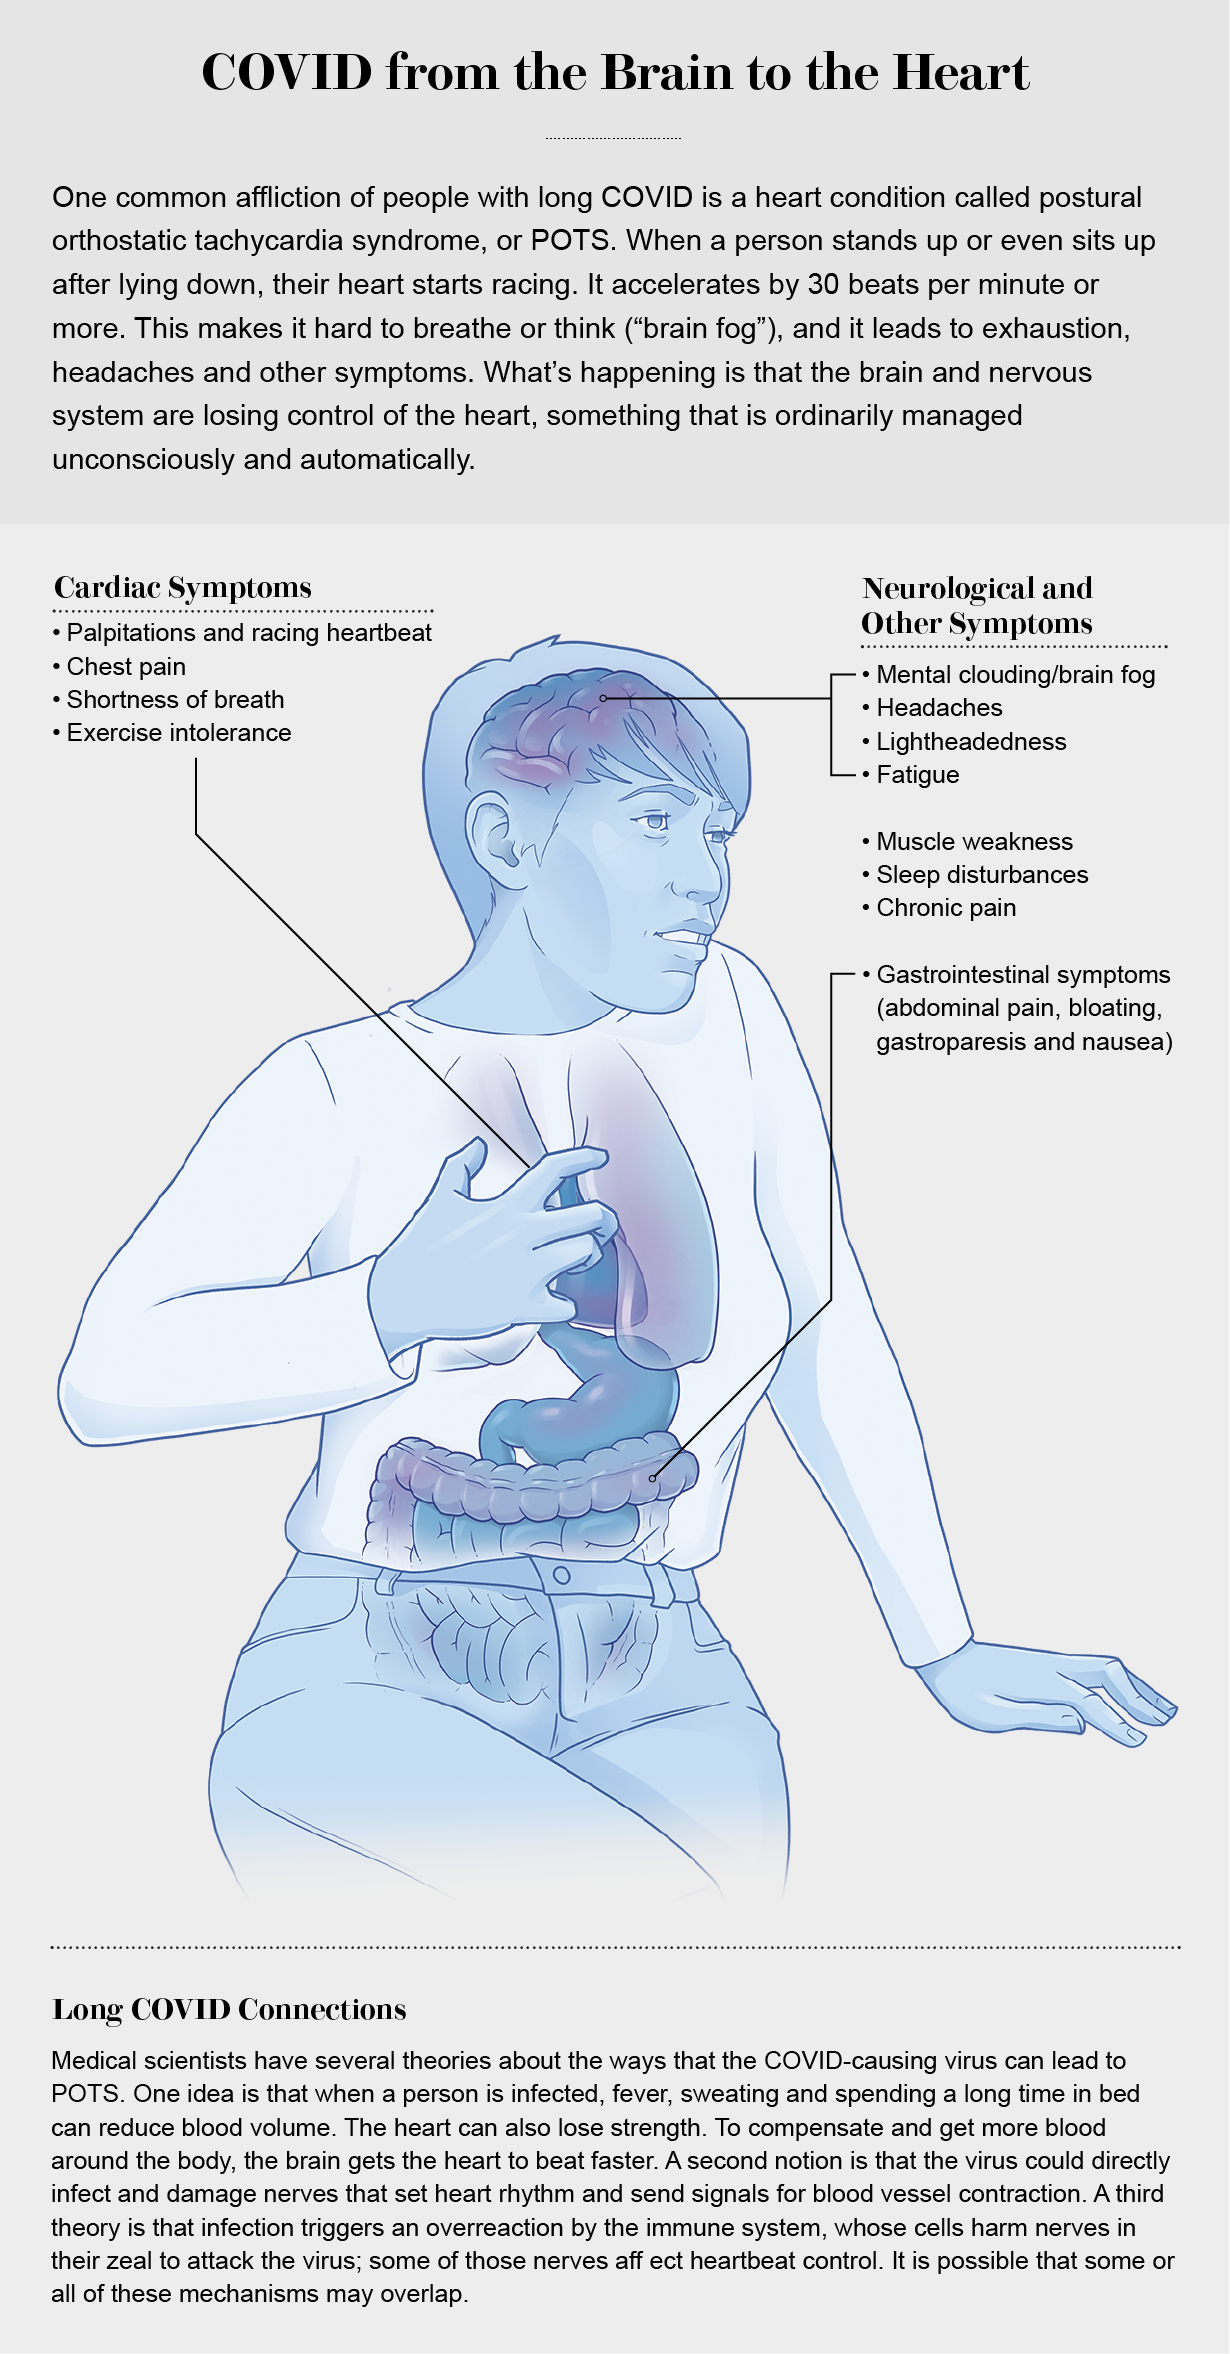
Dysautonomia impairs the autonomic nervous system, a network of nerves that branch out from the brain or spinal cord and extend through the body, controlling unconscious functions such as heartbeat, breathing, sweating and blood vessel dilation. For Ghormley, like many people with long COVID, dysautonomia takes the form of postural orthostatic tachycardia syndrome, or POTS. The syndrome encompasses a collection of symptoms that include a racing heart rate—particularly on standing—and fatigue, and it can cause bowel and bladder irregularities. POTS can also be a component of the exhaustion that comes with PEM. Although the symptoms may seem to affect the body, they stem from nervous system dysfunction.
Ghormley’s dysautonomia led her to see cardiologist Megha Agarwal at a UCLA clinic near her home. Many physicians are not familiar with POTS, but Agarwal is particularly attuned to it, having seen it in some of her patients before COVID hit. “There’s dysregulation of the nervous system, and so many things can cause it: some cancer therapies, viruses, autoimmune conditions.” Agarwal recognized POTS in Ghormley in the fall of 2020, when very little was known about long COVID. Now she believes “POTS is really what long-haul COVID is causing” in many patients. Luckily, Agarwal says, there are medical interventions that can help.
Tachycardia—the T in POTS—causes the heartbeat to speed up, contributing to exhaustion and fatigue in addition to stressing the heart itself. Drugs called beta-blockers (for the beta-adrenergic receptors they shut off in the heart) can lower the heart rate and improve symptoms. “When heart rate is controlled, not only does the pump improve,” Agarwal says, “[but people’s] energy improves, their fatigue is gone, and sometimes there’s better mental clarity.” For some patients like Ghormley, beta-blockers are not enough, so Agarwal adds a medication called ivabradine. “It’s a bit off-label, but it’s currently being aggressively studied” for POTS. For Ghormley, the combination led to real improvements, “so now she doesn’t feel like she ran the Boston Marathon when all she did was sit down and stand up at work or take a shower,” Agarwal says.
Among Ghormley’s toughest symptoms is her brain fog, a catchall term for a slew of cognitive problems that make it hard for her to function. For days when Ghormley works, her psychiatrist prescribes Adderall, a stimulant used to treat attention deficit hyperactivity disorder that helps her concentrate and stay focused. That has “helped immensely,” Ghormley says.
Ghormley credits her doctors and Agarwal in particular with doing the detective work to dig into her symptoms. “Nobody knew anything about it, but everyone listened to me,” Ghormley says. Perhaps because she was a professional from a medical field, no one “brushed me aside.”
That’s unusual for people with long COVID, many of them women, who are often dismissed by physicians who doubt their complaints are real. “Patients just don’t feel heard,” Viswanathan says. “I had a patient who told me everything, and after, I just said, ‘This must be so hard for you. I want you to know that everything you’re feeling is real, and I’ve seen so many patients like you.’ And she started crying. She said, ‘No one has told me that. I can’t tell you the number of times I was told it was in my head.’”
Credit: Now Medical Studio; Sources: “Postural Orthostatic Tachycardia Syndrome as a Sequela of COVID-19,” by Cameron K. Ormiston et al., in Heart Rhythm, Vol. 19; November 2022; “Long COVID-19 and Postural Orthostatic Tachycardia Syndrome—Is Dysautonomia to Be Blamed?” by Karan R. Chadda et al., in Frontiers in Cardiovascular Medicine; March 2022 (references)
In addition to drugs, other types of therapies, including physical therapy, can help improve some symptoms. But people who experience PEM face a particular challenge when using movement therapies. Pittman says the exertion can make these patients feel worse. “We don’t want patients to go to not moving at all, but sometimes the type of movement they’re doing may be flaring their symptoms.” He notes that often PEM strikes young, previously healthy people who will say, “‘I need to push myself,’ and then they go way too far and get worse. Our job is to try to find that middle ground and then make that consistent over time, so they’re not getting further deconditioned but they don’t have the PEM, which has been shown to set them back.”
The Long Haul
Some patients, Pittman says, “have the expectation that they’re going to come in, and within a month they’re going to be back to normal. And resetting those expectations can be really challenging. You have to be really empathetic because people’s lives have completely changed.” But sometimes patients’ quality of life can improve noticeably when they are able to adjust to a new normal. Still, he says, “patients have so many questions, and I can’t lead them down a physiological pathway. I can tell them there’s neuroinflammation, maybe there’s autoimmunity, but we still don’t have the answers. Sometimes it’s really tough for us to accept and for the patient to accept that we just have to try our best.”
A number of people, Viswanathan says, benefit from reducing various treatments they have accumulated. Some people become so desperate that they will try anything from supplements to off-label medications to untested potions from the Internet. Stopping those sometimes leads to improved symptoms, she says.
Psychological care and support groups can help. Lavretsky adds that “lifestyle choices can play a huge role in improvement,” particularly better sleep habits and the use of breathing exercises to control anxiety. She tells people their bodies can heal themselves if the patients and clinicians find the right tools.
Whether that’s true for everyone remains to be seen, Viswanathan says. “We see many patients who have gotten better with time. I have patients whose symptoms have disappeared in the course of a year, or they disappear and occasionally flare up again.” But for some, she says, “it could last many years.”
“We’re going to be addressing this for probably decades,” Viswanathan says. “COVID is not going to go away so much as we’re just going to get used to living with it, but part of [that] means that people will continue to develop long COVID.”
Vaccination appears to reduce the risk of long COVID. But a study published in May 2022 in Nature Medicine suggests the protection, though real, is not as good as one might hope. The survey of electronic health records from the U.S. Department of Veterans Affairs looked at the relatively small portion of vaccinated people who subsequently became infected. They developed long COVID only 15 percent less often than unvaccinated people. “These patients can have symptoms for one to two years or longer, and so every month you’re racking up more patients. Even if it’s 15 percent less, the total population of patients is still growing and exploding,” Pittman says. The best way to avoid getting long COVID, experts all agree, is to avoid getting COVID at all.
The syndrome is still mired in a lot of medical uncertainty. Patients might have one or a combination of the problems investigated so far: Long COVID might be caused by viral particles that persist in the brain or other parts of the nervous system. Or it might be an autoimmune disorder that lasts long after the virus has disappeared. Maybe overactive immune cells continue to perturb the nervous system and nearby blood vessels. Fortunately, the increasing ability to recognize specific problems is helping clinicians hone treatments that give patients the best chance of recovery.
Although Ghormley says her care has dramatically improved her symptoms and allowed her to “do some normal things again,” she continues to experience flare-ups that make it impossible for her to work for weeks at a time. One day last year she skipped a dose of her heart medication and made a Target run in the southern California heat. “I got home and basically collapsed in the hallway. Since then, everything has been out of whack. If I try to move around, my legs give out.” Most frustrating—and scary—to Ghormley is the unpredictability of her symptoms. “They have changed so much; some are manageable, some debilitating. One thing will get better, and another thing comes back. I’m always hopeful that it’s going to get better, but I just don’t know.”
Employees stories | The Biden administration announced Monday its strategy to end the Covid-19 community health and fitness emergency Could 11, in accordance to The New York Situations. The adjust will usher in a crescendo of difficult public health and fitness policy modifications, signaling a new period for The united states.
A person of the more impactful adjustments will affect the availability of free of charge Covid exams, treatment plans and vaccines, The Instances reported. The adjustments in plan may well eradicate entry to free Covid screening, at-residence screening kits and vaccinations. Out-of-pocket expenditures will apply to companies that were being beforehand no cost beneath the general public wellbeing unexpected emergency.
Due to the fact the general public well being unexpected emergency has been in position for the entirety of Biden’s time in business office, the White Residence emphasised a will need for an organized tactic to the changeover. The May 11 declaration is developed to give well being officials, hospitals and wellbeing care providers sufficient time to put together for protocol variations.
Condition overall health officers really encourage residents to refer to the CDC’s local community levels map to monitor the severity of Covid-19. As of Jan. 31, Charleston County’s group stage is minimal, which is in line with the earlier reporting period.
For the 7 days ending Jan. 28, Covid-connected hospitalizations in Charleston had been down 19.7{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} in comparison to the 7 days ending Jan. 21. For the week ending Jan. 28, state officials described 48 individuals died from Covid-19 — 28 more deaths than the prior week. In this time period, 5,627 new cases have been documented — 962 much less than the previous reporting period.
Most current COVID-19 data
As of Dec. 20, the South Carolina Office of Health and Environmental Manage (SCDHEC) will no extended include data on ventilations and weekly developments owing to a new program of monitoring adopted from the U.S. Office of Well being and Human Companies.
SCDHEC transitioned to weekly reporting of new Covid data in December 2022. The most latest numbers have been claimed Tuesday and protected Jan. 15-21. In other info:
Proportion of S.C. citizens age 12+ with at the very least just one vaccine: 69.5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}
Percentage of S.C. people age 12+ who have concluded vaccination: 60.6{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}
Percentage of S.C. citizens age 5-11 with at the very least a single vaccine: 23.5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}
Share of S.C. citizens age 5-11 who have accomplished vaccination: 19.5{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}
Metropolis Paper has been bringing the finest information, food items, arts, audio and occasion coverage to the Holy City because 1997. Assist our ongoing endeavours to spotlight the very best of Charleston with a a single-time donation or develop into a member of the Town Paper Club.
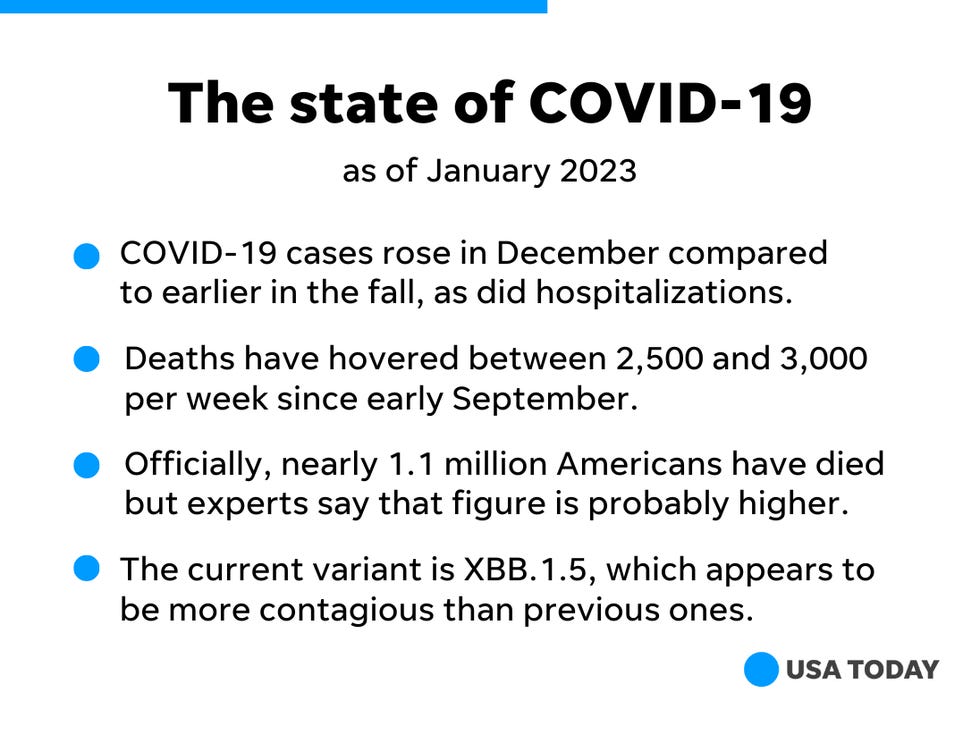
The newest COVID-19 variant is so contagious that even people who’ve avoided it so far are getting infected and the roughly 80{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of Americans who’ve already been infected are likely to catch it again, experts say.
Essentially, everyone in the country is at risk for infection now, even if they’re super careful, up to date on vaccines, or have caught it before, said Paula Cannon, a virologist at the University of Southern California.
“It’s crazy infectious,” said Cannon, who is recovering from her first case of COVID-19, caught when she was vacationing over the holidays in her native Britain.
“All the things that have protected you for the past couple of years, I don’t think are going to protect you against this new crop of variants,” she said.
The number of severe infections and deaths remains relatively low, despite the high level of infections, she said, thanks to vaccinations – and probably – previous infections. But the lack of universal masking means that even people like her, who do wear masks, are vulnerable.
The latest variant, called XBB.1.5, grew exponentially over the month of December, from about 1{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of cases nationwide to 27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} as of Jan. 7, according to data from the Centers for Disease Control and Prevention. The variant is likely behind the vast majority of cases in New York and New England.
Its growth is probably due to XBB.1.5’s characteristics – it appears to bind even more tightly to receptors in the human body than its predecessors – as well as human behavior, such as traveling and not masking.
It’s a good idea to do what you can to avoid getting infected, said Dr. Ziyad Al-Aly, chief of research and development at the VA St. Louis Health Care System and a clinical epidemiologist at Washington University in St. Louis.
It’s still early and there are a lot of unknowns about XBB.1.5, he said. Every infection makes someone vulnerable to a bad course of the disease and to the lingering, miserable symptoms of long COVID, Al-Aly’s research shows.
“Reinfection buys you additional risk,” he said.
As the United States enters the fourth year of COVID-19, we’re providing an update on the state of the pandemic. Here’s a preview of what you’ll learn in this article:
COVID-19 symptoms typically last around five to seven days and can include fever, sore throat, muscle aches, exhaustion, nausea, cough and sinus congestion, among other problems.
Symptoms with XBB.1.5 are the same as with earlier variants and can range from almost nothing to shortness of breath and low oxygen levels that require emergency medical attention.
Early in the pandemic, COVID-19 often cost people their sense of taste and smell, at least temporarily, but that symptom seems less common, possibly because of vaccination or previous infection rather than a change in the virus, said Dr. Peter Hotez, an infectious disease specialist and co-director of the Center for Vaccine Development at Texas Children’s Hospital.
It takes anywhere from two to 14 days for exposure to lead to symptoms and a positive test.
People with COVID-19 are contagious as long as they remain positive on a rapid test, typically for about 10 days, but often longer.
The CDC recommends people isolate for at least five days and wear an N95 or similarly protective mask for at least 10 days when around others. Day One is considered the first full day after symptoms start.
A PCR test, which is considered the gold standard for diagnosing COVID-19, can remain positive for months because it detects viral fragments as well as the whole, infectious virus. To confirm the end of the contagious period, experts instead recommend a negative rapid test after 10 days or two within 48 hours if sooner.
Yes. While a previous infection provides some protection, that fades over time and as the virus evolves into different variants.
Some people who had a mild case with a first infection get hit harder the second or third time, while others might suffer less.
“Even if you’ve had it before, that doesn’t mean your next bout is going to be the same,” Cannon said. There are lots of factors at play in determining the seriousness of an infection, she said, including prior immunity, the nature of the variant and how long it’s been since your last infection or vaccination.
It’s possible that her recent infection was much milder than her husband’s, for instance, because she had caught a head cold a few days earlier, while her husband hadn’t. A respiratory virus can put the immune system on high alert and might have provided some protection when she was exposed to COVID-19.
“It’s part of the bigger dance between our bodies and our immune system,” Cannon said.
The methods for avoiding infection haven’t changed, though it can be hard to stick with them when no one else is: Get vaccinated, wear a mask and avoid crowded spaces.
First is getting vaccinated. This will protect against severe infection as well as reduce the risk of passing the virus to others, said Hotez, also dean of the National School of Tropical Medicine at Baylor College of Medicine.
The newer boosters, which take aim at both the original virus and the BA.4/BA.5 variants common this summer, are more protective against XBB.1.5 than earlier boosters. People who are up to date on their COVID-19 shots probably don’t shed as much virus for as long, so they’re also less likely to pass it on, he added.
Past infection provides some protection against severe disease, but that protection is “highly unreliable,” Hotez said.
Second is wearing a mask. Good quality, well-fitting masks, like an N95 or KN95 can reduce the risk of infection.
Cannon said people sometimes get annoyed at her mask-wearing “because it’s like I’m reminding them that (COVID) is still a problem.” But she doesn’t want to accidentally pass COVID on to someone who might be more vulnerable to the virus.
Third is avoiding crowded indoor spaces. You’re less likely to get infected in large indoor spaces with high ceilings and lots of ventilation than in cramped, airless ones.
It’s a good idea to have a plan ready in case you get sick, Cannon said. She suggests every plan include:
How to isolate from others in your household
The contact number for a health care provider who can prescribe an antiviral
Equipment such as rapid coronavirus tests, extra masks, a thermometer and a pulse oximeter to make sure the patient’s blood oxygen level doesn’t drop below the low 90s
Every U.S. household is eligible for four free coronavirus tests from the government that can be ordered from this link: covid.gov/tests.
For someone over 60 or with medical conditions like obesity that raise the risk for serious disease, the first step after a positive test should be a call to the doctor to get the antiviral Paxlovid, she and others said. The government has pre-bought millions of doses, so they are available for free.
Some doctors are hesitant to provide the antiviral because people may need to stop taking common medications during the five-day treatment course, but it’s essential for people at high risk for serious disease, Hotez said. “Any senior going on Paxlovid is not dying,” he said.
“We can’t stop people getting infected,” Cannon added, “but we absolutely can stop people from being seriously ill. Gosh, why wouldn’t you take it?”
Every COVID-19 infection increases your risk for serious disease and for long COVID, which brings sometimes debilitating symptoms that can linger for a year or more.
Older adults are more vulnerable, Al-Aly said, “but it doesn’t mean younger people are totally shielded.” Long COVID, too, can strike people at any age from childhood through to the 101-year-old recently treated at his hospital, he said.
Vaccination reduces the risk of long COVID by 15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} to 30{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}, according to a study he recently published. Another study he is working on shows Paxlovid reduces the risk by 26{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}.
Cannon’s daughter works in a long COVID clinic and regularly sees patients who are in their 20s or 30s, “healthy people who didn’t even have a particularly bad bout of COVID who now have a massively debilitating set of symptoms.”
All six experts interviewed by USA TODAY this week dismissed the idea that there is somehow an upside to getting infected: Vaccination provides better protection against future infection without the risk.
“I’d be happy if I never got any virus again,” Cannon said. “And I say this as a professional virologist.”
COVID-19 has been perhaps the most successful virus in all of human history, Cannon said, infecting billions of people across the planet.
While she worries about how it might continue to evolve, she hopes it’s a good sign that for the last year, all the variants have been descendants of omicron.
Before that, the original virus, alpha, beta and delta had been “radically” different from each other.
“The virus is now in this committed lineage,” Cannon said, which might mean it won’t evolve away from the protection against serious disease thatnearly everyone now has from vaccinations and previous infections.
Contact Karen Weintraub at kweintraub@usatoday.com.
Health and patient safety coverage at USA TODAY is made possible in part by a grant from the Masimo Foundation for Ethics, Innovation and Competition in Healthcare. The Masimo Foundation does not provide editorial input.