Washington — U.S. wellness regulators on Tuesday approved the initially gene treatment for hemophilia, a $3.5 million just one-time therapy for the blood-clotting condition. The Food items and Drug Administration cleared Hemgenix, an IV treatment method for older people with hemophilia B, the much less common sort of the genetic condition which primarily impacts adult men.
Currently, individuals obtain repeated, high priced IVs of a protein that assists blood clot and protect against bleeding.
Signage for CSL Behring, a device of CSL Ltd., is displayed at one of the company’s crops in Melbourne, Australia, in a July 2, 2014 file image.
Carla Gottgens/Bloomberg by way of Getty
Drugmaker CSL Behring, based in Pennsylvania, declared the $3.5 million price tag soon soon after the Food and drug administration acceptance, saying its drug would in the end lower health and fitness care fees due to the fact people would have fewer bleeding incidents and will need less clotting treatments.
According to a study cited by the Countrywide Library of Medication, the cost makes Hemgenix the most high-priced medicine in the planet, very easily topping Novartis’ Zolgensma gene remedy for spinal muscular atrophy (SMA), which costs ideal all over $2 million for each dose and is also a solitary-dose medicine.
Strangers donate more than $2M to conserve little girl’s daily life
01:53
Like most medications in the U.S., most of the expense of the new remedy will be paid out by insurers, not sufferers, together with private strategies and governing administration packages.
Immediately after decades of study, gene therapies have begun reshaping the cure of cancers and uncommon inheritable diseases with medications that can modify or right mutations embedded in people’s genetic code. Hemgenix is the to start with these types of procedure for hemophilia and several other drugmakers are doing work on gene therapies for the more frequent sort of the condition, hemophilia A.
“Present day acceptance provides a new remedy solution for individuals with hemophilia B and signifies essential progress in the progress of progressive therapies,” stated the FDA’s Dr. Peter Marks.
The agency did not specify how very long the therapy functions. But CSL Behring explained patients need to advantage in conditions of minimized bleeding and greater clotting for yrs.
Hemophilia pretty much often strikes males and is caused by mutations in the gene for a protein necessary for blood clotting. Small cuts or bruises can be lifetime-threatening, and many people need remedies at the time or extra a week to stop significant bleeding. Remaining untreated, the situation can lead to bleeding that seeps into joints and internal organs, including the mind.
Hemgenix delivers a functioning gene for the clotting protein to the liver, where it is manufactured.
Hemophilia B affects about 1 in 40,000 individuals and accounts for approximately 15{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of these with the illness, according to the Food and drug administration.
The Fda said it granted approval primarily based on two modest research, which includes just one that showed these having the drug had elevated stages of the clotting protein, lessened require for standard treatment method and a 54{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} fall in bleeding difficulties.
Previously this yr, European regulators permitted a equivalent gene therapy for hemophilia A. That drug, from drugmaker BioMarin, is continue to underneath evaluation at the Fda.
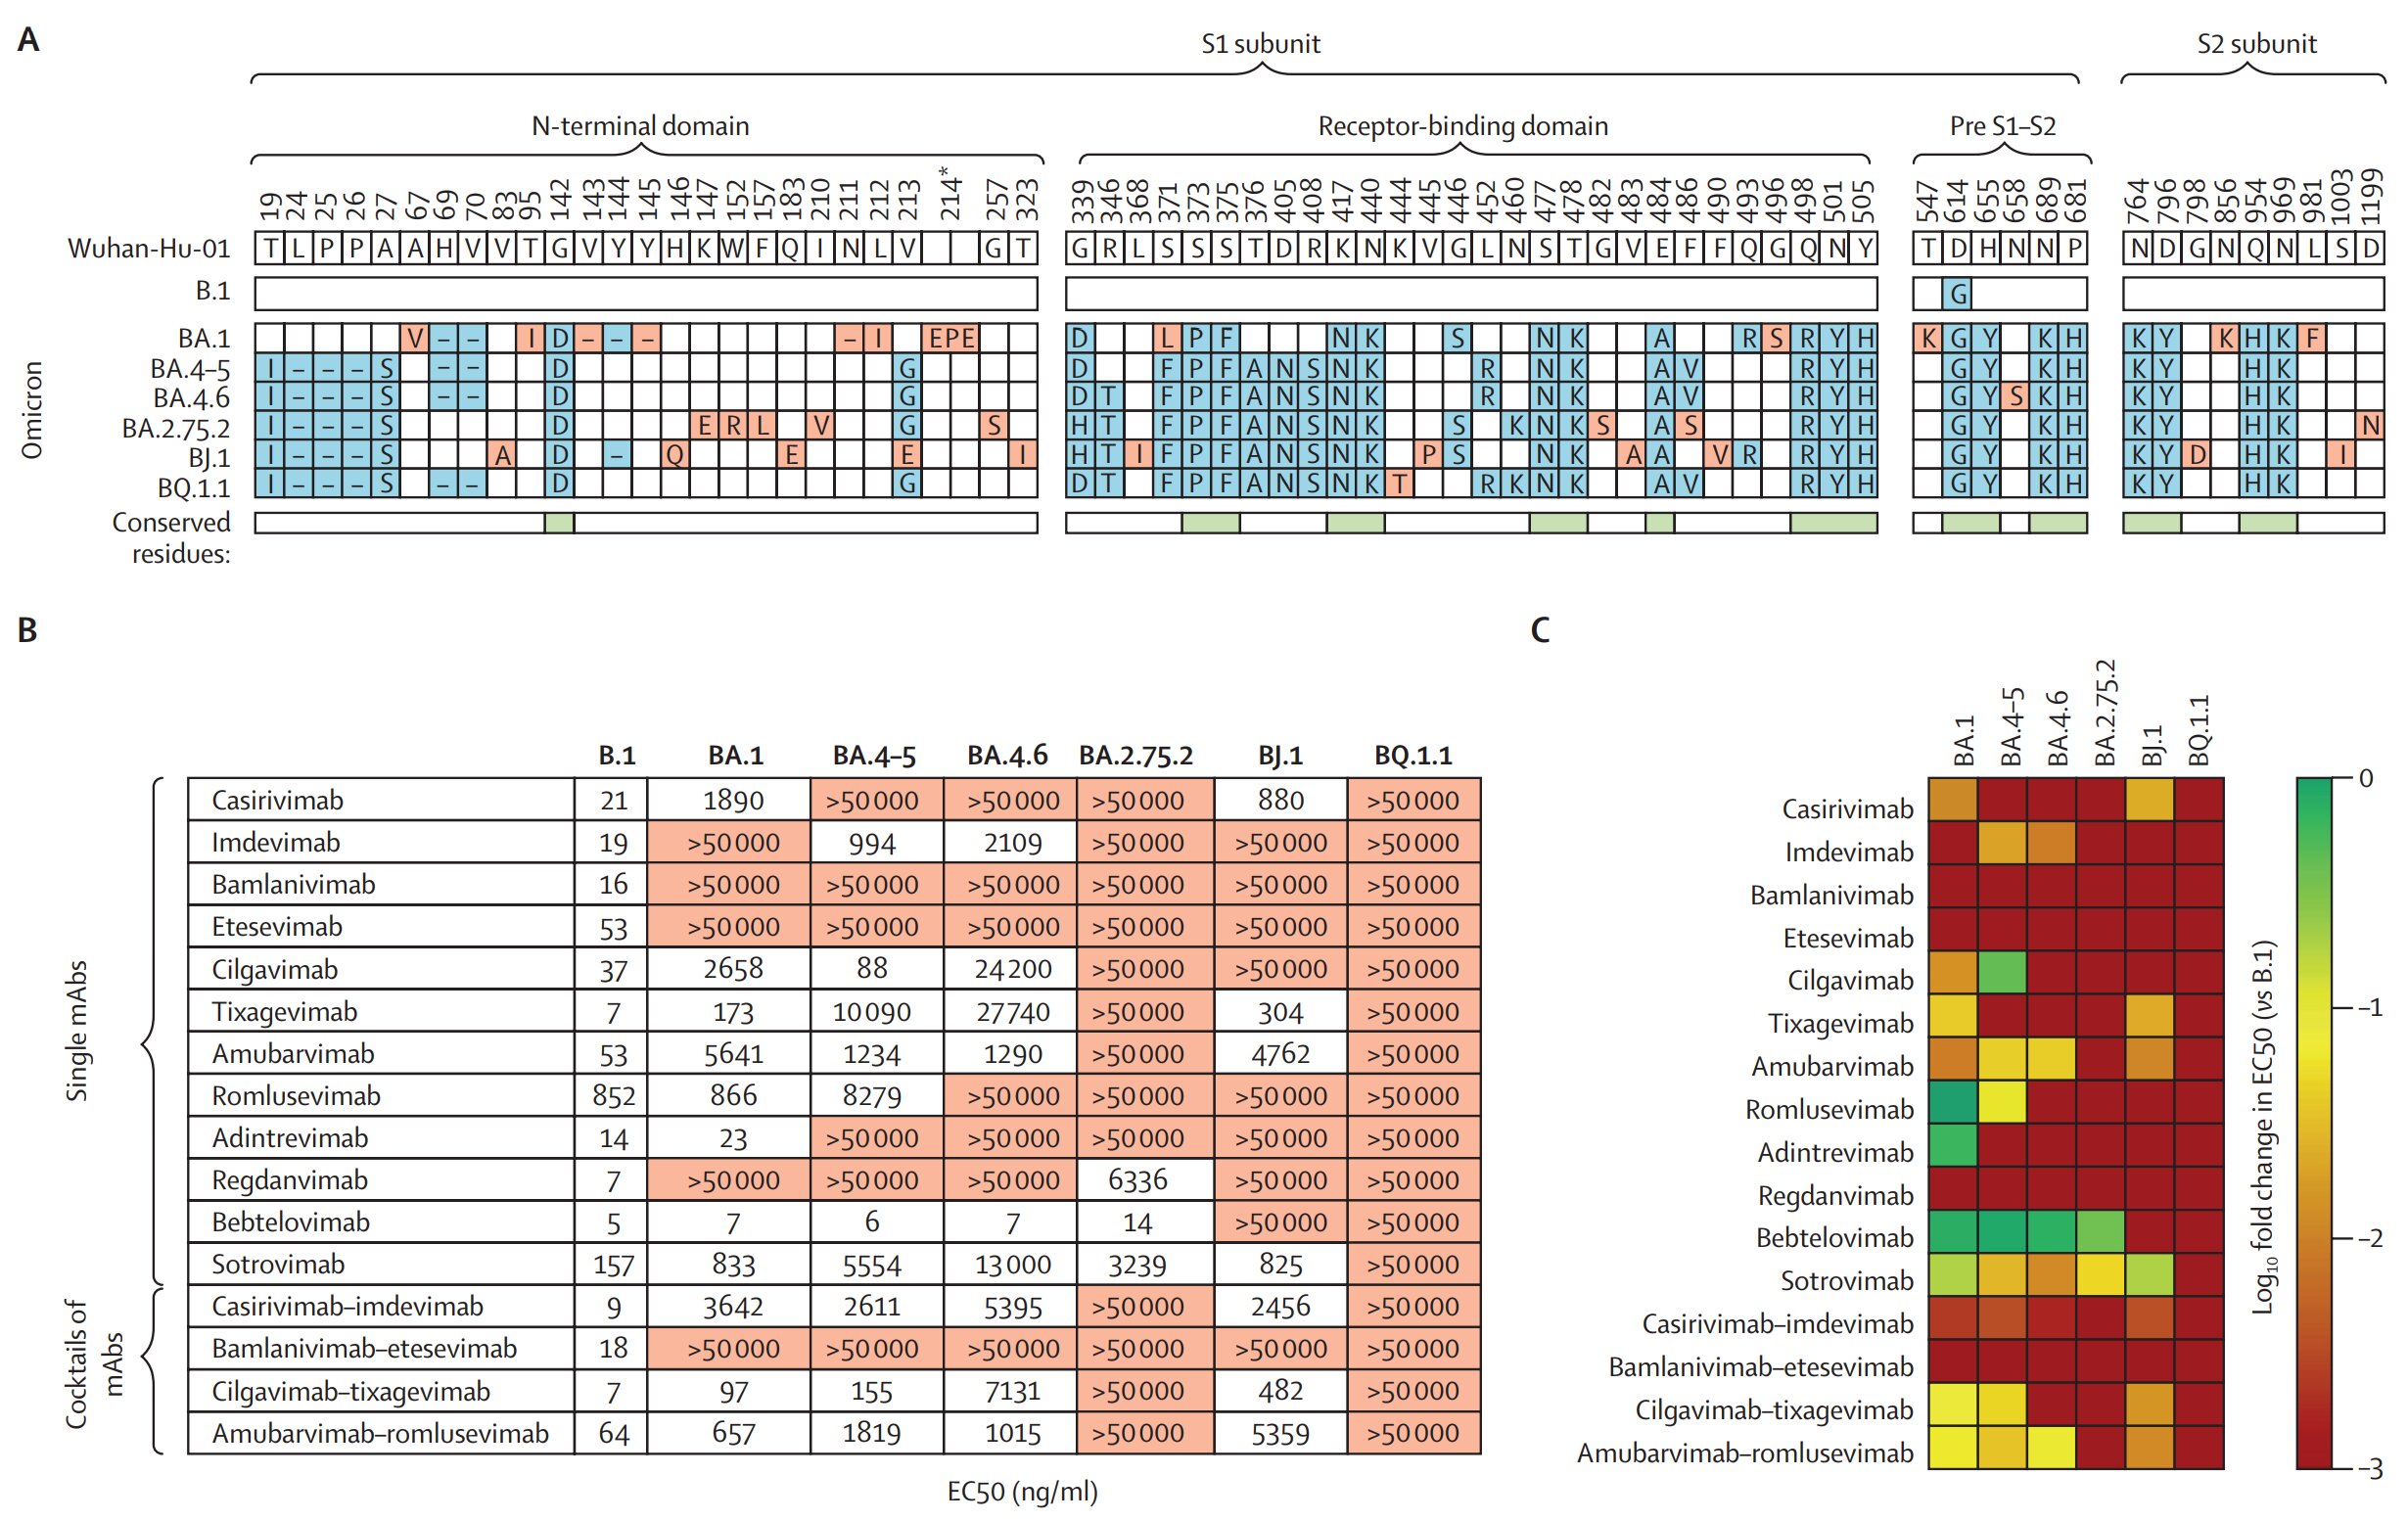
Comprehensive resistance of Omicron sublineage B.Q.1.1 to neutralization by mAbs (A) Area of mutations (blue and crimson) in the spike proteins of SARS-CoV-2 lineages B.1, BA.1, and BA.4–5 (which are identical at the amino acid amount), BA.4.6, BA.2.75.2, BJ.1, and BQ.1.1 (numbered in accordance to the spike protein of SARS-CoV-2 Wuhan-Hu-01). Mutations that are exclusive to only one of the Omicron sublineages are highlighted in crimson and conserved mutations between Omicron sublineages are indicated beneath the sequences in eco-friendly. (B) Pseudovirus particles carrying the indicated S proteins were being preincubated with different concentrations of solitary mAbs or cocktails of mAbs, in advance of currently being inoculated on to Vero cells. Pseudovirus entry was analyzed at 16–18 h publish-inoculation, by measuring firefly luciferase activity in mobile lysates, and was normalized towards samples without the need of any antibodies ({35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} inhibition). The EC50 was calculated by use of a non-linear regression model. Information stand for the signify of three organic replicates (done with 4 technological replicates). For further information see the appendix (p 12). (C) Heatmap indicating the fold alter in EC50 compared with B.1 pseudovirus particles. EC50=the focus essential for 50{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of highest inhibition. mAbs=monoclonal antibodies. Pre S1–S2=the area among the receptor-binding domain and the S1–S2 cleavage internet site. S=spike. *The BA.1 spike protein contains a exceptional insertion at place 214 (EPE). Credit rating: The Lancet Infectious Diseases (2022). DOI: 10.1016/S1473-3099(22)00733-2
A put together workforce of scientists from Leibniz Institute for Primate Analysis and Friedrich-Alexander College of Erlangen-Nürnberg, equally in Germany, has located that the SARS-CoV-2 omicron variant BQ.1.1 is resistant to all recognised monoclonal antibody treatments. In their analyze, printed in The Lancet—Infectious Diseases, the team tested a host of omicron sublineages versus all regarded antibody treatments.
Monoclonal antibody remedies, as their identify implies, are therapies that prompt antibody output in men and women by now infected with a pathogen. As the pandemic has worn on, clinical researchers have constantly searched for new monoclonal antibody treatments to combat off potential variants of the virus. But now, it seems researchers are shedding that race. In this new effort and hard work, the researchers appeared at COVID-19 variants and the success of monoclonal antibody remedies utilised to battle them.
In their do the job, the scientists appeared at BJ.1, BA.4.6, BA.2.75.2 and BQ.1.1—all subvariants of the omicron pressure of the SARS-CoV-2 virus. They analyzed each and every from all of the currently accessible monoclonal antibody treatment options to see how well the therapies are functioning. They located that all of the variants were being resistant to some of the solutions and that BQ.1.1 was resistant to all of them.
The discovering is alarming in a single respect—BQ.1.1, along with BQ.1, currently comprise virtually 50 percent of all bacterial infections in the U.S. The excellent information is that since of the multi-pronged attack the healthcare local community has taken towards the virus, collectively with significant figures of folks infected, all round figures of bacterial infections are low.
Also, monoclonal antibody treatments are commonly only supplied to infected people with underlying conditions that are thought to be at fantastic hazard of serious troubles from the disease. On the other hand, since of the unpredictable character of the virus, no a person genuinely is aware of what this new growth may possibly necessarily mean for the development of the pandemic—except for people unfortunate individuals with underlying ailments who, in the close to potential, transpire to capture the BQ1.1. model of COVID-19.
Extra information and facts:
Prerna Arora et al, Omicron sublineage BQ.1.1 resistance to monoclonal antibodies, The Lancet Infectious Illnesses (2022). DOI: 10.1016/S1473-3099(22)00733-2
Citation:
Omicron variant BQ.1.1 uncovered to be resistant to all monoclonal antibody treatment options (2022, November 22)
retrieved 23 November 2022
from https://medicalxpress.com/news/2022-11-omicron-variant-bq11-resistant-monoclonal.html
This doc is issue to copyright. Apart from any truthful dealing for the reason of private research or analysis, no
aspect could be reproduced with no the penned authorization. The material is furnished for info uses only.
At the end of November, thousands of researchers from around the world will descend on San Francisco for the annual Clinical Trials on Alzheimer’s Disease meeting. The conference is a mainstay of the dementia research calendar, the place where the latest progress – and all too often, setbacks – in the quest for Alzheimer’s treatments are made public for the first time.
This year’s meeting is poised to be a landmark event. After more than a century of research into Alzheimer’s, scientists expect to hear details of the first treatment that can unambiguously alter the course of the disease. Until now, nothing has reversed, halted or even slowed the grim deterioration of patients’ brains. Given that dementia and Alzheimer’s are the No 1 killer in the UK, and the seventh largest killer worldwide, there is talk of a historic moment.
The optimism comes from a press statement released in September from Eisai, a Japanese pharmaceutical firm, and Biogen, a US biotech. It gave top-line results from a major clinical trial of an antibody treatment, lecanemab, given to nearly 2,000 people with early Alzheimer’s disease. The therapy slowed cognitive decline, the statement said, raising hopes that a drug might finally apply the brakes to Alzheimer’s and provide “a clinically meaningful impact on cognition and function”.
The announcement was greeted, broadly, with delight and relief from researchers who have endured failure after failure in the long search for Alzheimer’s drugs. But even the most enthusiastic conceded that significant questions remained. With only a press release to go on, it was hard to be sure the claims stood up. The answer will come on 29 November when researchers leading the trial, named Clarity AD, present their results at the San Francisco meeting.
‘If you can slow the decline, even a small amount, you will really start to see an impact at the economic and medical level.’ Illustration: Thomas Hedger at Grand Matter/The Guardian
Lecanemab has already sparked debate. Antibody drugs are so costly they are beyond the means of many countries. Lecanemab itself is not easy to administer, unlike pills and capsules: patients are required to attend clinic for an intravenous infusion twice a month. And the side-effects call for extensive monitoring: patients on the trial had regular scans for brain swelling and haemorrhages, a service many hospitals cannot provide at scale.
More importantly, lecanemab might not work very well. From the data released so far, it is unclear what difference it could make to the devastating burden inflicted by Alzheimer’s. Some doctors warn that the benefits of the drug seem so small, patients may not even notice. But others counter that any effect on Alzheimer’s deserves celebration: it proves the disease can be beaten, or at least slowed down. It’s a start, a concrete foundation to build on.
“Dementia is a global economic disaster as people are institutionalised while their disease progresses at huge cost to society and healthcare systems,” says Prof Giovanna Mallucci, former centre director of the UK Dementia Research Institute at the University of Cambridge, now principal investigator at Altos Labs. “If you can slow the decline, even a small amount, you will really start to see an impact at the economic and medical level.”
‘I feel like we might be able to offer something decent to patients within the next few years’ … Prof Bart De Strooper. Photograph: Ine Dehandschutter/Ine Dehandschutter/VIB
Researchers liken the situation to the HIV crisis in the 1980s. The first anti-HIV drug was far from ideal, but it paved the way for the highly effective therapies used today. “When you have that first breakthrough, it’s like the hole in the dyke that leads to a bigger hole,” says Prof Bart De Strooper, director of the UK Dementia Research Institute at University College London. “There is much more belief now that we can find something. As a doctor, I feel like we might be able to offer something decent to patients within the next few years.”
“This is not a cure by any stretch of the imagination, but if it does slow cognitive decline, it means that for the first time we are modifying the disease,” says Dr Richard Oakley, head of research at the Alzheimer’s Society. “We need to understand the real-world clinical benefit, but I’ve spoken to people and where there’s never been excitement, always hesitation, this does look like the real deal. We need to see the data, but everyone is now saying this is the beginning of disease-modifying treatments.”
Alzheimer’s accounts for more than 60{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of the 55 million cases of dementia worldwide. The condition costs the UK £25bn a year, a figure that is on course to nearly double to £47bn by 2050. The most common early signs are memory problems, but as the disease progresses, people can find themselves lost in familiar places, having trouble with decisions, struggling with simple tasks, experiencing mood swings and changes in personality. It is a terminal condition: typically, people die within eight years of an Alzheimer’s diagnosis.
The cognitive decline in Alzheimer’s arises from the relentless destruction of neurons, the cells that ferry information around the brain. The effect goes far beyond normal age-related brain shrinkage: on death, a patient’s brain can weigh 140g less than before the disease took hold – a reduction of more than 10{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc}.
Exactly what kills the brain cells is still up for debate. In some families blighted by early onset Alzheimer’s, scientists have found mutations that cause abnormal clumps, or plaques, of a brain protein called amyloid beta to build up between neurons. Above a certain tipping point, these plaques seem to aid the formation of harmful tangles of another brain protein called tau. These accumulate inside the neurons themselves. More tangles tend to mean greater cognitive decline.
But inherited forms of Alzheimer’s are rare. In most patients, the decline is likely to be driven by a messy mix of processes, which fuel one another. Amyloid and tau are still in the frame, but other toxic proteins, chronic inflammation, vascular problems, cellular health, and faulty disposal of waste from the brain may all contribute. “If we think about Alzheimer’s in old age, I don’t think most of these people have pure Alzheimer’s,” says De Strooper. “I think they have mixed forms of dementia. It’s not always clear what’s really driving the disease.”
Efforts to develop Alzheimer’s drugs have focused overwhelmingly on amyloid. Some aim to block enzymes involved in the production of abnormal amyloid, while others, such as lecanemab, are antibodies designed to clear it from the brain. Between 2007 and 2019, more than a dozen final-stage, or “phase 3”, trials of amyloid-targeting drugs reported results. None slowed cognitive decline; some even made it worse.
A computer-generated image of amyloid plaques – misfolded proteins that aggregate between neurons. Photograph: Artur Plawgo/Getty Images/iStockphoto
The failures split the research community. Some threw out the entire amyloid hypothesis. Others concluded that even if it was valid, amyloid wasn’t the best protein to target. Further concerns surrounded the trials themselves: many enrolled patients who already had Alzheimer’s symptoms. For them, removing amyloid may be too little, too late: snuffing out the match once the fire is raging. The problem is compounded by the insidious early phase of the disease, which destroys neurons without people noticing. “Your brain is so plastic that it can cope with a lot of damage before it starts to show symptoms,” says De Strooper.
In June last year, the US Food and Drug Administration gave the green light to the first new drug for Alzheimer’s in nearly 20 years. Biogen’s Aduhelm (aducanumab) became the first approved therapy to target amyloid, but the decision provoked a furore. An independent FDA committee advised against approval because Biogen’s trial data failed to show clear benefit.
But the FDA granted “accelerated approval” because it cleared amyloid plaques from patient’s brains, and therefore might slow the progression of Alzheimer’s if taken early enough, and for long enough. Several scientists resigned from the committee in protest, including Prof Aaron Kesselheim at Harvard Medical School, who told the regulator that its ruling was “probably the worst drug approval decision in recent US history”.
The FDA will rule on lecanemab in January 2023, with decisions in the UK and Europe to follow. While press-released data from the lecanemab trial suggests the drug slowed cognitive decline, the effect was small. After 18 months, cognition declined 27{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} less in those who took the drug compared with those on a placebo. On a common dementia rating scale, which scores people from 0 to 18 on memory, problem-solving and other tasks, those on lecanemab performed only 0.45 points better. The result is statistically significant, but it may not mean much for individual patients.
“The effect they’ve reported to date is very small. It’s not large enough to be clinically important,” says Prof Victor Henderson, director of the Alzheimer’s Disease Research Center at Stanford University. He warns that there is a subjective element to the dementia ratings that could matter when the observed benefit is so marginal. “I would be concerned that this could be a drug that has statistical significance without clinical significance and we may need to wait for something better,” he says.
One idea gaining ground in Alzheimer’s research is that drugs will need to remove amyloid fast to have any hope of showing a clinical benefit. The logic is laid out ina 2022 paper by De Strooper and Eric Karran at AbbVie, a US biopharmaceuticals firm. They argue that it will take time for the effects of amyloid removal to show up in thinking and memory tests. If a drug doesn’t push amyloid low enough, or takes years to do it, it probably won’t help, they suggest, at least not in the timeframe of most clinical trials.
Despite lecanemab’s reportedly small effect, Mallucci sees positives in the results. “What really needs to be trumpeted from this trial [assuming the results hold up] is that you can change the rate of decline of the disease. That half a point is subtle and the individuals might not feel very different, but you can build on it,” she says.
It’s likely that more research has been done on Covid in the past three years than on dementia in the past century. Photograph: Cultura Creative Ltd/Alamy
Chronic underfunding means patients have already waited too long for progress. Earlier this year, De Strooper searched the US medical database PubMed for dementia. He found 250,000 studies. He then searched for cancer and found 4.7m. Next, he searched for Covid, a disease that didn’t exist before 2019, and found 300,000 studies. It’s a rough metric, but it suggests that more research has been done on Covid in the past three years than on dementia in the past century.
The comparison with cancer is particularly striking. Decades of substantial funding and research have transformed cancer diagnosis and care. Under NHS England targets, people should wait no more than 28 days from referral to hear whether or not they have cancer. But for dementia, NHS England has only an “ambition” to diagnose two-thirds of patients. No timescale is mentioned.
With cancer, the full suite of diagnostic equipment is brought to bear on patients, from genome sequencing to advanced MRI and PET scanners. People often receive a detailed diagnosis of the cancer they have. Dementia diagnosis and care lag far behind. If Alzheimer’s patients can benefit from amyloid-clearing treatments, they will need an early diagnosis and evidence of amyloid in the brain. UK clinics are not close to being able to offer such services. “We could be in the situation in 2025 when we have access to a drug that modifies disease but are unable to give it to those most likely to benefit because we diagnose them too late and unspecifically,” says Oakley.
The real hope may lie in entirely different approaches. Antibodies may help some Alzheimer’s or pre-Alzheimer’s patients, but to have a major effect on the disease, a combination of drugs that hit different biological processes is needed. “I suspect antibodies will have a place for a small number of carefully selected patients, but we need multiple approaches,” says Mallucci. “This isn’t a feasible way forward for dementia treatment on a global scale. It’s not feasible economically or logistically.”
One idea is to administer vaccines that prompt the patient’s immune system to churn out antibodies to clear problematic amyloid and tau. De Strooper believes drugs that block key enzymes needed for the production of harmful amyloid are worth another look. Mallucci favours drugs that make the ageing brain more resilient, by protecting and reinvigorating brain cells. There are many potential approaches, including boosting the brain’s ability to clear toxic proteins and targeting inflammation. She has pioneered work on increasing the fitness of diseased brain cells, the ability to make new proteins, and on the “cold-shock” protein RBM3, which mammals release in hibernation and hypothermia. Both these approaches help to regenerate synapses, the connections between neurons, and – in mice, at least – help to protect against dementia by boosting memory and preventing brain cell death.
Another line of attack is to boost a compound called BDNF, which might also reinvigorate cells and help them build new connections. A new clinical trial at the University of California, San Diego, is about to test whether a BDNF-boosting gene therapy can help patients with early Alzheimer’s.
And this is what the field needs, says Oakley: more funding, more approaches, more trials. “We are beginning to see a future where we can make dementia a chronic condition, one you live with and die with but don’t die from,” he says. “We’ve seen it work in every other major condition that research has tackled, and we will see it in dementia. This first generation of amyloid-clearing drugs is only the beginning.”
Interdisciplinary rules to improve the cure of childhood arthritis at world stage. So significantly, there no uniform suggestions have existed for the therapy of arthritis of the jaw, a likely debilitating consequence of juvenile arthritis.
Health professionals about the planet lack insight into how most effective to treat arthritis of the jaw, which is a repeated and major consequence of juvenile arthritis.
Now, a team of scientists from Aarhus College, in collaboration with industry experts from a huge assortment of worldwide specialist teams, have formulated a established of interdisciplinary guidelines to improve the treatment of people with the condition.
The rules have a specific target on early prognosis and screening, and they can gain small children all more than the entire world, according to Peter Stoustrup, affiliate professor at Department of Dentistry and Oral Wellbeing at Aarhus University.

A much more timely initiation of treatment method will outcome in a much better procedure result. Untreated, arthritis of the jaw can result in main problems in adulthood, but treatment of the issue has lagged significantly due to uncertainty among the overall health industry experts and wellbeing systems, so this examine is essential for all little ones with jaw arthritis.”


Peter Stoustrup, Associate Professor, Department of Dentistry and Oral Overall health, Aarhus College

Complicated joint – difficult treatment
Close to 1,500 small children in Denmark have a diagnosis of juvenile arthritis, which generally results in inflammation of the jaw joint. This potential customers to soreness, reduced joint functionality, and development disruption in the encounter, which in severe circumstances may give increase to snooze apnoea and a need to have for surgical therapy of the patient’s jaw.
Up right up until now, it has proved complicated to obtain an powerful therapy for arthritis of the jaw, as it is a complicated joint, and optimal treatment method involves the involvement of numerous distinct groups of professional medical pros, which include radiologists, paediatric rheumatologists, physiotherapists, maxillofacial surgeons and orthodontists.
But now, a group of professionals from these disciplines has come jointly to create frequent suggestions and recommendations for interdisciplinary collaborative therapy in link with arthritis of the jaw.
“Well being devices are arranged in various strategies all over the planet, and the treatments available have therefore been a bit random. Now, guidelines have been drawn up for ideal collaboration in treating this situation, which can information the therapy of the individual client, but also aid the health and fitness methods to arrange themselves in these kinds of a way that this interdisciplinary approach to procedure is probable,” points out Peter Stoustrup.
The new suggestions and guidelines are based mostly on the awareness and evidence available in the area.
The research on which the guidelines are primarily based provides a foundation for follow-up analysis and data operate, and the suggestions will be revised as new awareness will become accessible.
Of great price in countries with no health and fitness insurance policy
In Aarhus, the interdisciplinary tactic to remedy has been regular practice for numerous years, and researchers from Aarhus College have thus been the driving force powering the advancement of the tips in the space.
With the suggestions in hand, Peter Bangsgaard Stoustrup says it will be less complicated to build facilities that exercise multidisciplinary remedy for kids and younger persons with arthritis of the jaw.
This will be especially worthwhile for clients in countries devoid of public wellbeing coverage – for case in point United states of america.
“We have on board centers like Boston Kid’s Medical center and hospitals in Atlanta and Calgary, who are rolling out the organizational and interdisciplinary approach to this cure that we are proposing. It is our hope that this can present inspiration for other centers,” suggests Peter Bangsgaard Stoustrup.
Supply:
Journal reference:
Stoustrup, P., et al. (2022) Management of orofacial manifestations of juvenile idiopathic arthritis: Interdisciplinary consensus-primarily based recommendations. Arthritis & Rheumatology.doi.org/10.1002/art.42338.
The metropolis of San Diego’s ambulance supplier, Falck, is set to see fines once again, soon after failing to fulfill response times and staffing targets. This 7 days an update on the company’s efficiency for July, August and September was listened to at the San Diego Metropolis Council’s Public Security and Livable Neighborhoods Committee meeting.
San Diego Hearth-Rescue (SDFD) Main Colin Stowell stated Wednesday he is nevertheless not observing the higher level of services promised by Falck.
“This is not acquiring better anytime shortly,” Stowell said. “We’re viewing the traits proper now with the staffing, and I do not really feel like nearly anything is likely to be corrected in the in close proximity to foreseeable future if we just hold out this out and hold out for it to increase.”
Previous November, Falck fully took in excess of San Diego’s 9-1-1 deal. Falck promised more paramedics and EMTs than the past provider (American Clinical Response), but facts from the city exhibits they have not after fulfilled every month staffing targets. Falck is contracted for a regular median of 900 hours. In July they strike 810 hrs, 768 in August and 756 in September.
Falck San Diego’s Managing Director Jeff Behm mentioned lower staffing degrees have continued to damage reaction periods.
“July, in phrases of compliance, was quite very good and August became a small even worse, but we observed September currently being just one of our worst months of the yr upcoming to January,” Behm mentioned, “a ton of that is absolutely because of to staffing, health issues and injury.”
Falck has previously been fined $1.5 million, and fire section officials claimed far more fines are on the way. Ultimate reaction time details for the very last handful of months is not nonetheless finalized and an SDFD spokesperson explained fines are however remaining tallied.
Falck officials said there is a nationwide lack of paramedics and EMTs. They also confess recruiting has been a obstacle, even soon after supplying signal-on bonuses.
“This ebb and circulation is quite noticeable — the trouble we have below is they are not competitive,” reported Anthony Sorci. Sorci has been a paramedic for 25 decades and president of the San Diego Association of Prehospital Gurus, which signifies Falck personnel.
Sorci reported staffing shortages are forcing time beyond regulation and initially responders are burning out.
“Our customers share activities of helplessness and mental anguish that has resulted in greater quantities of bodily accidents, sickness, PTSD (submit-traumatic stress dysfunction) and significant scientific depression,” Sorci said.
Sorci also stated deficiency of staff members has ambulances traveling all over the city, pushing up reaction times and even forcing the fire office to take their own actions.
“These delays have resulted in critical individuals getting transported to space hospitals by San Diego hearth engines mainly because the fire crews could no longer wait around for an ambulance at the scene…” Sorci stated.
A SDFD spokesperson verified fire engines have taken clients to hospitals. City info reveals availability for paramedic ambulances has risen from just more than an hour in April to 42 hrs in September.
Councilmember Raul Campillo was not pleased with the lack of enhancement.
“I’m upset that we appear to be in a placement that we just cannot supply our people what we promised them,” Campillo said. “It’s the similar song all over again.”
Councilmember Marni von Wilpert stated she does not want to listen to any much more.
“It appears that we have a fairly significant difficulty,” she said. “This contract is failing.”
Fire Main Stowell is preparing for the worst. He commissioned a review to glimpse into what it would just take for the metropolis to acquire around unexpected emergency clinical companies. Von Wilpert is keen to see possibilities offered during a meeting in January.
“Whether it’s an amendment to the agreement or if we have to do some kind of bond or takeover of the software, or deliver an additional software in to assist — we have to do some thing,” Von Wilpert mentioned.
Falck officers also sustain one particular cause for delays: their ambulances are being held also prolonged at hospitals. Some nearby hospitals press again on the cause. Scripps Wellness said in a letter to council users that unexpected emergency rooms are chaotic. They issue to county data that reveals most individual transfers materialize on-time.
“We see the per cent offloads in below 30 minutes in San Diego was 74{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} for that month (September),” wrote Monica Montano, Scripps Director of Authorities and Neighborhood Relations. “We would like to realize why the Falck information is various.”
A letter from the President of the Healthcare facility Association of San Diego and Imperial Counties pointed out the very same details. Officials from Sharp Grossmont Healthcare facility mentioned they are also busy, and that is when delays can materialize.
“Our division is generally open to chances to decrease offload delays and we seem ahead to partnering with our EMS (Crisis Clinical Provider) colleagues to be certain that people today are receiving the needed consideration and cure they need as rapidly as feasible,” explained Marguerite Paradis, director of Crisis Products and services and Essential Care at Sharp Grossmont Healthcare facility.
Councilmember Monica Montgomery Steppe said bottom line, no extra excuses.
“I just do not want to listen to that any more — we need to have to set options on the table,” she claimed. “And I’m glad that we’re going to be coming back again in January.”
Falck, the metropolis and other stakeholders mentioned they will proceed to collaborate.
“We’re functioning closely with the San Diego Hearth-Rescue Section and making investments that will deliver more paramedics to the process,” stated Jeff Lucia, Falck San Diego spokesperson.
Falck officers stated they have invested over $30 million in San Diego, which includes a fleet of new ambulances and products. The enterprise signed a 5 yr agreement with the city in 2021.
A year after moving to Bridge City, Texas, 8-year-old Samuel Kulovitz thought his life couldn’t get any worse. He had made no friends in the swampy oil refinery town and spent most of his time in his family’s mobile home. He missed Florida and playing on the beach there with other children.
But life did get worse. He hit puberty. For Kulovitz, who was assigned female at birth, “growing into being a young woman horrified me,” he said. “I kept crying and crying, and I didn’t know why I didn’t like it.”
Then, at age 11, Kulovitz started venturing onto social media. There, he came across a cosplayer on Tumblr who said he realized he was a transgender boy from the euphoria he felt while dressed as the hero of an online comic. Kulovitz was transfixed. “I kept asking myself, ‘Why do you want to look like him?’” he told Reuters. In the online community where Kulovitz spent more and more time, he adopted the pronouns “he” and “him,” and he liked it.
When his mother learned of his transgender identity, she was supportive and enrolled him in therapy. He was diagnosed at age 12 with gender dysphoria, the distress that comes from identifying as a gender different from the one assigned at birth.
Two and a half years later, Kulovitz started on the hormone testosterone. He was thrilled as he grew facial and chest hair, his voice dropped, and his menstrual periods stopped.
Still, his breasts were a constant source of distress, and his body ached from wearing a chest binder. “I always thought, ‘I wish I could get rid of them,’ ” Kulovitz said.
One day during his junior year of high school, Kulovitz, then 16, was scrolling on his phone when the TikTok account of a Miami surgeon who offered to “yeet the teets” of young transgender people popped up. In videos with hip-hop music playing in the background, Dr Sidhbh Gallagher provided detailed information about top surgery to remove or modify breasts and displayed photos of her satisfied gender-diverse patients, most of them young people, with shirts off to show the results of the doctor’s work. “Come to Miami to see me and the rest of the De Titty Committee,” she said in one of the videos.
Six months later, in June 2021, Kulovitz was in Miami with his mother, who gave consent for her son’s surgery and paid $10,000 out of pocket for it. He also had the letters of support Gallagher required from his therapist and doctor. When Kulovitz woke up after the procedure, “I felt euphoric,” he said. “I finally felt right in my body.”
A question of influence
Thousands of children who, like Kulovitz, were assigned female at birth have sought gender-affirming care in recent years. And for reasons not well-understood, they significantly outnumber those assigned male at birth who seek treatment.
As Reuters reported in October, a growing number of the children receiving care at the 100-plus gender clinics across the United States are opting for medical interventions – puberty-blocking drugs, hormones and, less often, surgery. And they are doing so even though strong scientific evidence of the long-term safety and efficacy of these treatments for children is scant.
That has led to a split among gender-care specialists: those who urge caution to ensure that only adolescents deemed well-suited to treatment after thorough evaluation receive it, and those who believe that delays in treatment unnecessarily prolong a child’s distress and put them at risk of self-harm.
The outsized proportion of adolescents seeking treatment to transition from female to male has sparked parallel concerns. Professionals in the gender-care community agree that treatment of all transgender children should be supportive and affirming. The question, for some, is whether peer groups and online media may be influencing some of these patients to pursue medical transition, with potentially irreversible side effects, at a time in their lives when their identities are often in flux.
Corey Basch, a professor of public health at William Paterson University in New Jersey who researches health communication and teens’ use of social media, said she fears that some adolescents are susceptible to making faulty self-diagnoses without adequate input from medical professionals. “Teens are so incredibly vulnerable to information overload and being pushed in one direction,” Basch said. “They could be lacking the analytical skills to question who is giving this advice and if their advice is valid.”
Adolescents assigned female at birth initiate transgender care 2.5 to 7.1 times more frequently than those assigned male at birth, according to the World Professional Association for Transgender Health (WPATH), a 4,000-member organization of medical, legal, academic and other professionals. Several clinics in the United States told Reuters that among their patients, the ratio was nearly 2-to-1, and similar phenomena have been documented in Europe, Canada and Australia.
Not all of these patients receive medical treatment. Their gender-affirming care may entail adopting a name and pronouns aligned with their gender identity. It may include counseling and therapy. But an increasing number are opting to take hormones and have top surgery.
In October, researchers at Vanderbilt University School of Medicine published a paper showing a 389{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} increase in gender-affirming chest surgeries performed nationally from 2016 to 2019 on patients under age 18. The total of 1,130 procedures during the period, nearly all of them for chest masculinization, represents a weighted estimate based on records from more than 2,000 U.S. medical facilities. Likewise, at least 776 chest masculinization surgeries were performed on patients ages 13 to 17 with a gender dysphoria diagnosis over the past three years, according to U.S. insurance claims analyzed for Reuters by health technology company Komodo Health Inc. This is probably an undercount because it does not include procedures paid for out of pocket.
The predominance of patients assigned female at birth is a reversal from the past. For years, when very few minors sought gender care, those assigned male at birth accounted for the majority. But about 15 years ago, that began to change as care became more accessible and the overall number of patients started climbing, according to studies and interviews with gender-care specialists.
For example, at Amsterdam University Medical Center’s gender clinic, a pioneer in adolescent gender care, the proportions flipped. From 1989 to 2005, 59{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of its adolescent patients were assigned male at birth, the Dutch clinic reported in a 2015 study published in the Journal of Sexual Medicine. Since 2016, about 75{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of the clinic’s patients have been youths who were assigned female at birth.
A diversity of identities
Advocates of transgender rights and clinicians who treat adolescents see nothing out of the ordinary in the trend. While transgender children face significant prejudice and threats of violence, they say, increasing social acceptance of transgender identity has encouraged more children to seek treatment. At the same time, this reasoning goes, society is generally less accepting of what it deems an effeminate boy than of a masculine girl, and the greater stigma that those assigned male at birth face may make them less likely to pursue treatment, reducing their share of the patient population.
These children may not necessarily identify as transgender, but more broadly as gender diverse. A growing list of terms reflects this diversity of gender identities: agender, nonbinary, gender fluid, polygender, demiboy and demigirl.
“Folks may feel freer and safer to express and take on a more diverse identity because the social conversation has been put out there.”
“There’s been an explosion in the gender-expansive model,” said Dr Michelle Forcier, a professor of pediatrics at Brown University’s Alpert Medical School who has specialized in the care of transgender and gender-diverse patients. “Folks may feel freer and safer to express and take on a more diverse identity because the social conversation has been put out there.” For these patients, she said, “the moral and ethical thing to do is to give them a list of options that might help them achieve their gender goals.”
But other gender-care providers and some parents are skeptical. In interviews with Reuters, they expressed worry that some adolescents assigned female at birth may be dealing with significant mental health issues in addition to questions about their gender identity, or may be seeking to transition as a refuge in a culture of internalized misogyny, body hatred and early sexualization of girls.
“Girls have a harder time with the physical and emotional changes that come with the onset of puberty,” said Dr Erica Anderson, a clinical psychologist, transgender woman and former board member of WPATH. “And I think there is an element of truth that males have it better in many quarters of society than females.”
For all children, experts say, adolescence is a search for identity, when they try on various personas, appearances and interests and move beyond family to seek validation from peers. Anderson, who treats transgender and gender-questioning youth in her private practice in Berkeley, California, said she’s concerned that medically transitioning has become the default choice for too many girls who are uncomfortable with their bodies, struggling to fit in socially or dealing with mental health issues.
“Kids do try things on and not everything sticks. They experiment,” she said. “I do not believe that we have an obligation to accept at face value everything a young person says to us.”
Anderson and other clinicians say the danger is that adolescents receive medical treatment, do not experience relief from their distress, and perhaps end up regretting the irreversible results of hormone therapy and top surgery. Treatment guidelines issued by WPATH and other medical groups rely heavily on research from the Netherlands that studied children who exhibited persistent gender dysphoria from an early age and who had no serious psychiatric issues before receiving puberty blockers, hormones or surgery.
The good and the bad
The role of peer influence and social media looms large in discussions about the gender imbalance among transgender youth patients.
In recent years, young transgender people have enthusiastically embraced social media to tell their stories. On platforms such as TikTok and Instagram, young people receiving gender treatment regularly share with followers – sometimes numbering in the tens of thousands – details about taking medications and having surgery. Their presence is augmented by doctors who use social media to communicate directly with potential patients.
Many patients, like Kulovitz, and doctors who treat them say social media can be a source of helpful advice and information for minors questioning their gender identity and can reduce their isolation by connecting them to others with similar experiences.
But some prominent clinicians also say that along with those benefits, social media may lead some youths to mistake mental health problems or uncertainty about their identity for gender dysphoria.
In its new Standards of Care, published in September, WPATH acknowledged for the first time that “social influence” may impact an adolescent’s gender identity. The organization recommends that youths undergo an in-depth evaluation in part so that clinicians “can discern between a person’s gender identity that is marked and sustained and an identity that might be socially influenced,” according to Dr Eli Coleman, director of the University of Minnesota Medical School’s Institute for Sexual and Gender Health who oversaw the update of WPATH’s guidelines.
Some patients may see others touting huge improvements in their quality of life after transitioning, and so they think, “‘I’m having these same problems, and transitioning to a different gender will help me feel better,’” said Dr Laura Edwards-Leeper, a clinical psychologist in Oregon who specializes in treating transgender children. She was a co-author of WPATH’s new Standards of Care for adolescents.
Parents of 40 gender-diverse children told Reuters they were concerned that their children came out only after they hit puberty, often at the same time as their friends and after their use of social media had increased. For many, their worries were compounded when clinicians swiftly affirmed their childrens’ transgender identities and recommended medical intervention without fully assessing whether other potential underlying causes of distress were present.
Kelly, a 43-year-old parent who asked that her full name not be used to protect her family’s privacy, told Reuters that her child was heavily into highly sexualized anime and transgender online forums when the 12-year-old started experimenting, seemingly overnight, with being a transgender boy. The child’s therapist encouraged medical intervention, Kelly said, but while Kelly supported social transition outside the home, she made it clear that her child would have to wait until she was 18 for hormones and top surgery.
After several years of living as a boy and using “he” and “him” pronouns, Kelly’s child, now 18, is back to using her female name, dressing in feminine clothing and using “she” and “her” pronouns. “We would have lost our daughter if we had followed what the therapist was telling us to do,” the mother said.
No definitive research has established a link between social media use and gender identity among youths. Still, gender-care experts say the possible influence of social media and peer groups highlights the necessity of comprehensive assessments before referring patients for medical treatment. The problem, they say, is that some clinics, facing a flood of patients, lack the mental health staff and patience needed to do such evaluations to determine whether a patient has persistent gender dysphoria and that medical treatment is in their best interests.
“These evaluations are more important than ever,” Edwards-Leeper said, because “many of these adolescents are learning about gender dysphoria for the first time online or from friends.”
In Finland, which was early to embrace gender care for minors, Dr Riittakerttu Kaltiala, chief psychiatrist at the Tampere University Hospital Department of Adolescent Psychiatry, noticed a few years ago that the profile of patients seeking to medically transition was shifting. Many showed no signs of gender dysphoria until puberty, were mostly assigned female at birth – reaching 90{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of patients by 2017 – and often belonged to similar social circles in school and online. In some cases, she said, patients described personal experiences with exactly the same details.
That these teens were possibly emulating each other didn’t bother Kaltiala. “That is perfectly normal” in adolescence, she told Reuters. What did bother her was that many of the teens had concluded quickly that they were transgender and viewed their identity as fixed, attempting to cut short the process of identity formation that typically lasts years.
She also encountered a handful of young patients who regretted medically transitioning. “They have said, ‘I was so sure that you could not have changed my mind. I was so confident that this is the way, but nevertheless I think it was a mistake,’ ” Kaltiala said. “I take that really seriously. It’s a horrible situation for everybody.”
Her concerns prompted a team of mental health professionals running Finland’s two adolescent gender clinics to ask the country’s national healthcare council to evaluate the evidence supporting youth gender care. In their request, they told the board that clinicians were under growing pressure to make increasingly complex medical decisions on treating transgender youths without enough scientific or expert guidance.
In 2020, the council concluded that “in light of available evidence, gender reassignment of minors is still an experimental practice.” Now, psychosocial support is the first-line treatment for most adolescents with gender dysphoria. Medical interventions are possible in Finland on a case-by-case basis if, after psychotherapy, the patient’s gender-related anxiety persists, personality development appears stable and no severe mental health disorders would complicate treatment.
Resisting the ‘fad’ narrative
Transgender advocates and some doctors reject the idea that social media and peer influence may play a role in the predominance of female-to-male transitions among adolescent patients. They say that it feeds a dangerous transphobic myth, and that opponents of gender care weaponize this false “fad” narrative to limit children’s access to treatment.
“One of the false narratives is that young people are being lured in and directed somehow against their will to become transgender, which is not at all the case,” said Dr Dan Karasic, professor emeritus of psychiatry at the University of California San Francisco and lead author of the mental health chapter in WPATH’s new Standards of Care.
He said opponents of children’s gender care erroneously conflate young patients undergoing medical treatment for persistent, longstanding gender dysphoria with “somebody who has a text chat with someone and is left with some confusion about who they are.”
Prisha Mosley is one of several people who told Reuters that, in hindsight, they think the medical professionals who helped them transition should have evaluated them more thoroughly and advised against medical treatments they now regret.
Starting in her early teens, Mosley, who was assigned female at birth, struggled with anorexia, anxiety and depression. She attempted suicide by drowning, and a sexual assault added to her trauma.
Isolated and miserable, she sought friends online, where she met a group of people on Tumblr who told her that if she hated her body, felt suicidal and didn’t fit in with her gender, she was transgender. “I wanted to do the treatment that would fix that,” Mosley, now 24, told Reuters.
Mosley socially transitioned, adopting a male name and pronouns and coming out to her mother with a PowerPoint presentation.
But that, as well as therapy and the help of a specialist in pediatric eating disorders, did not ease her distress. In January 2015, she was hospitalized after cutting her wrist with a knife, her medical records from Cone Health in Greensboro, North Carolina, show.
Later that year, Mosley said, a therapist diagnosed her with gender dysphoria after a single visit. By July, Mosley began treatment with testosterone under the care of her doctor at Cone. The hormone immediately boosted her energy, and her appetite improved. But her depression and suicidal thoughts persisted.
Cone Health spokesperson Doug Allred would not comment on Mosley’s case specifically. He said the health system’s gender-affirming care is based on established guidelines and provided to patients who undergo psychological assessment and have parental consent. “An individual’s perspective about their gender-affirming care can sometimes change,” he said.
Mosley’s mother, Christine Bourgeois-Mosley, said that she struggled for years to accept Mosley’s identity, but she consented to gender treatment because of her child’s persistent suicidal thoughts. Mosley’s therapist, Shana Gordon, and her physician at Cone, Dr Martha Perry, assured the family that it was the right thing to do, both Mosley and her mother said. Gordon and Perry declined to comment on Mosley’s care.
When Mosley turned 18, she had surgery to remove her breasts. Her mother objected to the surgery, but accompanied Mosley anyway. “What was I going to do, let her go by herself?” Bourgeois-Mosley said.
Mosley said the physical transition did not alleviate her depression; she continued to cut herself. Her mental health began to improve only after several years of behavioral therapy. At 22, she stopped taking testosterone and determined that she regretted transitioning.
“I decided that I didn’t want to be a woman before I had ever even experienced being a woman,” said Mosley, who is now studying psychology at a community college in Michigan. “Now I feel like I will never entirely know.”
Mosley suffers from painful vaginal atrophy, marked by dryness and inflammation of the vaginal walls, a common side effect of testosterone that she said she didn’t fully understand when her doctor warned her about it. She is undergoing laser treatments to remove the facial and body hair brought on by testosterone, and she hopes to be cleared for breast reconstruction.
Mosley said she wishes her doctors had focused more on her mental health instead of endorsing her desire to change her body. “I just took the cure that was handed to me,” she said, “and I ruined my life.”
The surgical route
The main components of medical treatment for transgender youths are puberty blockers, hormones and surgery. Clinicians say many adolescents seeking to transition show up after the onset of puberty, making puberty blockers impractical. Treatment for those assigned female at birth may start with testosterone. Over time, the hormone can cause male-pattern baldness, high blood pressure, an enlarged clitoris and the vaginal atrophy that plagues Mosley. The long-term effects on fertility are unclear.
Some of these young patients opt for surgery. When they do, it’s almost always top surgery. A common bottom surgery they would have – phalloplasty to create a penis – is expensive and has a high rate of complications. Many hospitals do not perform genital surgeries on patients under 18.
Top surgery, by comparison, is less complicated and less risky. Surgeons warn patients about scarring, loss of lactation, possible loss of sensation in the nipples, along with routine post-operative risks like slow wound healing. Prices typically range from $5,000 to $30,000 or more. Some insurers cover the procedure for gender dysphoria patients as young as 13.
Top surgery is a particular target for opponents of gender care, who object to allowing minors to undergo life-altering procedures at such a young age. Some children’s hospitals and doctors providing top surgery have reported being harassed and threatened online for treating adolescents.
Within the gender-care community, top surgery is considered a safe and effective way to alleviate a major source of anguish in transgender boys.
After receiving an “overwhelming number of violent threats” in August, Dr Scott Mosser of the Gender Confirmation Center in San Francisco announced he had paused accepting new adolescent patients for gender surgery. In a statement posted on his website, Mosser said: “We are profoundly disturbed by the extent to which misinformation, prejudice and fanaticism threaten trans, nonbinary and gender expansive people’s access to life-saving care.”
Within the gender-care community, top surgery is considered a safe and effective way to alleviate a major source of anguish in transgender boys. WPATH’s new guidelines say that chest dysphoria is associated with higher levels of anxiety and depression in patients assigned female at birth, and that testosterone does little to alleviate this distress. Without specifying a recommended minimum age, the organization says top surgery “can be considered in minors when clinically and developmentally appropriate.”
Floor Hurlbert was a middle-school student in Connecticut when, around the start of puberty, they began to suffer from severe chest dysphoria. Pained by their appearance, Hurlbert avoided taking showers and removed a full-length mirror from their room. Wearing a chest binder was uncomfortable and didn’t ease their distress. “I knew people were looking at me and perceiving me in a way I didn’t like,” Hurlbert said.
Hurlbert wasn’t interested in taking testosterone. They only wanted top surgery, and they got it soon after turning 18. “It was like a huge source of my mental health issues were not there anymore,” said Hurlbert, now a 19-year-old college student. “I could feel happy about myself and how I looked.”
Research on long-term outcomes for patients who undergo top surgery as minors is limited. In its guidelines, WPATH cites two small studies published in recent years that it says “demonstrated good surgical outcomes, satisfaction with results, and minimal regret during the study monitoring period.” Both studies followed up with patients an average of about 1.5 years after surgery.
A menu of options
Amid the debate over whether social media is influencing adolescents to seek top surgeries, some surgeons are using online platforms to tap rising demand for the procedures.
Top Surgery Specialists of New York City and Los Angeles has Instagram accounts that feature photos of young people proudly displaying their scars after top surgery.
Dr Tony Mangubat, a Seattle plastic surgeon who has more than 200,000 followers on TikTok @TikDocTony, often tags his posts with the hashtag “#teetusdeletus.” In his videos, he answers questions like “What is the perfect age to have top surgery?” (“My youngest patient was 15,” Mangubat replied) and “Hey Doc, how old do I have to be to start T,” short for testosterone. (“You start T, really, when you’re ready,” Mangubat responded, and advised patients to talk to their doctors).
Top Surgery Specialists and Mangubat did not respond to requests for comment.
Gallagher, the doctor who performed Kulovitz’s top surgery, posts bare-chested selfies from her patients – who often refer to themselves as “Gallagher guys” – frolicking on sun-drenched beaches. She also posts images of parents standing in the lobby of her Miami office next to their children, who wear unbuttoned “nip-reveal shirts” that show their red incision scars. “Supportive moms are the best!” Gallagher writes in photo captions.
SHOWING RESULTS: Miami surgeon Sidhbh Gallagher posted on Instagram this photo of herself with Samuel Kulovitz and his mother, Tisha Kulovitz, after the surgeon performed Samuel’s top surgery.
Gallagher describes to her 273,000 TikTok followers the options she offers for “designer” chests. Top surgery can include torso “masculoplasty” to smooth out feminine curves. For the nonbinary, Gallagher can remove the nipples altogether: “No Nips, No problem,” as one post’s text display puts it. And for the gender fluid, she offers “non-flat” surgery, leaving enough breast tissue so that on some days patients can have a “perky breast” with cleavage and on other days they can bind their breasts.
TikTok did not respond to requests for comment. A spokesperson for Instagram parent Meta Platforms Inc said that doctors who post about medical procedures involving minors wouldn’t necessarily violate the platform’s rules, but that paying for ads directed at minors is prohibited.
Half a dozen of Gallagher’s patients who were minors when they got top surgery, including Kulovitz, told Reuters they were very pleased with the results. They also said they appreciated how Gallagher publicly champions their right to a body that aligns with their gender identity.
Gallagher’s marketing tactics have caught the attention of organizations critical of gender-affirming care for minors. In February, five of these groups, made up of parents, medical professionals and people who have detransitioned, filed a complaint with the Federal Trade Commission, asking the agency to investigate Gallagher over the way she communicates with young people on social media. The complaint alleges that Gallagher and her medical practice are “engaged in unfair, false and deceptive practices in the aggressive advertising and marketing to minors of their plastic surgery services, namely mastectomies of healthy female breasts, as proven safe, effective and medically necessary.” One of the groups’ members said she was alarmed when her child, who was following Gallagher on social media, told her about wanting surgery by the doctor.
REACHING OUT: Gallagher has 273,000 followers on TikTok, where she frequently posts information about top surgery and the various options she offers to young transgender people for “designer” chests.
Two lawyers filed a similar complaint earlier this year with the Florida Attorney General’s Office alleging that Gallagher is improperly marketing surgery to teens on TikTok and Instagram, in particular to “children with mental health disorders.”
In a statement to Reuters, Gallagher said that nine months after the FTC complaint was filed, “there is, to our knowledge, no investigation by the FTC” and that the “obvious aim of these opposing groups is to oppress, silence and attack gender-affirming care and those that provide it.” She added that the mission of her social media was to “amplify transgender voices, celebrate transgender lives and, most importantly, to provide education that empowers our patients to navigate the complex process of surgical transition.”
The FTC and the Florida attorney general’s office did not respond to requests for comment.
More generally, Florida is among several conservative-run states opposed to gender-affirming care for minors that have sought to limit access to treatment. In early November, two Florida medical boards approved draft rules to ban puberty blockers, hormones and gender-affirming surgeries for minors. Patients already in treatment and children enrolled in clinical trials could continue to receive care. The rules are scheduled to take effect in the coming weeks.
It’s not unusual for plastic surgeons to share information with prospective patients on social media. But some gender-care specialists say that using graphic patient photos and lighthearted videos aimed at minors online glosses over potential complications and life-altering consequences.
“It seems like they’re almost trying to recruit people based on really flashy videos that minimize the risks,” said Dr Marci Bowers, a transgender woman who is a gender surgeon and president of WPATH. “For those who are genuinely concerned that people are being swept in by this ‘social contagion,’ these kinds of videos are not helpful,” she said. “I wish we could police them, but I just don’t know of any good way to do that other than to appeal to good taste.”
Bowers said that she doesn’t advertise on social media and that WPATH’s ethics committee is examining how to discourage improper marketing practices.
‘A beautiful feeling’
When the then-7-year-old Samuel Kulovitz moved with his mother and stepfather to Bridge City from West Palm Beach, Florida, he found himself in a “sad and depressing” flood-prone Gulf Coast town with no sidewalks and few places to swim, often cloaked in the sulfurous emissions of ubiquitous oil refineries. The brainy child, who struggles with sensory and auditory processing issues, was quickly ostracized, a frequent target of teasing and bullying. Outside school, he spent his time in the family’s mobile home, reading, playing video games and hanging out with his mom.
The panic of puberty, a training bra and menstrual periods only worsened his isolation – until he started exploring social media. There, he said, he finally realized the main source of his unhappiness: He was transgender.
Inspired by the cosplayer he found on Tumblr, he walked to Walgreens one day, bought a gift card and ordered a chest binder online. “The first time I put it on, it was a beautiful feeling,” he said. “It was the most euphoric I had ever been in my life.”
He kept his newfound gender identity from his parents, fearful of how they would react. Then one day, while riding with his mother in her car, he passed out. Tisha Kulovitz rushed him to a local hospital, where doctors told her that her 12-year-old was malnourished from an eating disorder and had been binding his breasts.
At first, “I was completely blindsided,” Tisha said. “I think we initially even blamed the internet.”
But after she began doing her own online research on transgender children, she concluded it was important to support her child. She enrolled him in gender therapy, found him a psychiatrist to help treat his eating disorder, depression and sensory and auditory processing issues and took him to a transgender support group located out of town, driving him the 30 miles each way once a month. In the summer, he attended a gender-inclusive camp where everyone was encouraged to experiment with any identity they wanted. “My mom was my hero through all of this,” said Kulovitz. “I wouldn’t be alive without her.”
After a diagnosis of gender dysphoria and more than two years of therapy, Kulovitz went on testosterone at age 14. The masculinizing effects gave him a big confidence boost.
Kulovitz was still the only transgender student he knew of when, as a high-school freshman, he felt emboldened enough to start the school’s first LGBTQ club. At first, nobody came. But over time, the club had grown to include 30 students, half of whom identified as transgender, nonbinary or gender fluid. “I was like, ‘Wow so great you are here, I’m glad y’all feel comfortable,’ ” he said.
As a junior in high school, he discovered Dr Gallagher on social media. Two months later, for Valentine’s Day, his mother gave him a virtual consultation with the doctor, scheduled during his school lunch break. Gallagher “was super cool and affirming,” Kulovitz said. “She put all my anxieties to rest.”
His parents were on board. To pay for the procedure, his mother worked overtime at her job and chipped in earnings from her vintage-clothing store on Etsy. Kulovitz said that he is “super proud” of how the surgery made him feel. “If I hadn’t gotten it, I don’t think my mental health would be where it is,” he said.
Today, Kulovitz identifies as a transgender man who is gay. In August, he started college on a full scholarship in a small Texas town about a four-hour drive from Bridge City. The university doesn’t offer LGBTQ housing, so Kulovitz, who changed his gender marker to male on his birth certificate when he transitioned, shares a dorm room with a cisgender male football player.
He is pleased to be living in a community that includes more LGBTQ people, and has made fast friends with a cisgender young woman with whom he goes shopping for vintage clothes. For now, he has no interest in dating or pursuing a romantic relationship – and no interest in bottom surgery. “It’s an intense procedure, and at this point in time I don’t think it’s right for me,” he said.
He also has dialed back on social media after deciding he was spending too much time scrolling on his phone. “I hated how it made me feel,” he said. “It was like quitting a drug.”
Last January, on his 18th birthday, he deleted TikTok from his phone.
Do you have an experience with gender-affirming care to share as a patient, family member or medical provider? Share it with Reuters.
Youth in Transition
By Michelle Conlin, Robin Respaut and Chad Terhune