Teresa Adams House unveiled for families seeking medical attention

Teresa Adams House unveiled for families seeking medical attention

QUINCY (WGEM) – The community collected on Tuesday for a ribbon reducing ceremony, unveiling the new Teresa Adams Household.

Officers stated the more than $2 million up grade was needed for the reason that the primary Quincy Hospitality Property was not designed for individuals with disabilities.

Karen Dieckhoff is a single of the founders of the first Quincy Hospitality Household. She sat on the board in 1993 and served plan what the to start with dwelling would embody.

At the unveiling of the most recent household, she gets to mirror on the development built in three decades.

“We dreamed, just dreamed of owning a position like this for this prolonged and so this day is just a wonderful end result of many, many, many men and women operating,” said Dieckhoff.

The Teresa Adams Home, which was constructed on land donated by Blessing Health and fitness, is named soon after the Quincy indigenous who officers reported was a symbol of residence and ease and comfort in the Tri-States’ healthcare technique.

Her spouse, Kent Adams, said she would be thrilled about the new facility.

“It’s just amazing,” stated Adams.

The new Teresa Adams Property delivers much more handicap accessibility prospects with company getting ready to roll their wheelchair straight into the creating alternatively of acquiring to navigate techniques.

The original hospitality property, positioned on Oak Avenue, has stairs that all guests are pressured to acquire to enter.

The new making features two wheelchair entrances.

All eight rooms in the facility are wheelchair available, with two queen beds in just about every and roll-in showers.

Teresa Adams Home Coordinator Becky Albert claimed getting a spot like this is necessary for all those obtaining clinical remedy, and their families, in the place.

“If you at any time have had a cherished just one which is been under treatment and you require a place to be capable to remain just to have that nap, or have a shower, have a minimal little bit of some thing to try to eat, you know that it makes these kinds of a difference for them as caregivers to be equipped to go again and handle whatsoever they will need to for that loved 1,” Albert mentioned.

Teresa Adams Dwelling team explained there are no age limits on who can stay at the home, but they are searching for some a lot more volunteers just before they allow lodging at the house after Jan. 1.

The Teresa Adams Home will provide all those obtaining inpatient and outpatient treatment at blessing medical center or any clinical doctor’s or dentist’s office environment in the surrounding location.

The workforce claimed they’ll also serve people traveling to nearby nursing properties, funerals or people traveling to the Illinois Veterans’ Dwelling.

The price is $40 for each evening, but grants are accessible to individuals who are not able to spend.

For extra information about the residences or to donate, go to right here.

Ground Strategy of Teresa Adams House

Teresa Adams House Floorplan
Teresa Adams Residence Floorplan(Blessing Overall health Process)

A lot more about the home’s namesake, Teresa Adams

https://www.youtube.com/enjoy?v=Ffa7-I9JRcg

Copyright 2022 WGEM. All legal rights reserved.

A digital application and augmented physician rounds reduce postoperative pain and opioid consumption after primary total knee replacement (TKR): a randomized clinical trial | BMC Medicine

A digital application and augmented physician rounds reduce postoperative pain and opioid consumption after primary total knee replacement (TKR): a randomized clinical trial | BMC Medicine
  • Vowles KE, McEntee ML, Julnes PS, Frohe T, Ney JP, van der Goes DN. Rates of opioid misuse, abuse, and addiction in chronic pain: a systematic review and data synthesis. Pain. 2015;156(4):569–76.

    Article 
    PubMed 

    Google Scholar
     

  • Makary MA, Overton HN, Wang P. Overprescribing is major contributor to opioid crisis. BMJ. 2017;359:j4792.

    Article 
    PubMed 

    Google Scholar
     

  • Hirschfeld DJ. Trump Declares Opioid Crisis a ‘Health Emergency’ Requests no Funds The New York Times; 2017.


    Google Scholar
     

  • Hollmann MW, Rathmell JP, Lirk P. Optimal postoperative pain management: redefining the role for opioids. Lancet. 2019;393(10180):1483–5.

    Article 
    PubMed 

    Google Scholar
     

  • Silva BM, Rodrigues JJ, de la Torre DI, Lopez-Coronado M, Saleem K. Mobile-health: A review of current state in 2015. J Biomed Inform. 2015;56:265–72.

    Article 
    PubMed 

    Google Scholar
     

  • Bhavnani SP, Narula J, Sengupta PP. Mobile technology and the digitization of healthcare. Eur Heart J. 2016;37(18):1428–38.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Brummett CM, Waljee JF, Goesling J, Moser S, Lin P, Englesbe MJ, et al. New Persistent Opioid Use After Minor and Major Surgical Procedures in US Adults. JAMA Surg. 2017;152(6):e170504.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Hamnvik OR, Alford DP, Ryan CT, Hardesty IT, Drazen JM. NEJM Knowledge+ Pain Management and Opioids – A New Adaptive Learning Module. N Engl J Med. 2019;380(16):1576–7.

    Article 
    PubMed 

    Google Scholar
     

  • Babu KM, Brent J, Juurlink DN. Prevention of Opioid Overdose. N Engl J Med. 2019;380(23):2246–55.

    Article 
    PubMed 

    Google Scholar
     

  • Colloca L, Barsky AJ. Placebo and Nocebo Effects. N Engl J Med. 2020;382(6):554–61.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Benedetti F. Placebo analgesia. Neurol Sci. 2006;27(2):100–2.

    Article 

    Google Scholar
     

  • Colloca L, Lopiano L, Lanotte M, Benedetti F. Overt versus covert treatment for pain, anxiety, and Parkinson’s disease. Lancet Neurol. 2004;3(11):679–84.

    Article 
    PubMed 

    Google Scholar
     

  • Hack TF, Degner LF, Parker PA, Team SC. The communication goals and needs of cancer patients: a review. Psychooncology. 2005;14(10):831–47.

    Article 
    PubMed 

    Google Scholar
     

  • Del Re AC, Fluckiger C, Horvath AO, Symonds D, Wampold BE. Therapist effects in the therapeutic alliance-outcome relationship: a restricted-maximum likelihood meta-analysis. Clin Psychol Rev. 2012;32(7):642–9.

    Article 
    PubMed 

    Google Scholar
     

  • Epstein R, Street RL. Patient-centered communication in cancer care: promoting healing and reducing suffering: National Cancer Institute. Bethesda: US Department of Health and Human Services, National Institutes of Health; 2007.


    Google Scholar
     

  • Baker PN, van der Meulen JH, Lewsey J, Gregg PJ. The role of pain and function in determining patient satisfaction after total knee replacement. Data from the National Joint Registry for England and Wales. J Bone Joint Surg Br. 2007;89(7):893–900.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • World Health O. ICD-10 : international statistical classification of diseases and related health problems : tenth revision. 2nd ed. Geneva: World Health Organization; 2004.


    Google Scholar
     

  • Breivik H, Borchgrevink PC, Allen SM, Rosseland LA, Romundstad L, Hals EK, et al. Assessment of pain. Br J Anaesth. 2008;101(1):17–24.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Younger J, Gandhi V, Hubbard E, Mackey S. Development of the Stanford Expectations of Treatment Scale (SETS): a tool for measuring patient outcome expectancy in clinical trials. Clin Trials. 2012;9(6):767–76.

    Article 
    PubMed 

    Google Scholar
     

  • Faul F, Erdfelder E, Buchner A, Lang AG. Statistical power analyses using G*Power 3.1: tests for correlation and regression analyses. Behav Res Methods. 2009;41(4):1149–60.

    Article 
    PubMed 

    Google Scholar
     

  • Booth RG, Strudwick G, McBride S, O’Connor S, Solano López AL. How the nursing profession should adapt for a digital future. BMJ. 2021;373:n1190.

    Article 
    PubMed Central 

    Google Scholar
     

  • Fairbrother P, Ure J, Hanley J, McCloughan L, Denvir M, Sheikh A, et al. Telemonitoring for chronic heart failure: the views of patients and healthcare professionals – a qualitative study. J Clin Nurs. 2014;23(1-2):132–44.

    Article 
    PubMed 

    Google Scholar
     

  • Barello S, Triberti S, Graffigna G, Libreri C, Serino S, Hibbard J, et al. eHealth for Patient Engagement: A Systematic Review. Front Psychol. 2015;6:2013.

    PubMed 

    Google Scholar
     

  • Eaton L, Walsh C, Magnuson T, Schweitzer M, Lidor A, Nguyen H, et al. On-line bariatric surgery information session as effective as in-person information session. Surg Obes Relat Dis. 2012;8(2):225–9.

    Article 
    PubMed 

    Google Scholar
     

  • Heikkinen K, Leino-Kilpi H, Vahlberg T, Salanterä S. Ambulatory orthopaedic surgery patients’ symptoms with two different patient education methods. Int J Orthop Trauma Nurs. 2012;16(1):13–20.

    Article 

    Google Scholar
     

  • Matthew DA. The use of a computer website prior to scheduled surgery (a pilot study): impact on patient information, acquisition, anxiety level, and overall satisfaction with anesthesia care. AANA J. 2005;73(1):29.


    Google Scholar
     

  • D’Haese PF, Pallavaram S, Li R, Remple MS, Kao C, Neimat JS, et al. CranialVault and its CRAVE tools: a clinical computer assistance system for deep brain stimulation (DBS) therapy. Med Image Anal. 2012;16(3):744–53.

    Article 
    PubMed 

    Google Scholar
     

  • de Visser H, Watson MO, Salvado O, Passenger JD. Progress in virtual reality simulators for surgical training and certification. Med J Aust. 2011;194(4):S38–40.

    PubMed 

    Google Scholar
     

  • Neuprez A, Neuprez AH, Kaux J-F, Kurth W, Daniel C, Thirion T, et al. Early Clinically Relevant Improvement in Quality of Life and Clinical Outcomes 1 Year Postsurgery in Patients with Knee and Hip Joint Arthroplasties. Cartilage. 2018;9(2):127–39.

    Article 
    PubMed 

    Google Scholar
     

  • Klimek M, Büchele G, Rehm M, Beyersmann J, Günther KP, Brenner H, et al. Long-term mortality of patients with osteoarthritis after joint replacement: Prognostic value of pre-and postoperative pain and function. Athritis Care Res. 2021;0(0):1–7. https://doi.org/10.1002/acr.24808.

    Article 
    CAS 

    Google Scholar
     

  • Kaptchuk TJ, Miller FG. Placebo Effects in Medicine. N Engl J Med. 2015;373(1):8–9.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Amanzio M, Pollo A, Maggi G, Benedetti F. Response variability to analgesics: a role for non-specific activation of endogenous opioids. Pain. 2001;90(3):205–15.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Bingel U, Wanigasekera V, Wiech K, Ni Mhuircheartaigh R, Lee MC, Ploner M, et al. The effect of treatment expectation on drug efficacy: imaging the analgesic benefit of the opioid remifentanil. Sci Transl Med. 2011;3(70):70ra14. https://doi.org/10.1126/scitranslmed.3001244.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Kam-Hansen S, Jakubowski M, Kelley JM, Kirsch I, Hoaglin DC, Kaptchuk TJ, et al. Altered placebo and drug labeling changes the outcome of episodic migraine attacks. Sci Transl Med. 2014;6(218ra5).

  • Levine JD, Gordon NC. Influence of the method of drug administration on analgesic response. Nature. 1984;312(5996):755–6.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Moore RA, Cai N, Skljarevski V, Tolle TR. Duloxetine use in chronic painful conditions–individual patient data responder analysis. Eur J Pain. 2014;18(1):67–75.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Rief W, Nestoriuc Y, Weiss S, Welzel E, Barsky AJ, Hofmann SG. Meta-analysis of the placebo response in antidepressant trials. J Affect Disord. 2009;118(1-3):1–8.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Colloca L. The Placebo Effect in Pain Therapies. Annu Rev Pharmacol Toxicol. 2019;59:191–211.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Elsenbruch S, Kotsis V, Benson S, Rosenberger C, Reidick D, Schedlowski M, et al. Neural mechanisms mediating the effects of expectation in visceral placebo analgesia: an fMRI study in healthy placebo responders and nonresponders. Pain. 2012;153(2):382–90.

    Article 
    PubMed 

    Google Scholar
     

  • Kaptchuk TJ, Friedlander E, Kelley JM, Sanchez MN, Kokkotou E, Singer JP, et al. Placebos without deception: a randomized controlled trial in irritable bowel syndrome. PLoS One. 2010;5(12):e15591.

    Article 
    PubMed 
    PubMed Central 
    CAS 

    Google Scholar
     

  • Timmers T, Janssen L, Kool RB, Kremer JA. Educating Patients by Providing Timely Information Using Smartphone and Tablet Apps: Systematic Review. J Med Internet Res. 2020;22(4):e17342.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Klinger R, Colloca L, Bingel U, Flor H. Placebo analgesia: clinical applications. Pain. 2014;155(6):1055–8.

    Article 
    PubMed 

    Google Scholar
     

  • Colloca L, Jonas WB, Killen J, Miller FG, Shurtleff D. Reevaluating the placebo effect in medical practice. Z Psychol. 2014;222(3):124–7.

    PubMed 
    PubMed Central 

    Google Scholar
     

  • Benedetti F. Placebo Effects. Understanding the mechanisms in health and disease. Oxford: Oxford University Press; 2014.

    Book 

    Google Scholar
     

  • Colloca L, Miller FG. Harnessing the placebo effect: the need for translational research. Philos Trans R Soc Lond B Biol Sci. 2011;366(1572):1922–30.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Enck P, Bingel U, Schedlowski M, Rief W. The placebo response in medicine: minimize, maximize or personalize? Nat Rev Drug Discov. 2013;12(3):191–204.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Miller FG, Colloca L. The legitimacy of placebo treatments in clinical practice: evidence and ethics. Am J Bioeth. 2009;9(12):39–47.

    Article 
    PubMed 

    Google Scholar
     

  • Schedlowski M, Enck P, Rief W, Bingel U. Neuro-Bio-Behavioral Mechanisms of Placebo and Nocebo Responses: Implications for Clinical Trials and Clinical Practice. Pharmacol Rev. 2015;67(3):697–730.

    Article 
    PubMed 

    Google Scholar
     

  • Crum A, Zuckerman B. Changing Mindsets to Enhance Treatment Effectiveness. JAMA. 2017;317(20):2063–4.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Price DD, Finniss DG, Benedetti F. A comprehensive review of the placebo effect: recent advances and current thought. Annu Rev Psychol. 2008;59:565–90.

    Article 
    PubMed 

    Google Scholar
     

  • Finniss DG, Benedetti F. Mechanisms of the placebo response and their impact on clinical trials and clinical practice. Pain. 2005;114(1-2):3–6.

    Article 
    PubMed 

    Google Scholar
     

  • Colloca L, Finniss D. Nocebo effects, patient-clinician communication, and therapeutic outcomes. JAMA. 2012;307(6):567–8.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Colloca L. How do placebo effects and patient-clinician relationships influence behaviors and clinical outcomes? Pain Rep. 2019;4(3):e758.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Ashton-James CE, Forouzanfar T, Costa D. The contribution of patients’ presurgery perceptions of surgeon attributes to the experience of trust and pain during third molar surgery. Pain Rep. 2019;4(3):e754.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Henry SG, Matthias MS. Patient-Clinician Communication About Pain: A Conceptual Model and Narrative Review. Pain Med. 2018;19(11):2154–65.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Volkow ND, Collins FS. The Role of Science in Addressing the Opioid Crisis. N Engl J Med. 2017;377(4):391–4.

    Article 
    PubMed 

    Google Scholar
     

  • White AG, Birnbaum HG, Mareva MN, Daher M, Vallow S, Schein J, et al. Direct costs of opioid abuse in an insured population in the United States. J Manag Care Pharm. 2005;11(6):469–79.

    Article 
    PubMed 

    Google Scholar
     

  • Wolford ML, Palso K, Bercovitz A. Hospitalization for total hip replacement among inpatients aged 45 and over: United States, 2000-1010: US Department of Health and Human Services, Centers for Disease Control and …; 2015.

  • Arthrose K-IR. Gesundheitsberichterstattung des Bundes. Berlin: RKI; 2013.


    Google Scholar
     

  • Darley JM, Fazio RH. Expectancy confirmation processes arising in the social interaction sequence. Am Psychol. 1980;35(10):867–81.

    Article 

    Google Scholar
     

  • Von Korff M, Ormel J, Keefe FJ, Dworkin SF. Grading the severity of chronic pain. Pain. 1992;50(2):133–49.

    Article 

    Google Scholar
     

  • Klinger R, Krug F, Goßmann M, Damzog U, Dahme B, Bruch H-P. Das perioperative Schmerz- und Befindlichkeitsinventar: Ein Fragebogen zur Erfassung der perioperativen Lebensqualität. Der Schmerz. 1999;13:86.


    Google Scholar
     

  • Flor H, Rudy TE, Birbaumer N, Streit B, Schugens MM. The applicability of the West Haven-Yale multidimensional pain inventory in German-speaking countries. Data on the reliability and validity of the MPI-D. Schmerz. 1990;4(2):82–7.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Lowe B, Wahl I, Rose M, Spitzer C, Glaesmer H, Wingenfeld K, et al. A 4-item measure of depression and anxiety: validation and standardization of the Patient Health Questionnaire-4 (PHQ-4) in the general population. J Affect Disord. 2010;122(1-2):86–95.

    Article 
    PubMed 

    Google Scholar
     

  • Lequesne MG. The algofunctional indices for hip and knee osteoarthritis. J Rheumatol. 1997;24(4):779–81.

    PubMed 
    CAS 

    Google Scholar
     

  • Faul F, Erdfelder E, Lang AG, Buchner A. G*Power 3: a flexible statistical power analysis program for the social, behavioral, and biomedical sciences. Behav Res Methods. 2007;39(2):175–91.

    Article 
    PubMed 

    Google Scholar
     

  • Beswick AD, Wylde V, Gooberman-Hill R, Blom A, Dieppe P. What proportion of patients report long-term pain after total hip or knee replacement for osteoarthritis? A systematic review of prospective studies in unselected patients. BMJ Open. 2012;2(1):e000435.

    Article 
    PubMed 
    PubMed Central 

    Google Scholar
     

  • Kim SS, Kaplowitz S, Johnston MV. The effects of physician empathy on patient satisfaction and compliance. Eval Health Prof. 2004;27(3):237–51.

    Article 
    PubMed 
    CAS 

    Google Scholar
     

  • Sim I. Mobile Devices and Health. N Engl J Med. 2019;381(10):956–68.

    Article 
    PubMed 

    Google Scholar
     

  • Bortz J, Schuster C. Statistik für Human-und Sozialwissenschaftler: Limitierte Sonderausgabe. Berlin: Springer-Verlag; 2011.


    Google Scholar

     

  • Radical new therapy for Parkinson’s will use stem cell transplants | Parkinson’s disease

    Radical new therapy for Parkinson’s will use stem cell transplants | Parkinson’s disease

    Early next year, a radical new therapy for Parkinson’s sickness involving tissue transplants will acquire its very first trial with clients – together with a team from the British isles.

    Stem cells developed in the laboratory and remodeled into nerve cells will be made use of to replace all those wrecked by the disorder. It is hoped that these will end the spread of debilitating indications.

    “It has taken a lengthy time to get to this stage but hopefully effects from these trials will imply that, in a several decades, we could be in a position to offer tissue transplants as regular treatment options for Parkinson’s,” reported Prof Roger Barker, of Cambridge College. “It is unquestionably a promising technique.”

    In the British isles, about 145,000 people today are living with Parkinson’s and about 18,000 new scenarios are diagnosed just about every year. The illness is activated when nerve cells that source dopamine to the mind commence to die due to a mix of genetic and environmental factors.

    Dopamine will help a person handle motion. When materials drop, the final result is shaking, stiffness, depression and other signs that can end with clients utilizing a wheelchair or getting mattress-ridden. The disease’s development can be slowed by the drug L-dopa, which replaces some of the shed function of dopamine cells. Treatments turn out to be much less effective about the decades. Scientists have been browsing for a long time for new approaches.

    One particular thought has been to swap dying dopamine cells with unaffected variations, which has been experimented with by several centres throughout the earth. This in the beginning associated employing tissue from aborted foetuses that experienced been donated for health-related exploration.

    Foetal tissue includes dopamine-producing cells that can supply the missing chemical, despite the fact that at the very least 6 or 7 foetuses are required to deliver sufficient content for a person individual. In trials in Europe, these cells ended up injected into patients’ brains with encouraging success. Other trials in the US observed these types of remedies much much less productive, having said that.

    The use of tissue from aborted foetuses was opposed by lots of on spiritual grounds. It was also tough to supply sufficient supplies for widely made use of treatment options. Having said that, Barker and his staff at Cambridge – working in collaboration with scientists led by Prof Malin Parmar at Lund College in Sweden – have made a technological know-how that avoids these challenges.

    The new strategy uses stem cells, from which all cells with specialised capabilities are generated in the human system. These stem cells can be developed in laboratory cultures. Even improved, researchers have figured out how to rework them into dopamine cells. These will sort the core of the transplants that will be carried out next thirty day period.

    “We now know that placing dopamine cells in the brain will operate and the course of action is secure,” explained Barker. “There is no longer a problem about supply of enough tissue due to the fact we can manufacture these cells in big numbers in the laboratory. The value is relatively low. A offer of dopamine cells – built out of stem cells – has turn out to be standardised products and we really do not have any contaminating cells, which you can get with foetal tissue.

    “That means that we are now at a stage where by we can use stem -mobile transplants as therapies for Parkinson’s sufferers, while it will take various years right before we will know that these perform and can be applied as normal treatment options for Parkinson’s disorder.”

    The trials will start out in the up coming couple months and will proceed around the upcoming year. There will be 4 individuals from Sweden and four participants from the United kingdom. “The cells are in a freezer and prepared to go in,” stated Barker. “The transplants will be carried out in Sweden for the reason that they have the devices to carry this out. This will be adopted up in excess of the yr with even more trials.”

    Experts assume that their trials will take at minimum two yrs to total. They will be followed by very careful scrutiny of the outcomes and of any aspect-results. Offered that these progress satisfactorily, tissue transplants could be completely ready for wider use in about five yrs.

    “Younger sufferers will advantage most from this remedy,” reported Barker. “It is heading to be a a person-off treatment, so that the complications that you get with continual prescription drugs will not come up, though people innovative therapies involving deep-mind stimulation will not be wanted so frequently.”

    FDA approved a 1st-of-its-kind treatment made from human poop. What does it do?

    FDA approved a 1st-of-its-kind treatment made from human poop. What does it do?

    For the to start with time, the Meals and Drug Administration (Food and drug administration) has accredited a therapy which is manufactured employing donated human poop, the company declared (opens in new tab) Wednesday (Nov. 30). The treatment method, termed Rebyota, includes intestine micro organism collected from the stool of healthful human donors and is permitted for the prevention of a perhaps everyday living-threatening bacterial an infection. 

    By administering the liquid cure into a patient’s rectum through a tube, health professionals can aid restore harmony to the patient’s gut microbiome, the community of microbes dwelling in the decrease digestive tract. 

    Long Covid costs patients an average $9,000 a year in medical expenses

    Long Covid costs patients an average ,000 a year in medical expenses

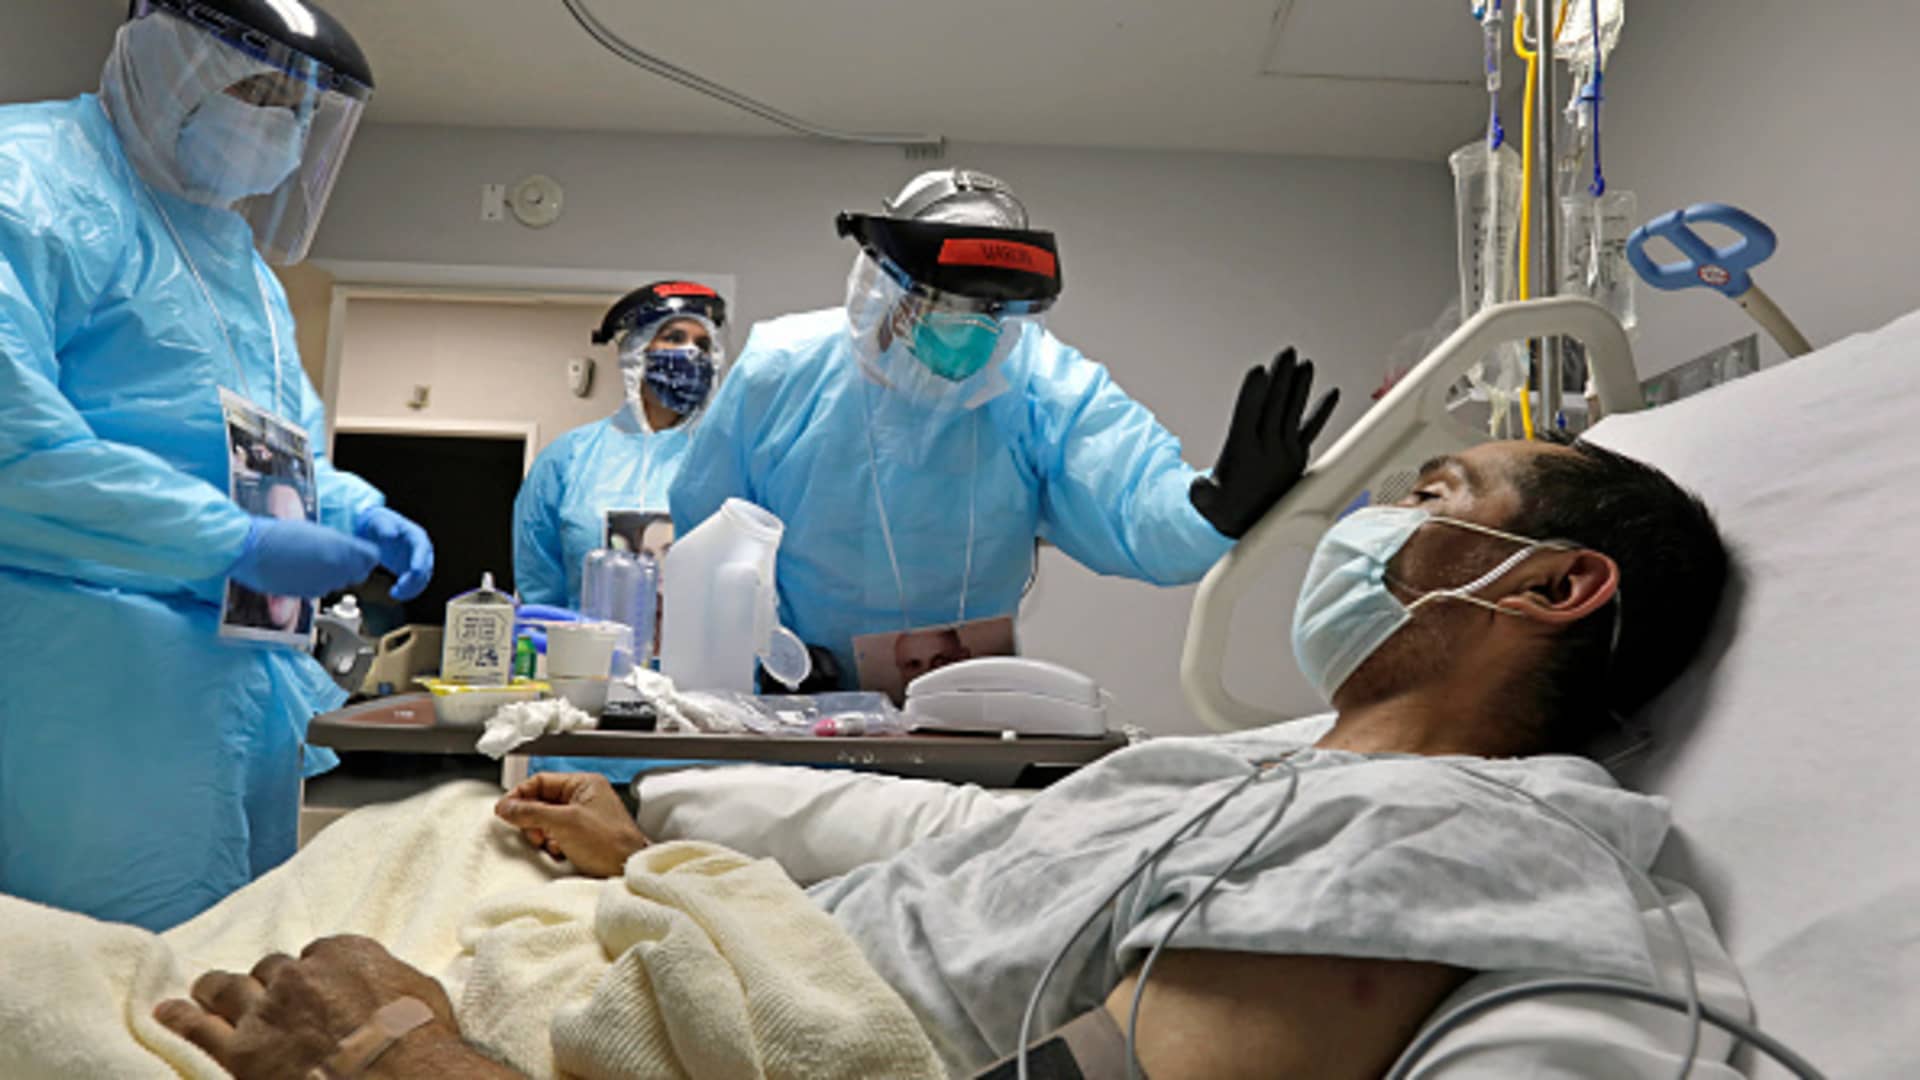
    The Covid-19 unit at United Memorial Medical Center in north Houston.

    Carolyn Cole | Los Angeles Times | Getty Images

    Long Covid has affected as many as 23 million Americans to date — and it’s poised to have a financial impact rivaling or exceeding that of the Great Recession. By one estimate, the chronic illness will cost the U.S. economy $3.7 trillion, with extra medical costs accounting for $528 billion.

    Costs on a household and national scale are tough to quantify because the illness — also known as long-haul Covid, post-Covid or post-acute Covid syndrome — is so new. Anyone with a prior Covid-19 infection is susceptible, regardless of factors such as age, health or vaccine status.

    Symptoms, which number in the hundreds, can range from mild to severe and may persist for months or even years.

    David Cutler, an economist at Harvard University who projected the $3.7 trillion economic cost of long Covid, estimates the individual medical costs of the disease to be about $9,000 a year, on average. However, typical costs can range from roughly $3,700 up to almost $14,000, Cutler said.

    More from Your Health, Your Money

    Here’s a look at more stories on the complexities and implications of long Covid:

    Costs can be much higher, depending on the severity of illness. And because symptoms often impact a person’s ability to work, someone suffering from long Covid may not be able to lean on a regular paycheck — or employer-sponsored health insurance — to help cover those medical bills.

    Cutler’s financial estimate draws on prior research into treatment for myalgic encephalomyelitis, a condition also known as chronic fatigue syndrome, or ME/CFS.

    Dr. Greg Vanichkachorn, medical director of the Mayo Clinic’s Covid Activity Rehabilitation Program, said those estimates are the best approximation right now, since treatment and evaluation for long Covid are similar to those for ME/CFS. There is no cure or approved treatment for ME/CFS; as with long Covid, patient symptoms are merely treated or managed.

    “I think it is important to note that this, again, is an estimate,” Vanichkachorn said. “As new treatment measures come out, things could get more expensive or, hopefully, more affordable.”

    “That’s the nature of the word ‘long-haul’ — it can be an open box of costs for a while,” Vanichkachorn said.

    ‘People are trying all sorts of treatments’

    Getting an official long Covid diagnosis can be challenging, which can compound early expenses.

    The afflicted may undergo a battery of tests to rule out other ailments, for example. Or doctors may refer patients to specialists for treatment if they’re unfamiliar with long Covid or unwilling to entertain it as a possibility.

    Medical professionals typically treat infectious disease by identifying the invasive organism and attacking it. But that’s not what’s happening with long Covid.

    Why long Covid could cost the U.S. nearly $4 trillion

    Instead, doctors treat symptoms of the disease, not the disease itself, said Dr. Jeff Parsonnet, an infectious disease physician who started the Post-Acute Covid Syndrome clinic at Dartmouth Hitchcock Medical Center.

    Some of the most common long Covid symptoms include fatigue, post-exertional malaise, chronic pain, cognitive dysfunction (also known as “brain fog”), neurological tremors, depression, anxiety and cardiac or pulmonary impairment, according to the U.S. Department of Health and Human Services. Long Covid can also cause other chronic conditions such as diabetes, myalgic encephalomyelitis or chronic fatigue syndrome and heart disease, HHS said.

    Treatment is more about symptom management: If a patient experiences fatigue, doctors may recommend physical therapy; if pain, then pain medication; if brain fog, perhaps speech or occupational therapy; if depression or insomnia, perhaps sleep studies, counseling or psychiatric evaluation.

    “The real difficulty in treating patients with long Covid is, we don’t know what causes it,” Parsonnet said. “People are trying all sorts of treatments, but it’s guesswork at this point.

    “They don’t cure anything, but they help people cope better,” he said, describing the treatments as “labor intensive and expensive.”

    Health insurance is essential — if you can get it

    Health insurance may cover some or most expenses associated with diagnosis and treatment — that is, for those who have it.

    Here’s what that looks like for three patients with long Covid:

    Uninsured and weighing specialist visits against rent

    Rosa Santana

    Source: Julia Santana

    Rosa Santana, 56, is a self-employed yoga instructor in south Florida. She doesn’t have health insurance, and so she can’t afford to visit specialists, despite feeling like she’s “been living in a different body” since a Covid infection in May 2020.

    “Every time I go somewhere, I know it’s going to be $300 or $400, and [I wonder], ‘Will I make my rent?'” Santana said of doctor visits.

    Yoga used to be a form of health care for her. Now, it doesn’t offer the relief it used to; doing a headstand can cause heart palpitations and dizziness for days afterward.

    Long Covid has impacted Santana’s ability to work, and her income stream to cover any medical bills. Before, she was like the “Energizer bunny”; now, she schedules two private yoga sessions with clients and it’s “time to rest,” she said.

    Hitting annual out-of-pocket max with a single infusion

    Donna Pohl

    Source: Donna Pohl

    Donna Pohl hits her insurance plan’s yearly out-of-pocket maximum — about $3,500 — after just one infusion for common variable immunodeficiency, or CVID.

    Pohl, 56, was healthy before a severe case of Covid, for which she was hospitalized in fall 2021. Now, CVID — a complication resulting from long Covid — puts her at increased risk of infections. Without insurance, Pohl would pay more than $10,000 for each infusion; she needs them monthly.  

    Pohl, who lives in Bettendorf, Iowa, has a roster of 10 doctors, including a primary care physician and nine specialists.

    In early 2022, she was diagnosed with Mast Cell Activation Syndrome, a disease that causes severe allergic reactions. She’s had pneumonia three times in a year. Pohl falls often due to “neuropathy,” a type of nerve damage; she ruptured a ligament in her left hand in a recent fall and needs surgery to repair it.  

    “I’m a year out, and I’m still getting new symptoms,” she said.

    Pohl, a nurse practitioner at a hospital, counts herself lucky in one sense: She can’t work her grueling emergency-room shifts right now, but the hospital kept her job (and her employer-sponsored health insurance) intact.

    I’m a year out, and I’m still getting new symptoms

    Donna Pohl

    nurse practitioner

    Without insurance coverage, costs for Pohl’s 156 medical claims through October this year would have amounted to more than $114,000, records show.

    Like many who suffer from long Covid, Pohl seeks relief from crippling symptoms wherever it’s available.

    That means she pays about $300 to $400 a month, on average, for many supplements and therapies that aren’t covered by insurance: chiropractic work, nutrition consultations and hyperbaric oxygen, which has “by far” been the best treatment, she said.

    She lives on 60{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of her prior income from a long-term disability insurance policy — which, in the best-case scenario, will continue until early 2024.

    COBRA coverage and a $4,000 deductible

    Sam Norpel and her family. Norpel, 48, second from the right, got Covid-19 in December 2021 and hasn’t recovered. This chronic illness, known as long Covid, impacts up to 23 million Americans.

    Kirstie Donohue

    Sam Norpel, 48, lost her job in June. Debilitating symptoms — including unpredictable bouts of broken speech, cognitive issues, chronic fatigue and severe migraines with prolonged screen time — made it impossible for the former e-commerce executive to keep working.

    Norpel, who lives outside Philadelphia, was able to negotiate that the employer pay her COBRA premiums for a year so she could keep her employer-sponsored health insurance.

    Even with the health plan, the family paid roughly $4,000 out of pocket to hit the plan’s annual deductible. Norpel’s husband, who’d been out of work to care for their kids, is planning to return to the labor force partly to avoid losing workplace health coverage.

    ‘People … do get better,’ but it’s hard to see specialists

    There are nearly 250 post-Covid clinics in the U.S., according to Survivor Corps data as of early November. (A provider with multiple physical clinics is only counted once.) The list is growing steadily: There were 178 in January.

    Even so, skyrocketing demand for specialists to treat long Covid means the afflicted can spend up to a year waiting for an appointment, according to the U.S. Department of Health and Human Services.

    Norpel reached out to the Mayo Clinic in April, but the next available consultation was about four months later, in August.

    That’s the nature of the word ‘long-haul’ — it can be an open box of costs for a while.

    Dr. Greg Vanichkachorn

    medical director of the Mayo Clinic’s Covid Activity Rehabilitation Program

    An additional hurdle: She also had to pay her way to get there — a hotel room for a week and round-trip airfare from Pennsylvania to Minnesota. She also can’t get a follow-up appointment with a neurologist until February next year.

    “There are so many of us now that it’s taking months to see professionals,” she said of long Covid patients.

    When it comes to treatment, however, time is of the essence. Early intervention — generally less than four months from infection — has yielded better outcomes for patients, Vanichkachorn said.

    “Despite all the doom and gloom out there, people actually do get better,” he said.

    Patients at his clinic typically return to their normal, baseline function four to six months after treatment starts, he explained.

    New study raises serious concerns over long Covid impact

    Time alone generally doesn’t cure long Covid symptoms; it often requires some form of rehabilitation. Months of low activity can lead to serious physical deconditioning, compounding patients’ malaise. Physical and occupational rehab helps strengthen muscles and aids patients in reframing their daily lives as they recover, Vanichkachorn said.

    “People are really sick of being sick,” he said. “They try to push themselves way too hard. “It’s really difficult to tell people we have to go slower, and that’s the only way we can get you better as fast as you can.”

    Treatment delays can have broader financial impacts, too. Patients are more likely to be denied financial assistance from disability insurance without a diagnosis and certifications from specialists, HHS said. They may also face more challenges requesting workplace accommodations.

    Despite slow progress, patients and medical experts remain optimistic. The U.S. government has more than 72 active long Covid research programs in place, according to HHS. One of them, the RECOVER initiative, led by the National Institutes of Health, has about 7,000 patients enrolled at clinical sites. The CDC’s Innovative Support For Patients with SARS-CoV-2 Infections (or, INSPIRE) is enrolling up to 6,000 adults.

    “The scale of long Covid morbidity and the breadth of its clinical manifestations represent an unprecedented, but not insurmountable, challenge,” according to the HHS’ National Research Action Plan on Long COVID.

    The research is still in its early stages, Vanichkachorn said.

    “We may have a brand-new treatment regimen two months from now and people can get suddenly get better,” he said.

    Covid evolution wipes out another antibody treatment

    Covid evolution wipes out another antibody treatment

    The Food stuff and Drug Administration on Wednesday ended its unexpected emergency authorization for the only remaining Covid-19 antibody therapy cleared for use, indicating variants that render it ineffective are now dominant in the United States.

    The news about bebtelovimab helps make formal what has been expected for various months, as the Omicron sublineages BQ.1 and BQ.1.1 have been growing in prevalence. Continue to, it comes as a blow to both equally companies and sufferers who are at possibility for additional critical outcomes. The rapid evolution of the SARS-CoV-2 virus had currently knocked out quite a few other monoclonal antibodies for the procedure of Covid.

    Eli Lilly, the maker of bebtelovimab, has stopped the industrial distribution of the treatment, the Fda mentioned. Various organizations are working on current antibody therapies, but none seems near to being authorized.

    advertisement

    “Lilly will continue on to lookup [for] and evaluate monoclonal antibodies to identify possible candidates for scientific enhancement in opposition to new variants,” the company reported in a assertion.

    With each other, the “BQs” — as the two sublineages are acknowledged — are resulting in about 57{35112b74ca1a6bc4decb6697edde3f9edcc1b44915f2ccb9995df8df6b4364bc} of U.S. bacterial infections, according to estimates from the Facilities for Sickness Command and Avoidance. 

    ad

    The BQs are also undermining the efficiency of Evusheld, a type of pre-exposure remedy that provides an extra enhance of safety for individuals who battle to make a solid immune response when vaccinated. For now, Evusheld continues to have unexpected emergency use authorization from the Food and drug administration, however the company warned past thirty day period about the emergence of variants that are not neutralized by Evusheld. 

    Without the need of bebtelovimab and Evusheld, some 7 million immunocompromised People in america will lose highly effective defenses. There are other treatments obtainable, together with the oral antiviral Paxlovid, but quite a few folks — including transplant recipients — are on remedies that just cannot be taken at the exact same time as Paxlovid. 

    Other treatments are obtainable but have their restrictions. A different oral antiviral, Merck’s molnupiravir, is not as productive as Paxlovid. Remdesivir, or Veklury, aids hold individuals from finding so ill they have to be hospitalized, but it has to be supplied intravenously over three times — a major inconvenience compared to an oral remedy. 

    Get your day-to-day dose of well being and medication each weekday with STAT’s no cost e-newsletter Morning Rounds. Indicator up below.